If you have an ectomorph body type, you probably gain weight slowly, carry less muscle by default, and feel “full” fast. The upside? With the right training focus and a reliable calorie surplus, your frame can add size and strength—often faster than you expect—once you standardize the basics and track progress weekly. For broader context on how somatotypes are used (and misused), see this plain-English primer on ectomorph, mesomorph, and endomorph.
The two other body types you might want to read more about are:
At a glance, ectomorphs tend to have narrower shoulders and hips, longer limbs, smaller joints, and a leaner look at the same bodyweight as peers. Crucially, somatotypes are not destiny; treat them as a quick heuristic that suggests where to start your plan, not how it must end. That’s why we’ll combine practical experience with established guidelines from the American College of Sports Medicine and current hypertrophy research to steer your programming choices.
Key takeaways up front
You’ll build best with compound lifts first, modest accessories second, and steady progression week to week. Evidence shows hypertrophy occurs across a range of loads when sets are taken sufficiently hard; nevertheless, heavier loading still favors strength (see Schoenfeld et al., 2017).
Gaining requires a daily calorie surplus, not occasional feasts. You’ll anchor protein at evidence-based targets and then push carbs to fuel training (supported by Morton et al., 2018 and the ISSN protein position stand).
Although many ectomorphs assume they need super-high reps or marathon sessions, the research indicates you can build muscle with both lighter and heavier loads—as long as you train close enough to failure and accumulate sufficient weekly volume. Schoenfeld et al. (2017) reported similar hypertrophy outcomes across a low-to-high loading spectrum; strength, however, favored heavier work. Practically, that means mixing heavy compounds with moderate-rep accessories is ideal.
Weekly frequency and progression (why it works)
Begin with 3–4 lifting days each week so you can hit major muscle groups about 2× weekly. This lines up with ACSM progression models for novices and intermediates and matches what most busy lifters can recover from while still eating enough. Just as importantly, cap most sessions at 60–75 minutes so you leave fresh enough to eat well.
Day 5 — Lower (hinge/glute-bias) Conventional Deadlift 3×3–5 • Front Squat 3×6–8 • Hip Thrust 3×8–10 • Lying Leg Curl 3×10–12 • Ab Wheel 3×8–12
Days 6–7 — Rest
B. Progression that builds muscle on an ectomorph body type
Add load or reps weekly within the stated ranges while keeping top sets 1–3 reps shy of failure most of the time.
If a lift stalls for three weeks, add one set to that movement or swap to a close variation (e.g., high-bar to low-bar squat) and rebuild.
Keep long steady-state cardio minimal during gain phases; short walks (10–20 minutes) help appetite and recovery without draining you.
Why this works: moderate volume across two exposures per muscle keeps stimulus frequent without wrecking recovery. It also encourages skill with the big lifts while leaving time and energy to eat.
Let’s keep it simple: most ectomorphs undereat. You don’t need “dirty bulks,” but you do need consistent surplus. Start by estimating maintenance with the RMR calculator, then set macros using Macro Master and adjust from the scale each week.
Start with maintenance +250–500 kcal/day (choose the higher end if you’re very lean and training 4×/week).
Build meals from rice, oats, pasta, potatoes; then add a spoon of oil or ghee. For ideas, scan healthy weight-gain foods.
Prefer local, seasonal fruit; for eg. enjoy mangoes in moderation—myth-busting here: mangoes & weight gain.
Hitting protein targets without drama
Vegetarian or simply busy? No problem. Anchor your day with one “linchpin” meal that delivers ~40–50 g protein, then distribute the rest. For plant-forward batch cooks, these quinoa meal-prep ideas and high-protein chia prep posts provide simple, repeatable templates you can scale.
Why we care about protein: a large meta-analysis suggests benefits accrue up to ~1.6 g/kg/day for trained individuals, with possible advantages a bit above that depending on context (Morton et al., 2018). The International Society of Sports Nutrition aligns with daily and per-meal recommendations that are practical and sustainable. For extra context on supplementation, see reviews like Nunes et al., 2022 and Cintineo et al., 2018.
Protein powders are not magic—only convenient. Use whey, casein, or a good plant blend to reach the day’s total. If nighttime appetite exists, casein can help you tick the box without feeling stuffed. For whole-food variety (and minerals), rotate dairy, eggs, dals/legumes, tofu/tempeh, poultry, and fish.
As for supplements, creatine monohydrate (3–5 g/day) remains the best-supported single add-on for strength and lean mass. For safety and efficacy, rely on the ISSN creatine position stand (2025 update) and the earlier accessible open-access review. You don’t need a loading phase, and timing is flexible—take it whenever you remember. If you want a consumer-friendly explanation first, here’s a plain-English creatine side-effects guide.
Male vs Female: Applying the Plan to Your Ectomorph Body Type
Despite different goals, men and women succeed with the same principles—volume, progression, calories, and patience—while fine-tuning emphasis.
Men:
Push compounds that expand the silhouette: bench and overhead presses for chest/delts, rows and pull-ups for back width, squats and deadlifts for legs.
Eat more on lower-body days, when systemic fatigue (and thus fuel need) is higher.
Track a few “north star” lifts (e.g., 5-rep max on squat/bench/row) and chase slow increases monthly.
Women:
Prioritize glutes, hamstrings, lats, and delts for shape. Hip thrusts, RDLs, Bulgarian split squats, pull-downs/pull-ups, and lateral raises do heavy lifting here.
Keep protein every day, not just on training days, to support recovery and appetite control.
Consider slight carb cycling: +20–30 g carbs on hard days, –20–30 g on rest days—only if it helps adherence.
Either way, movements, sets, and reps differ less than you think; the ectomorph body type benefits most from consistency, not perfect exercise selection.
A Simple Weekly Checklist for Ectomorph Weight Gain
Train 3–4×/week, mostly compounds first, accessories second; take most sets within 1–3 reps of failure, keep 60–75 minutes per session. See the load-range evidence in Schoenfeld 2017.
Eat in surplus daily, not “whenever.” If your 14-day average weight doesn’t rise, add +150–250 kcal/day and reassess a week later.
Hit protein (~1.6–2.2 g/kg/day). That range is supported by Morton 2018 and the ISSN position stand; split across 3–5 meals you actually like.
Troubleshooting for the Ectomorph Body Type (quick fixes)
“I feel stuffed and can’t eat more.” Shift calories to liquids and semi-solids: milk-based shakes with oats and nut butters; yogurt bowls with granola and honey; fruit plus dates between meals. If needed, add 1–2 tsp of olive oil or MCT to smoothies for 80–160 easy calories. Borrow blueprint ideas from nut-infused smoothies or macadamia & sunflower protein shakes, but swap in regular milk and oats to boost calories.
“My lifts aren’t moving.” First, eat. Then add a back-off set at 60–70% for higher reps (12–15) after your top sets, or add a small 2.5 kg increment to your main lift every other week. Finally, rotate variations to keep momentum.
“I’m getting softer.” Ease the surplus down 100–150 kcal/day and maintain for two weeks. Keep protein steady; optionally increase steps slightly (no need for long cardio blocks).
“I miss sessions.” Use a 3-day full-body rotation instead (A/B/C), repeating weekly and sliding days as life allows. Each session: a squat/hinge, a press, a pull, plus 1–2 accessories.
Final Word
The ectomorph body type isn’t a limitation; it’s a programming clue. Build around heavy compounds, feed your training with a dependable surplus, standardize protein, and repeat—week after week. Use shakes when appetite fades, walk to recover, and choose a small handful of lifts to improve relentlessly. Then, let time do what time does best: compound your effort into visible muscle.
FAQs
1) What is the ectomorph body type?
An ectomorph body type is typically lean with a narrower frame, long limbs, and lower baseline muscle and fat. Consequently, ectomorphs often find it harder to gain weight or size without a structured plan.
2) What does “ectomorph meaning/definition” imply for training?
Practically, it signals you’ll respond best to progressive strength work, compound lifts first, and consistent recovery. Moreover, keep sessions focused (60–75 minutes) and push effort close to failure.
3) Ectomorph vs mesomorph vs endomorph—what’s the difference?
Briefly: ectomorphs gain slowly, mesomorphs are naturally more muscular, and endomorphs store fat more easily. Nevertheless, most people are a blend; use the category that best matches your current traits.
4) Can an ectomorph become “mesomorphic” in appearance?
Yes. With years of progressive overload, appropriate calories, and patience, an ectomorph can build a visibly more muscular, “meso-like” physique. Ultimately, habits drive results more than labels.
5) What’s the best ectomorph workout plan?
Prioritize a 3–4 day split that hits each muscle twice weekly. Notably, use heavy compounds (squat, deadlift, bench, row, pull-ups, overhead press) plus moderate-rep accessories for volume.
6) Best exercise for ectomorphs—what should top the list?
Start with multi-joint moves: back squat, Romanian deadlift, bench press, barbell row, overhead press, and weighted pull-ups. Additionally, add hip thrusts, lunges, leg curls, laterals, and curls to round out weak points.
7) How many sets and reps suit an ectomorph body type?
Aim for ~10–16 hard sets per muscle per week. Likewise, work mostly in 6–12 reps on compounds, 8–15 on accessories, keeping 1–3 reps in reserve most sets.
8) Should ectomorphs do cardio while gaining?
Yes—lightly. Meanwhile, prefer short walks or 10–20 minutes of easy cardio to aid appetite and recovery; avoid long, frequent endurance sessions during surplus phases.
9) What is the best ectomorph diet plan?
Build a daily calorie surplus of +250–500 kcal above maintenance. Furthermore, anchor protein at ~1.6–2.2 g/kg/day, set fats at 0.6–1.0 g/kg/day, and let carbs fill the remainder to fuel training.
10) How fast should ectomorph weight gain happen?
Target roughly 0.25–0.5 kg per week. Consequently, if your two-week average weight stalls, increase intake by +150–250 kcal/day and reassess after seven days.
11) What foods help an ectomorph gain weight without feeling stuffed?
Choose energy-dense staples: milk, oats, rice, pasta, potatoes, breads, dried fruit, nuts, nut butters, olive oil, and ghee. Beyond that, use smoothies and shakes to sneak in liquid calories.
12) Best protein for ectomorphs—what should I pick?
Whey concentrate/isolate, casein (especially at night), or a quality plant blend (pea/rice/soy) are all effective. Importantly, the “best” is the one you’ll take consistently to hit your daily total.
13) Which supplements are worth it for an ectomorph body type?
Keep it simple: creatine monohydrate (3–5 g/day), basic protein powder for convenience, omega-3s if intake is low, and vitamin D as needed. Otherwise, focus primarily on food and training.
14) Do ectomorph women need a different plan than men?
Principles are identical—volume, progression, surplus, and sleep. However, exercise selection can emphasize glutes, hamstrings, lats, and delts for shape while still progressing the big lifts.
15) What does an “ectomorph meal plan for muscle gain” look like?
Organize 4–6 feedings with at least one 40–50 g protein “anchor” meal; surround workouts with carbs; and include a calorie-dense shake daily. Additionally, pre-prep staples (rice, oats, potatoes, proteins) every 2–3 days.
16) Is a mass gainer necessary for ectomorph weight gain?
Not at all. Instead, blend your own: milk, oats, banana, nut butter, and a scoop of protein. This homemade option is flexible, cheaper, and easier to tailor to your targets.
17) What’s an ectomorph compound workout day example?
Try: Back Squat 4×6–8, Romanian Deadlift 3×8–10, Bench Press 4×6–8, Barbell Row 3×6–8, Hip Thrust 3×8–10, Lateral Raise 2×15–20. Furthermore, rest 90–150 seconds between hard sets.
18) How should an ectomorph track progress?
Use a simple trio: weekly average bodyweight, key lift logs (e.g., 5-rep bests), and biweekly front/side photos. Consequently, make small adjustments—load, reps, or calories—based on those trends.
19) Are “ecto endo meso” types fixed for life?
No. Genetics set starting points, yet training, nutrition, and recovery shift your look substantially. Nevertheless, accept your structure while maximizing what you can control.
20) What’s the fastest way for an ectomorph to add muscle safely?
Lift 3–4×/week with progressive overload, maintain a daily surplus, hit protein every day, sleep 7–9 hours, and repeat. Ultimately, disciplined consistency—more than novelty—drives visible change.
Creatine has long held the spotlight in the fitness and sports nutrition world, hailed for its ability to enhance muscle mass, strength, and performance. But as its popularity has surged among both athletes and everyday fitness enthusiasts, so too have concerns about its potential side effects. Is creatine really as safe as claimed? Or are there hidden downsides masked by its benefits?
In this detailed blog post, we’ll examine the most up-to-date clinical research as of 2025, compare that with real user experiences, and offer practical strategies to safely supplement creatine while minimizing risks. Whether you’re already taking creatine or just considering it, this guide will give you the nuanced understanding you need.
🔬 The Scientific Verdict: Creatine Is Largely Safe
A sweeping 2025 meta-analysis encompassing 685 clinical trials and over 25,000 participants has added significant weight to the scientific consensus: creatine is safe for healthy adults when used at recommended doses. In this landmark review, the incidence of side effects among creatine users (13.7%) was nearly identical to that of placebo users (13.2%).
This mirrors decades of smaller studies and expert opinions, such as those from the International Society of Sports Nutrition (ISSN), which affirm creatine’s safety profile across multiple health markers—especially when consumed as creatine monohydrate at 3–5 g/day.
However, “safe” doesn’t mean free from all side effects—particularly in individuals with certain sensitivities or preexisting health conditions. Let’s break this down in more detail.
🫰 Commonly Reported Side Effects (and What Science Says)
1. Gastrointestinal Discomfort
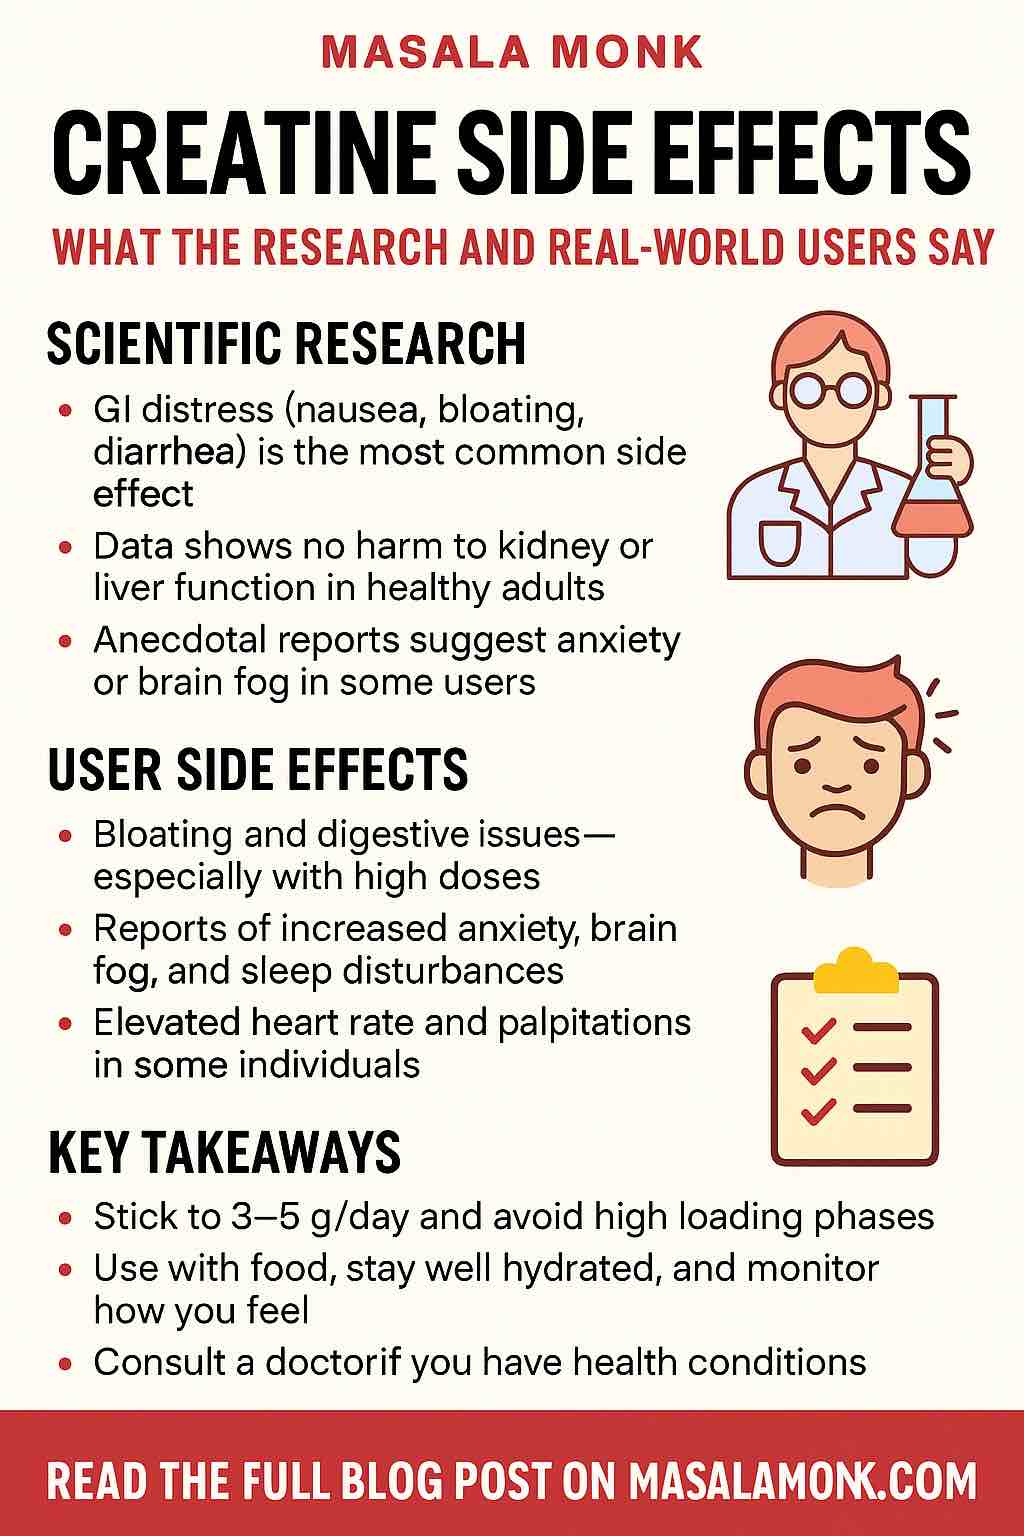
Clinical finding: Mild bloating, cramping, or diarrhea is the most frequently reported side effect, especially during high-dose loading phases (20 g/day).
User experience: Many Reddit and forum users report upset stomachs, gas, and nausea—particularly when taking creatine on an empty stomach.
Prevention tips:
Stick to 3–5 g/day; skip the loading phase.
Take with meals to improve tolerance.
Use micronized creatine monohydrate for better solubility.
2. Water Retention and Temporary Weight Gain
Clinical finding: Creatine draws water into muscle cells, leading to an initial weight increase of 1–2 kg. Long-term studies find no impact on total body water balance.
User experience: Many users report feeling “puffy” or bloated early in supplementation, but often note this dissipates over time.
Reality check: This is intramuscular water, not fat gain, and often enhances muscle fullness.
3. Sleep Disturbances and Night Sweats
Clinical finding: Largely anecdotal, with no confirmed link in clinical trials.
User experience: A noticeable subset report insomnia, vivid dreams, or night sweats—especially when dosing late in the day.
Prevention tips:
Take creatine earlier in the day.
Stay well hydrated.
4. Mood Effects, Anxiety, and Brain Fog
Clinical finding: Some evidence suggests creatine may help with cognitive function and mood in depression, but there are mixed reports in otherwise healthy users.
User experience: Some users describe brain fog, emotional dullness, or worsened anxiety—potentially linked to creatine’s role in brain energy metabolism or methylation pathways.
Caution: Those with a history of anxiety or bipolar disorder should consider starting with lower doses and consulting a healthcare provider.
5. Heart Rate & Palpitations
Clinical finding: No reliable evidence of cardiovascular stimulation.
User experience: A few individuals report increased heart rate or mild palpitations, which may be secondary to dehydration or anxiety rather than creatine itself.
Tip: Ensure proper hydration and evaluate for other confounding factors like caffeine intake.
🧬 The Most Debunked Myths About Creatine
Kidney Damage: No evidence supports kidney damage in healthy users at standard doses—even in long-term studies up to 5 years.
Liver Damage: Similarly, liver enzymes remain stable in clinical evaluations.
Hair Loss & Acne: No direct mechanistic link exists, though speculation around increased DHT remains unproven.
Cramping & Dehydration: In fact, some studies show fewer cramps due to enhanced muscle hydration.
Rhabdomyolysis: Creatine is not linked to rhabdomyolysis in healthy users; risk is more associated with extreme training or other medications.
🧰 Who Should Be Cautious?
Individuals with Preexisting Kidney Conditions: Always consult a physician.
Those with Bipolar Disorder or Mood Instability: Some case studies link creatine to manic episodes.
Adolescents: Safe use is possible, but long-term data is still emerging.
Pregnant or Breastfeeding Individuals: Insufficient evidence for safety.
⚡ Best Practices to Minimize Side Effects
Use a pure, micronized creatine monohydrate with third-party certification (e.g., NSF, Informed Sport).
Stick to 3–5 g/day—no need to load unless under guidance.
Take with a carb-rich meal to aid absorption and minimize GI issues.
Hydrate consistently, especially during workouts.
Avoid combining with stimulants if you’re sensitive to heart rate changes.
📊 Summary: Creatine Is Effective and Mostly Safe, But Not for Everyone
Creatine remains one of the most well-researched and effective supplements available—offering real benefits for muscle growth, performance, and even cognitive health. The risks? Generally mild and avoidable for most people, particularly when used responsibly. But it’s clear from both research and user reports that some individuals may experience side effects—especially when underlying health issues or poor supplementation practices are at play.
As with any supplement, personalization is key. Start low, monitor how you feel, and adjust as needed.
Have you experienced side effects from creatine, or found a strategy that worked for you? Share your insights in the comments—we’d love to hear from real users and keep the conversation evidence-informed and grounded in real-world use.
🔍 10 Frequently Asked Questions (FAQs)
1. Is creatine safe for long-term use? Yes, long-term studies (up to 5 years) show no adverse effects in healthy individuals when taking recommended doses (3–5 g/day). Kidney and liver function remain unaffected.
2. What are the most common side effects of creatine? The most frequently reported side effects are bloating, mild stomach discomfort, and temporary water retention—mostly during loading phases or when taken without food.
3. Can creatine cause anxiety or brain fog? While rare, some users report increased anxiety or mental cloudiness. There’s limited scientific evidence, but people with anxiety disorders should start with lower doses and monitor their response.
4. Does creatine affect sleep or cause night sweats? Clinical data doesn’t support a link, but anecdotal reports suggest it might in some individuals. Taking it earlier in the day and staying hydrated may help.
5. Is creatine bad for your kidneys? No. Numerous studies confirm that creatine does not harm kidney function in healthy users. Those with pre-existing kidney issues should consult a healthcare provider first.
6. Can creatine worsen acid reflux or heartburn? There’s no strong evidence, but a few users report increased reflux. Taking creatine with food and avoiding high doses may reduce this possibility.
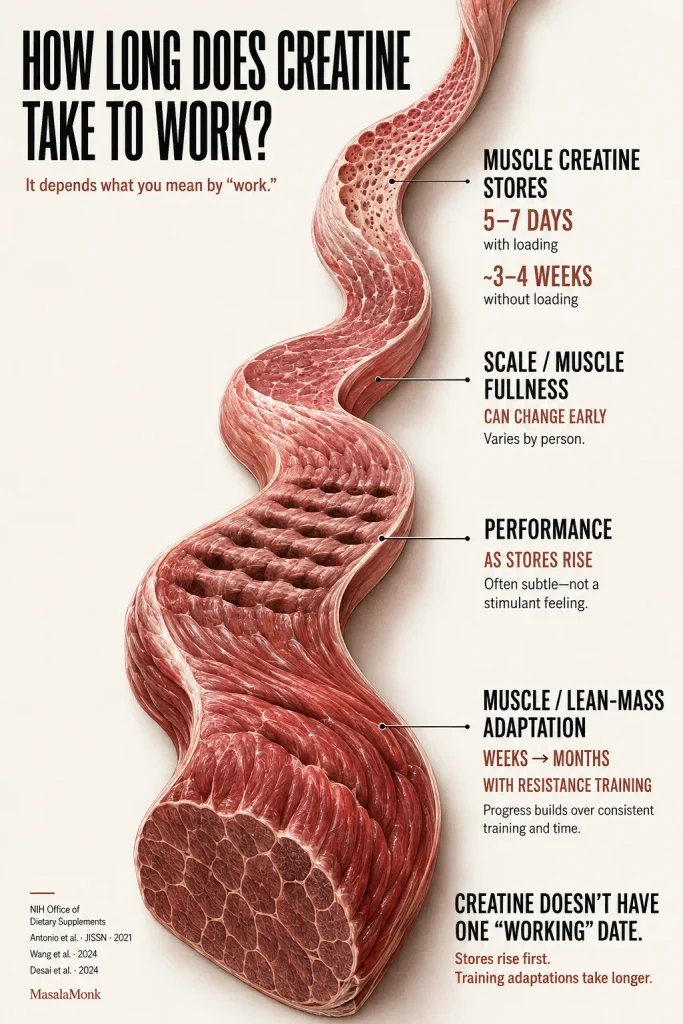
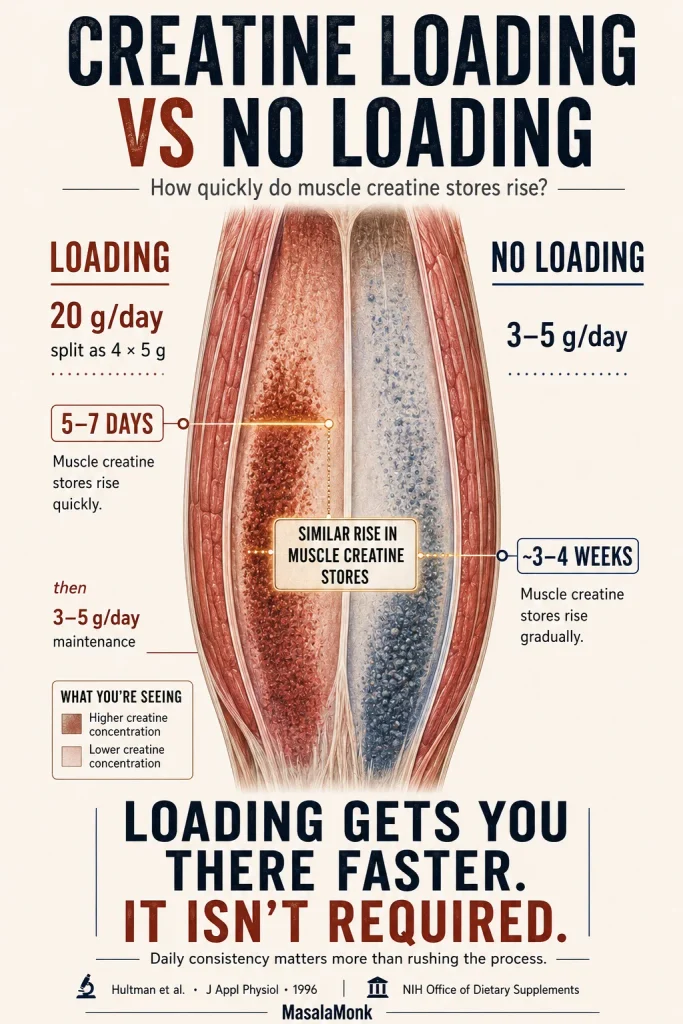
7. Is it necessary to do a loading phase with creatine? No. While loading (20 g/day for 5–7 days) saturates muscles faster, daily intake of 3–5 g reaches the same levels within 3–4 weeks and has fewer side effects.
8. Will creatine make me gain fat or look bloated? Creatine increases water content in muscle cells, not fat. Some early bloating may occur, but it typically subsides and muscle definition often improves.
9. Are there differences in side effects between creatine monohydrate and other forms? Creatine monohydrate is the most studied and generally best tolerated. Other forms (e.g., HCL, ethyl ester) claim better absorption but lack robust data and may not reduce side effects.
10. Can teenagers safely use creatine? Some research supports safe use in adolescents involved in supervised athletic programs, but long-term safety data is limited. Parental guidance and medical consultation are advised.
This guide has been substantially revised to include newer evidence on creatine and kidney function, hair loss, strength, body composition, cognition, postmenopausal women and safety.
Creatine used to be easy to understand. Lifters took it because it helped them train harder and get stronger.
Now someone is taking it for menopause. Someone else is worried it will ruin their kidneys. And someone who has never touched a barbell is considering it for their brain while quietly wondering what that daily scoop might do to their hairline.
Creatine deserves neither the old fear nor the new mythology.
If you are standing in front of a tub wondering what matters, start here.
Creatine works best where the evidence is deepest: resistance-training strength, repeated high-intensity exercise and somewhat greater lean-mass gains alongside training.
Creatine monohydrate is the default form to buy. More expensive alternatives have not convincingly shown that they work better.
For most healthy adults who choose to supplement, 3–5 g/day is a simple routine. Loading is optional: about 20 g/day split into four doses for 5–7 days raises stores faster, while a smaller daily dose gets there more gradually.
Consistency matters more than a perfect workout window. Rest days use the same daily routine, and routine cycling is not established as necessary.
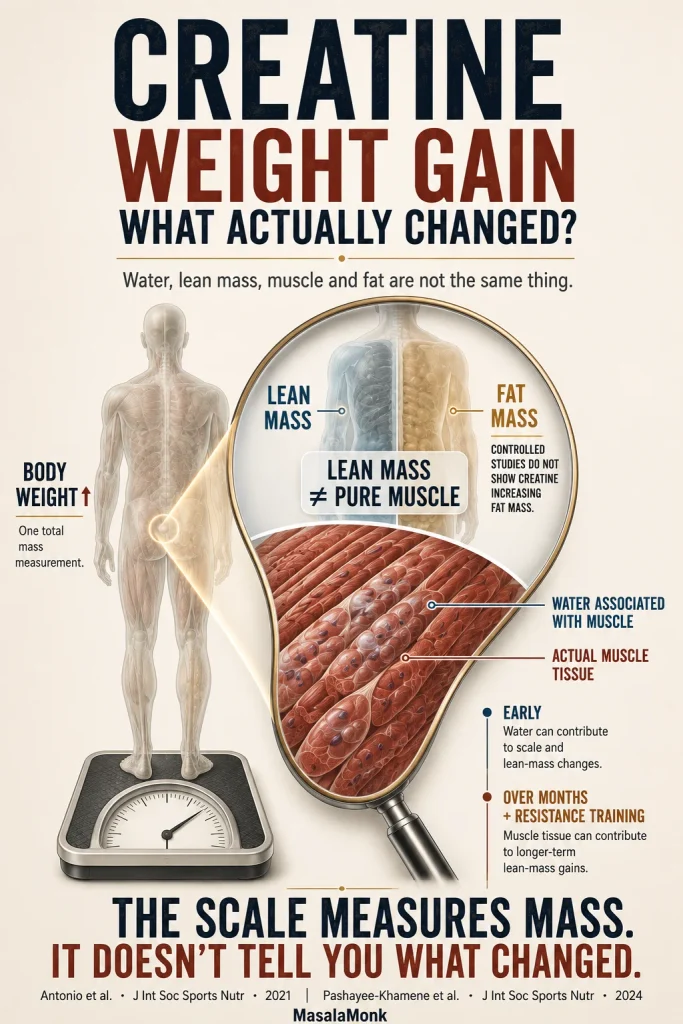
Early scale weight can rise. Water associated with muscle can contribute, so a quick increase does not tell you that you gained the same amount of fat—or pure new muscle.
The healthy-adult safety literature is reassuring, while newer claims deserve different levels of confidence. Creatinine-based kidney tests can be affected by creatine use; direct hair-loss evidence is reassuring; memory and postmenopausal findings are promising but narrower than the marketing often suggests.
Creatine monohydrate remains the most studied form, and the NIH Office of Dietary Supplements summarizes the common loading and non-loading approaches used in research.
What is creatine actually good for?
The internet tends to flatten very different claims into one enormous list of “creatine benefits.”
The evidence falls into very different tiers.
Use the evidence hierarchy as a filter whenever you encounter a new creatine benefit claim. Ask what researchers actually measured: a real performance or health outcome, a surrogate marker, or merely a plausible mechanism. Mechanisms are useful reasons to investigate an idea; they should not automatically be promoted to the same status as replicated human outcomes.
Outcome
Where the evidence stands
Strength with resistance training
Strong
Repeated high-intensity exercise
Strong
Additional lean-mass gains with resistance training
Strong
Lean mass and strength in some older adults alongside resistance training
Good evidence
Lean mass and strength after menopause, particularly with resistance training
Promising / increasingly supported
Memory and some cognitive outcomes
Promising, but mixed overall
Long-duration endurance performance
No meaningful overall benefit established
Soreness and faster recovery from every workout
Mixed
Direct fat loss
Not established
Where creatine has its strongest outcome evidence—and where expectations should stay lower.
That difference between established, promising and plausible matters throughout this subject.
What creatine does inside your muscles
Your body already makes creatine, and foods such as meat and fish provide additional dietary creatine.
Most of the body’s creatine is stored in skeletal muscle. Some exists as phosphocreatine, which helps regenerate ATP when energy demand rises very quickly.
You do not need the biochemistry-textbook version to understand the practical consequence.
Think of phosphocreatine as part of a small, rapidly available energy reserve. Increasing muscle creatine gives that system more capacity.
That becomes particularly useful when the work is hard, short and repeated: another heavy set, another sprint, another explosive effort.
What will you actually notice after starting creatine?
Imagine you begin taking 3–5 g of creatine monohydrate every day.
Your muscle creatine stores gradually rise. Loading makes that happen faster; smaller daily dosing gets there more gradually. NIH Office of Dietary Supplements
The scale may move before your gym numbers do.
Your muscles may look a little fuller.
And you may feel…exactly the same.
That last part catches people out. Creatine is not caffeine. There is no required buzz or dramatic moment when it “kicks in.” Its benefit often appears in repeated work: maintaining performance a little better, completing slightly more useful training, or accumulating better sessions over time.
If you have taken creatine for three weeks and are thinking, I can’t feel anything, that does not automatically mean you need more.
If you want to judge whether creatine is helping, “Can I feel it?” is a poor test. Instead, keep the routine stable and watch what happens across repeated training sessions. Creatine can be doing its job without producing a buzz, pump or obvious moment when it suddenly switches on.
What about over months rather than days?
This is where supplementation and training become much more interesting.
A 2024 meta-analysis of resistance training and body composition found that adults under 50 who combined creatine with resistance training gained about 1.14 kg more lean body mass than those doing resistance training without creatine. Small favourable changes in body-fat measures were also reported.
That is not evidence that one scoop manufactures a kilogram of muscle. It is evidence that creatine can help resistance training produce somewhat greater adaptations over time.
Where creatine earns its reputation
Strength
This remains one of the clearest cases for taking creatine.
A 2025 systematic review and meta-analysis of 69 studies involving 1,937 adults separated several common strength tests instead of collapsing them into one upper- or lower-body number. Compared with placebo, creatine plus resistance training produced statistically significant pooled improvements in bench/chest press strength (+1.43 kg) and squat strength (+5.64 kg).
The same analysis did not find statistically significant overall differences for leg press or handgrip strength. It also reported significant improvements in vertical jump and Wingate peak power, reinforcing that creatine’s performance signal depends partly on the outcome being tested.
Those values are pooled group averages, not predictions for your next personal record. Different exercises, populations, training programs and study designs produce different estimates. Overall, resistance training tends to produce somewhat greater strength and power gains when creatine is added, but there is no single universal “creatine strength increase.”
Exercise-specific results should not be read as “creatine works for squats but not leg press.” Different pooled outcomes contain different studies, people and training protocols. More importantly, creatine can add a modest training advantage on average, while the size of that advantage is not fixed across every exercise or lifter.
Repeated high-intensity exercise
Creatine also performs well in activities built around short, hard efforts with limited recovery:
resistance training;
repeated sprints;
explosive efforts;
sports involving repeated bursts of high power.
That is exactly where the phosphocreatine system is most relevant.
Lean mass—if there is a training stimulus
Creatine can increase water associated with muscle fairly quickly. Over longer resistance-training interventions, it can also help produce greater lean-mass gains. See the 2024 body-composition meta-analysis.
Both are real.
Two popular summaries are both too simple: “Creatine gains are just water” and “every kilogram of extra lean mass is pure new muscle.” The early and long-term changes are not the same thing.
What creatine is less impressive at
A useful creatine guide should also tell you where enthusiasm needs cooling.
Long-duration endurance
Creatine is particularly good at supporting intense, repeatable muscular work. It has not shown the same clear advantage for prolonged endurance performance.
A 2026 scoping review of endurance and mixed-sport research adds a useful distinction. The more favourable signals tended to appear in selected contexts involving repeated high-intensity efforts, sprint finishes and power-endurance demands, while aerobic outcomes remained limited or inconsistent.
That is why “creatine for runners” is not a yes-or-no question. A distance athlete who also strength trains, attacks hills, performs repeated hard surges or relies on a finishing sprint has different demands from someone concerned only with prolonged steady-state endurance. Creatine is not a proven general endurance booster; its physiological fit is stronger when the event temporarily becomes intense.
Being a “runner” does not answer whether creatine fits your goals. A runner who also strength trains, performs repeated sprints or relies on explosive race moments has a different performance profile from someone focused almost entirely on prolonged steady endurance. The decision should follow the demands of the sport—not the label attached to the athlete.
Direct fat loss
Creatine is not a fat burner.
Resistance-training studies sometimes show favourable body-composition changes when creatine is added, but that should not be rewritten as “creatine melts fat.” Diet, energy intake, daily activity and training remain the important variables if fat loss is the goal.
Soreness and recovery
Recovery research is much less consistent than the strength literature.
One systematic review found no meaningful improvements in soreness, muscle-strength recovery, inflammation or range of motion after muscle-damaging exercise, although creatine kinase was reduced at one time point. Other meta-analytic work has found potentially favourable changes in some muscle-damage markers but substantial heterogeneity.
Creatine may eventually prove useful for particular recovery outcomes. It is not something I would buy primarily because I want tomorrow’s leg-day soreness to disappear.
If you are trying to lose fat, that can be unsettling.
But the scale cannot tell you whether that change came from body fat, muscle tissue, glycogen, water, food and fluid still in the digestive system, or several of these together.
Creatine increases muscle creatine storage, and water accompanies that process. An early increase in body mass can therefore happen far faster than you could plausibly build the same amount of new muscle tissue.
It is also not the same as gaining 800 grams of fat.
If body weight is one of your progress markers, note when you start creatine before interpreting a sudden change. The supplement can make the scale noisier before anything meaningful has happened to body fat, so one unexpectedly high week should not automatically trigger changes to an otherwise sensible nutrition or training plan.
Water, lean mass and muscle are different things
What you notice
What may be happening
Scale rises relatively quickly
Increased water can contribute
Muscles look somewhat fuller
More intramuscular water may contribute
A scan reports more lean mass
Lean mass includes water and other non-fat tissues
Strength and lean mass increase over months
Training adaptations and creatine can both contribute
Body fat
Creatine does not simply turn into fat
What an early change in scale weight or “lean mass” can—and cannot—tell you.
The opposite mistake happens too. If a scan reports an extra kilogram of “lean mass,” that should not automatically be described as a kilogram of newly built muscle fibre.
If the water part is what worries you, that is a separate question from scale weight: see creatine, hydration and cramps.
Creatine and the brain: interesting science, incomplete answers
There is real biology behind the brain question.
The brain has enormous energy demands and uses a creatine-phosphocreatine system too. Supplementation can increase brain creatine, though the response appears more complicated than loading skeletal muscle. 2024 systematic review
Where things become difficult is translating that mechanism into noticeable cognitive outcomes.
A 2024 meta-analysis of 16 randomized trials involving 492 adults found improvements in memory, some measures of attention time, and processing speed. It did not find significant improvements in overall cognition or executive function, and confidence in the findings differed by outcome.
Another systematic review reached a more cautious conclusion, describing the cognitive findings as equivocal despite evidence that creatine can increase brain creatine. Read the review.
That disagreement is exactly why brain claims deserve more restraint than muscle claims.
A useful way to read any claim about creatine and the brain is to ask which cognitive ability actually improved. Better performance on a memory test does not automatically mean better concentration at work, greater productivity, higher intelligence or a noticeable everyday “brain boost.” Those are different claims requiring their own evidence.
What about sleep deprivation?
Creatine is particularly interesting when the brain is under unusually high energetic stress, including sleep deprivation.
Positive findings in those conditions deserve investigation. They do not mean creatine can substitute for sleep or that an experimental high-dose protocol should automatically become a normal “brain dose.”
Bottom line: memory has the most encouraging signal so far. Claims about universal focus, productivity, broad cognitive enhancement or prevention of neurodegenerative disease go beyond the current evidence.
The brain research is real. The marketing version is simply moving faster.
Creatine for women: the evidence is better than the old stereotype—and narrower than the new hype
Creatine spent years wrapped in male bodybuilding culture.
Now the pendulum is swinging hard in the other direction, with creatine sold to women for hormones, mood, menopause, muscle and cognition all at once.
The interesting evidence is narrower—and more useful—than that marketing bundle.
Women who train
Women use the same phosphocreatine energy system and can increase tissue creatine through supplementation. Female-specific research, however, is smaller than the overall creatine literature. We should not turn “women can benefit” into “women always respond better.”
After menopause
This is one area where newer research genuinely strengthens the case.
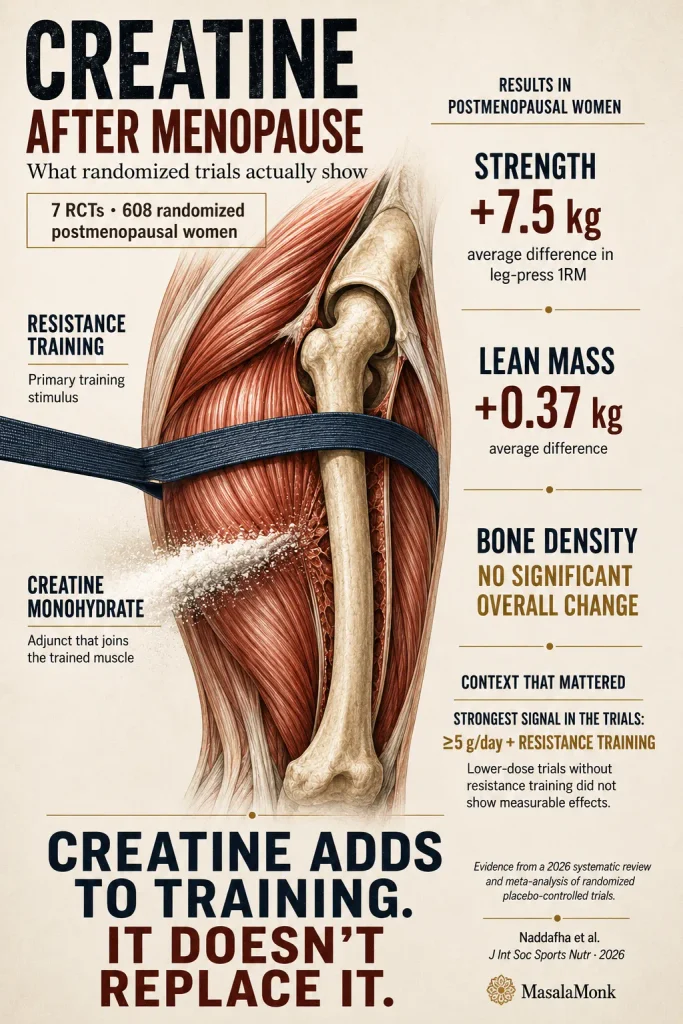
A 2026 systematic review and meta-analysis included seven randomized trials and 608 postmenopausal women overall. Five lean-mass comparisons involving 338 participants favoured creatine by about 0.37 kg, while three studies involving 111 participants contributed to the leg-press analysis, which favoured creatine by roughly 7.5 kg.
The clearest benefits appeared when at least 5 g/day was paired with resistance training. Overall bone density did not significantly improve. Most studies carried at least some risk-of-bias concerns, so the findings are encouraging rather than permission to attach every menopause claim imaginable to creatine.
That is a much stronger reason for interest than vague promises of “hormonal support.”
If the main reason for considering creatine after menopause is bone density, the current trials do not offer the same support they do for strength and lean mass. In practice, the evidence points toward creatine as a potential addition to resistance training—not as a stand-alone treatment for the many changes grouped under “menopause.”
Creatine as you get older
The resistance-training partnership also matters in older adults.
A 2025 systematic review and meta-analysis found that creatine added to resistance training improved lower-body strength and lean tissue mass compared with resistance training plus placebo in older adults.
That makes creatine an interesting adjunct when preserving strength and function matters increasingly with age.
No scoop, however, reproduces what progressive strength training asks your muscles, bones and nervous system to do.
Vegetarians and vegans may start from a different baseline
Dietary creatine comes mainly from animal foods.
People eating little or no meat may therefore begin with lower creatine stores, leaving more room for those stores to rise after supplementation. A systematic review of vegetarian and omnivorous athletes found that tissue creatine often increased more in vegetarian participants, while studies were mixed on whether their exercise-performance gains were greater than those of omnivores.
That does not guarantee that every vegetarian or vegan will gain more strength, muscle or cognitive benefit than every omnivore.
Lower baseline stores help explain why biological responses can differ. They do not guarantee a particular visible result.
For healthy adults taking commonly studied doses, creatine has an unusually large safety literature for a sports supplement.
A 2025 safety analysis covering 685 human creatine trials compared reported side effects across 12,839 creatine participants and 13,452 placebo participants. Overall participant-level side-effect reporting was 4.60% with creatine and 4.21% with placebo, a difference that was not statistically significant.
A separate 2026 study-level analysis across 684 randomized trials asked a different question: whether adverse effects showed a meaningful pattern as creatine dose or duration increased. Reported effects were generally infrequent and mild, and the analysis did not identify a consistent clinically meaningful dose- or duration-response pattern versus placebo.
That combination is reassuring: symptoms occur in both supplement and placebo groups, and the broad randomized-trial literature does not show the escalating safety pattern often implied online. It is still not evidence that every possible person in every medical situation should take creatine without thought.
The placebo comparison matters because symptoms can appear during a trial even when creatine is not the cause. Therefore, a headache, stomach complaint or other symptom beginning after a new supplement deserves attention—but timing alone cannot establish causation. That distinction is useful well beyond creatine when evaluating supplement side-effect stories.
For a symptom-by-symptom discussion of gastrointestinal complaints, water retention and other reported effects, see our dedicated guide to creatine side effects.
Creatine, creatinine and your kidneys
Imagine you have been taking creatine for several months.
You get routine blood work.
Your creatinine comes back higher.
After years of hearing that creatine “damages kidneys,” connecting those dots would be easy.
The test itself makes the story more complicated.
Creatine and creatinine are related, but not interchangeable
Creatine is the compound being supplemented.
Creatinine is a breakdown product.
Serum creatinine is also commonly used to estimate kidney filtration.
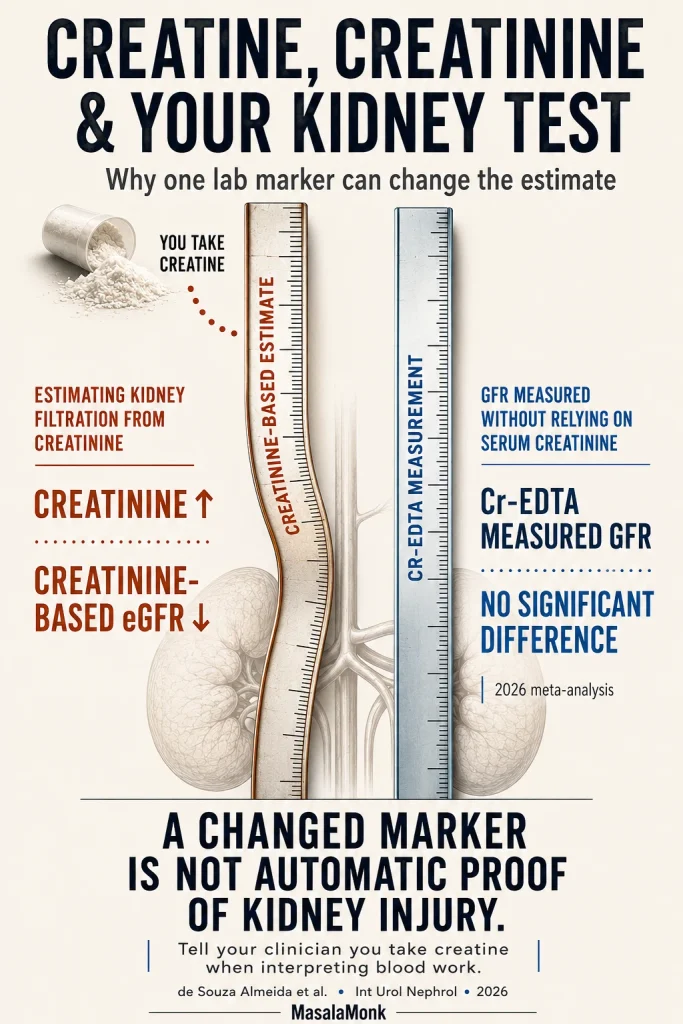
If creatine supplementation changes creatinine production or metabolism, a kidney estimate that relies on creatinine can move even when actual filtration has not deteriorated in the same way.
Two 2026 analyses help show why the blood test can look worse even when kidney filtration has not necessarily become worse.
One meta-analysis of randomized trials found that supplementation increased serum creatinine by an average of about 0.13 mg/dL but did not find significant differences in urea or estimated GFR overall.
A second 2026 kidney-health meta-analysis went a step further. Across 26 studies, serum creatinine increased and creatinine-based GFR estimates decreased. But when filtration was assessed using Cr-EDTA, there was no statistically significant difference between creatine and control groups. Other kidney markers including albuminuria and proteinuria were also not significantly different.
The practical lesson: a creatinine-based estimate can be affected by something that changes creatinine metabolism. A higher result deserves clinical interpretation, but it is not automatic proof that creatine injured the kidneys.
There is an important measurement lesson here: when a supplement can change the marker used in an equation, the estimated result can move partly because the marker moved. That is why the directly measured filtration findings matter—they help separate a change in creatinine from evidence that kidney filtration itself deteriorated in the same way.
So should you ignore a high creatinine result?
No.
A changed laboratory result deserves appropriate interpretation. Tell the clinician reviewing your blood work that you take creatine. They can consider supplementation alongside your medical history, other laboratory markers and—when clinically appropriate—measures that are less dependent on creatinine.
The point is not to self-diagnose yourself as healthy. It is also not to diagnose yourself with creatine-induced kidney damage from a single number.
What if you already have kidney disease?
That is a different situation from a healthy adult taking a sports supplement.
Research in people with kidney disease is much more limited, and Mayo Clinic recommends that people with kidney disease discuss creatine with their healthcare team.
Does creatine cause hair loss?
This rumour survived because there was just enough science underneath it to sound convincing.
Where the worry came from
A small 2009 study in rugby players reported changes in dihydrotestosterone (DHT) during creatine supplementation.
DHT is relevant to androgenetic hair loss in genetically susceptible people.
A plausible concern therefore emerged:
creatine → higher DHT → hair loss.
One important detail disappeared as the story travelled around gyms and the internet.
The study did not measure hair loss.
Then researchers measured the hair
In 2025, researchers conducted a randomized controlled trial specifically examining creatine and hair-follicle health.
Forty-five resistance-trained men aged 18–40 were assigned to 5 g/day of creatine monohydrate or placebo for 12 weeks.
Researchers measured total testosterone, free testosterone, DHT, hair density, follicular-unit count and cumulative hair thickness.
They found no significant differences in DHT or measured hair outcomes between creatine and placebo. Read the randomized trial.
That is much more direct evidence than the creatine-hair debate had previously.
It is also one 12-week trial in young resistance-trained men. It cannot answer every possible lifetime question about every population.
But we can no longer accurately say that nobody has directly tested creatine and hair loss. They have. In that first direct randomized trial, the results did not support the claim.
This creatine–hair-loss story illustrates a broader evidence rule: changing a hormone associated with an outcome is not the same as measuring the outcome itself. A 2009 DHT finding raised a reasonable question; years later, researchers finally tested hair density and follicular measures directly. Surrogate signals and real-world outcomes should not be treated as interchangeable.
“But I started creatine and saw more hair in the shower”
That can be genuinely unnerving.
The difficult question is not whether you saw more hair. The difficult question is whether creatine caused it.
Hair shedding can change with genetics, age, illness, stress, calorie restriction, nutritional problems, medications and ordinary variation. When a new supplement and a new symptom appear close together, connecting them is natural.
Anecdotes are useful for spotting questions worth studying. Controlled trials are what help us test causation.
Does creatine dehydrate you?
Creatine increases water associated with muscle.
That fact somehow became a rule that creatine users must spend all day chasing a giant water target.
You do not need a special four- or five-litre creatine quota.
Hydration needs vary with body size, climate, sweat rate, exercise volume, diet, health and individual physiology.
If you are training outside in hot, humid weather, your fluid and electrolyte needs may be substantial because you are losing more fluid through sweat.
Creatine itself does not create an arbitrary universal number everyone must drink. Controlled evidence has not supported the old claim that recommended creatine use inherently causes dehydration or muscle cramping; a 2025 safety review found no significant adverse effect on hydration or thermoregulation in the controlled literature it assessed.
Hydrate according to your actual circumstances rather than a creatine-specific internet ritual.
The same daily creatine dose can accompany completely different hydration needs. An air-conditioned rest day and a long outdoor session in hot, humid weather may require very different amounts of fluid and electrolytes—not because the creatine changed, but because sweat loss, exercise and environment did.
If creatine bothers your stomach
Gastrointestinal discomfort is one of the more plausible practical complaints, particularly when somebody suddenly tries to consume a large loading dose.
Before spending more money on an exotic creatine form, simplify.
skip loading;
keep each dose smaller;
split loading doses through the day;
take creatine with food if that feels better;
check whether your supplement contains sweeteners, stimulants or other ingredients that may be responsible.
The traditional loading protocol itself divides approximately 20 g across four doses rather than taking it all at once. NIH dosing guidance.
For many people, the stomach-friendly solution is simply 3–5 g/day without loading.
The easiest way to make creatine effective may be to make it boring. Attach the daily dose to a routine you already remember rather than building an elaborate supplement schedule around the clock. Consistency is easier to maintain when creatine becomes ordinary, not another task that requires perfect workout timing.
Is 3 grams enough?
For many people, yes.
The NIH describes non-loading research protocols around 3–6 g/day, including weight-adjusted approaches of roughly 0.03–0.1 g/kg/day, used over several weeks. See the dosing overview.
That does not mean the average recreational user needs a calculator. A consistent 3–5 g/day is much easier to follow than turning a simple supplement into body-weight mathematics.
Five grams is convenient. It is not a magical biological threshold.
Do you need to load?
No.
Loading mostly answers: How quickly do I want my muscle creatine stores to rise?
It does not answer: Will creatine eventually work if I don’t load it?
If you have a competition or a specific short timeline, reaching saturation quickly may matter. For a long-term gym routine, a slower daily approach is perfectly reasonable.
The real trade-off with a creatine loading phase is convenience. Faster saturation requires several larger doses across the day and can be harder on some stomachs; meanwhile, gradual daily dosing asks for more patience but less complexity. If reaching high stores quickly solves no real problem for you, speed itself may offer little practical value.
Before or after your workout?
For most users, the available timing literature does not support chasing a precise pre- versus post-workout window. Methodological limitations still prevent a firm recommendation for one ideal strategy. Review of creatine timing around exercise.
A 2026 randomized crossover pilot in 11 physically active men reported better acute lifting performance when creatine was consumed before exercise rather than during or after it. Interesting? Certainly. Enough to establish a new universal dosing rule? No—the authors themselves describe the findings as exploratory and in need of confirmation in larger studies.
Regular intake remains the more useful priority.
Morning works. Lunch works. After training works.
Choose a routine you will remember.
What about rest days?
Take your normal dose.
Creatine works through elevated tissue stores. Your muscles do not reset because today happens to be a rest day.
You forgot yesterday
Resume your normal amount.
There is no need to double today’s scoop or restart loading. One missed day does not erase weeks of accumulated muscle creatine.
Do you need to cycle creatine?
Routine creatine cycling has no established evidence-based requirement.
Gym culture borrowed “cycling” language from substances where cycling has entirely different biological reasons. Creatine is not an anabolic steroid.
You do not need to taper, and there is no recognised creatine withdrawal syndrome.
Muscle that you genuinely built through months of training does not suddenly vanish because the supplement left your shaker.
Can you take creatine with coffee?
For ordinary coffee drinkers taking normal creatine doses, the evidence does not justify a blanket rule that caffeine and creatine must always be separated.
The reason the internet argument sounds contradictory is that the small research base has tested different ways of combining them. Two systematic reviews each identified only about ten relevant studies. One review found that acute caffeine taken after a creatine-loading phase generally did not erase caffeine’s ergogenic effect, whereas chronic caffeine consumed throughout loading produced mixed results: some studies suggested interference, several found no interaction and one reported synergy.
A second systematic review similarly found that acute caffeine after loading produced an additional ergogenic effect over creatine alone in three of five studies, while daily caffeine during loading produced an additive benefit in only one of five studies.
That is not enough evidence to invent a mandatory two-, four- or six-hour separation rule. Your morning coffee does not automatically cancel your creatine, but chronic high-caffeine use during a loading phase is less settled. If combining large doses makes your stomach miserable, separating or simplifying them is sensible.
When you see the claim that “caffeine blocks creatine,” ask how caffeine was actually used. Acute caffeine after a creatine-loading period and chronic high-caffeine intake during loading are different research situations, and they have not produced identical results. That distinction is more useful than inventing a universal coffee-versus-creatine rule.
Which type of creatine should you buy?
This is the easiest part.
Creatine monohydrate.
It has the deepest evidence base, a long history of use and usually the lowest price.
Marketed with advantages that have not convincingly beaten monohydrate in evidence
Buffered creatine
No established practical superiority over monohydrate
How common creatine forms compare with the monohydrate evidence base.
The NIH likewise notes that more expensive alternatives have not been proven superior for increasing muscle creatine, digestibility, stability or safety.
Once you have chosen creatine monohydrate, product quality matters more than increasingly exotic formulation language. For athletes subject to drug testing, independent sport certification may be especially valuable because contamination with prohibited substances is a different problem from whether creatine itself is effective.
“Micronized” is not a different type of creatine
Despite the label, micronized creatine is still creatine monohydrate.
The term simply means the powder has been processed into smaller particles, which may help it disperse more easily in liquid without changing the underlying form of creatine.
Product quality matters more than impressive wording
Choose a reputable manufacturer.
If you compete in tested sport, independent sport certification may be particularly valuable because contamination with prohibited substances is a separate issue from whether creatine itself works.
You do not need a proprietary “ultra-anabolic matrix.” You need the product to contain what the label says it contains.
Who should be more cautious?
Healthy-adult evidence cannot automatically be transplanted into every population.
Known kidney disease
Discuss creatine with the healthcare team managing your kidney health rather than extrapolating from healthy-adult trials. Mayo Clinic creatine guidance.
Pregnancy and breastfeeding
Creatine is being investigated in maternal and fetal physiology, but routine supplementation during pregnancy and breastfeeding does not have the depth of human safety evidence available for adult sports supplementation. A recent safety review notes that evidence remains lacking in pregnancy, while the NIH LactMed creatine monograph reports that human milk levels after supplementation have not been studied and advises avoiding supplementation unless prescribed until more data are available.
Individual clinical advice is more appropriate here than extrapolating from gym studies.
Adolescents
It is no longer accurate to say that creatine has never been studied in teenagers.
A 2026 systematic review found five eligible studies and reported no consistent short-term kidney, liver or cardiometabolic safety signals during the study periods. It also emphasized how limited the evidence remains and the need for larger studies with longer follow-up.
So the evidence is not zero. It is also nowhere near as deep as the adult literature.
Medical conditions and medications
If you are managing a medical condition or take medication that affects kidney function, fluid balance or another relevant system, disclose supplement use to your healthcare professional.
“Available without a prescription” does not mean “irrelevant to medical care.”
Yes. Protein and creatine do different jobs, and there is no reason they have to live in separate drinks. If putting both in the same shake helps you remember your creatine, that is a perfectly good routine. For broader nutrition context, our guide to what protein does explains the role of dietary protein in more detail.
Can I take creatine on an empty stomach?
Yes, if you tolerate it. When your stomach dislikes it, take creatine with food. There is no benefit to making a simple supplement uncomfortable.
Is creatine a steroid?
No. Creatine is not an anabolic steroid. It is a compound your body naturally makes and uses in the creatine–phosphocreatine energy system; supplementation increases creatine availability rather than working through the hormonal mechanisms that define anabolic steroids.
Training, sport and long-term use
What if I take creatine but don’t work out?
Your tissue creatine stores can still increase. But many of the outcomes people want—more strength, more muscle and better training performance—depend on actually creating a training stimulus. The scoop cannot perform the repetitions for you. See the strength evidence for the training context.
Can runners take creatine?
Yes. The better question is whether it suits the runner’s goals. Someone who strength trains, sprints or performs repeated high-intensity intervals may have more reason to use creatine than someone concerned only with long-duration endurance. The dedicated endurance meta-analysis found no significant overall performance benefit in trained populations; see the full creatine-for-runners and endurance discussion.
How long can you take creatine?
There is no evidence-based rule telling healthy adults that creatine must be stopped after an arbitrary number of weeks. Mayo Clinic currently describes recommended oral doses as likely safe for many people for up to five years. That reflects the duration supported by available longer-term evidence; it does not mean creatine suddenly becomes unsafe on the first day of year six.
The 2026 analysis of 684 randomized trials also found no consistent pattern of clinically meaningful adverse effects increasing with dose or duration at the study level. Science cannot give us lifetime data on every possible user, but the available evidence does not support the familiar rule that healthy adults must routinely cycle off because continuous creatine inevitably becomes dangerous. For the broader context, see the creatine safety section.
So, is creatine worth taking?
Creatine has travelled through two opposite reputations.
First it was the suspicious bodybuilding powder supposedly responsible for cramps, kidney damage and baldness.
Now it is in danger of becoming a universal wellness supplement for muscle, menopause, memory, mood, longevity and brain optimisation.
Neither version fits the evidence particularly well.
Creatine is excellent at a fairly specific job. It supports the body’s rapid-energy system, and that translates into strong evidence for repeated high-intensity performance, greater strength gains and modestly greater lean-mass gains alongside resistance training.
The newer possibilities—in cognition, aging and postmenopausal women—deserve curiosity without being promoted to certainty before the evidence gets there.
And ordinary creatine use is much less complicated than supplement culture has made it.
For a healthy adult who decides it fits their goals:
Use creatine monohydrate.
Take around 3–5 grams each day.
Be consistent.
Then put considerably more thought into your training, food and sleep than into the timing of the scoop.
Key research used for this September 2026 update
How this guide was researched: priority was given to systematic reviews, meta-analyses, randomized controlled trials and major evidence-based clinical or sports-nutrition resources. Community questions were useful for identifying what readers are confused or worried about, but anecdotes were not treated as proof of benefit or harm. Where individual studies carried important limitations, we also considered sample size, study duration, risk of bias and relevant author disclosures when deciding how strongly to describe a finding.
Are you looking to transform your glutes from flat to fab? Chiara Pugliesi’s video, “How I INSANELY Grew My Glutes From Pancake To Shelf! Workouts, Nutrition & more tips,” is a must-watch. This post will delve into the insights shared in the video, providing a detailed overview and additional information to enhance your understanding of glute growth.
Chiara Pugliesi shares her personal journey and tips on how she successfully grew her glutes. The video covers various aspects, including diet, the use of creatine, specific workouts and exercises, and the importance of recovery. She provides a timestamp for each section, making it easy for viewers to navigate through the topics.
Key Takeaways
Diet: Chiara emphasizes the importance of a proper diet and shares her personal dietary choices.
Creatine: She discusses the role of creatine in muscle building.
Workouts and Exercises: The video provides detailed information about the workouts and exercises that helped her achieve significant glute growth.
Recovery: Chiara highlights the importance of recovery in muscle development.
Yes, additional resources and links are provided in the video description.
Is the video easy to navigate?
Yes, the video provides timestamps for each section, ensuring easy navigation.
Conclusion
Chiara Pugliesi’s comprehensive guide on glute growth is a valuable resource for anyone looking to enhance their glutes. The detailed insights, additional resources, and FAQs covered in this post aim to equip you with the necessary information to embark on your glute growth journey effectively.
Blog Tags
Glute Growth, Glute Activation, Glute Building Tips, Glute Exercises, Creatine, High Protein Meals, Bulking Meals, Bret Contreras, Smith Machine Workout, Best Glute Exercises, Lower Glute Workout, Upper Glute Exercises, Banded Workouts, Gym Motivation
Creatine, a naturally occurring compound found in small amounts in certain foods and synthesized in the body, has become one of the most popular and widely researched supplements in the fitness world. Its benefits range from improved athletic performance to potential neurological advantages. However, with popularity comes misconceptions. This comprehensive guide aims to cover everything you need to know about creatine, ensuring you’re well-informed and can make the best decisions for your health and fitness goals.
1. What is Creatine?
Creatine is a molecule produced in the body and stored primarily in the muscles. It provides a quick source of energy during short bursts of high-intensity activity, like lifting weights or sprinting.
2. Benefits of Creatine
Enhanced Athletic Performance: Creatine supplementation can increase creatine phosphate stores in the muscles, providing more immediate energy and potentially improving exercise performance.
Muscle Growth: Creatine has been shown to increase the water content in muscle cells, potentially leading to muscle growth. Additionally, it may boost the levels of certain proteins that contribute to muscle growth.
Brain Health: Preliminary research suggests that creatine might have potential benefits for brain health and could play a role in preventing neurological diseases, though more research is needed in this area.
3. Creatine Side Effects and Misconceptions
Water Retention: One of the most common side effects associated with creatine is water retention, leading to a temporary increase in weight. This is not fat gain but an increase in the water content of the muscles.
Stomach Discomfort: Some people might experience stomach pain, diarrhea, or nausea when consuming creatine, especially in larger doses. It’s often recommended to split the dosage throughout the day or opt for micronized creatine, which may reduce these side effects.
Mood and Mental Health: There’s limited evidence suggesting a link between creatine and mood swings or mental health issues. Most research indicates that creatine is safe and might even have neurological benefits, but always consult with a healthcare professional if you have concerns.
Dehydration Myth: A widespread misconception is that creatine can cause dehydration or cramps. While creatine does draw water into the muscles, there’s no scientific evidence to suggest it leads to dehydration or cramps. In fact, staying hydrated while using creatine is beneficial.
While creatine might lead to an initial weight gain due to water retention, it’s essential to differentiate between this and fat gain. Over time, with consistent training, the increase in muscle mass might contribute to weight gain, but this would be lean muscle, not fat.
5. Different Forms of Creatine
Raw Creatine Powder: This is pure, unflavored creatine without any additives. It’s essential to ensure its purity and source.
Micronized Creatine: This form of creatine has been processed to reduce the particle size, potentially improving its solubility in water and absorption in the body.
Creatine Monohydrate: The most researched form of creatine and considered the gold standard. Most studies on creatine’s benefits use this form.
6. Dosage and Recommendations
A common dosing regimen for creatine is the “loading phase,” where one takes 20 grams per day (split into 4 doses) for 5-7 days, followed by a “maintenance phase” of 3-5 grams per day. However, the loading phase isn’t mandatory, and one can take 3-5 grams daily without any loading.
FAQs about Creatine
1. What is the primary function of creatine in the body? Creatine serves as a quick energy source for the muscles, especially during short bursts of high-intensity activities. It helps regenerate a molecule called adenosine triphosphate (ATP), which is the primary energy currency of the cell.
2. How does creatine contribute to muscle growth? Creatine increases the water content in muscle cells, leading to a temporary increase in muscle size. Additionally, it may boost levels of certain proteins that promote muscle growth and enhance overall muscle protein synthesis.
3. Are there any neurological benefits associated with creatine supplementation? Preliminary research suggests that creatine might offer potential benefits for brain health, possibly playing a role in preventing certain neurological diseases. However, more extensive research is needed to confirm these findings.
4. How can I reduce stomach discomfort when taking creatine? To minimize stomach discomfort, consider splitting your creatine dosage throughout the day. Opting for micronized creatine, which has smaller particle sizes, can also improve its solubility and reduce the chances of stomach issues.
5. Is the weight gain from creatine due to fat accumulation? No, the initial weight gain from creatine is primarily due to water retention in the muscles. Over time, with consistent training, there might be an increase in muscle mass, but this would be lean muscle, not fat.
6. Which form of creatine is considered the most effective? Creatine monohydrate is the most researched form and is often considered the gold standard due to its proven benefits and safety profile.
7. Do I need to go through a “loading phase” when starting creatine? While a loading phase can saturate the muscles with creatine faster, it’s not mandatory. Many individuals take a consistent daily dose of 3-5 grams without any loading and still experience the benefits.
8. Can I take creatine with other supplements? Yes, creatine can be combined with other supplements. However, it’s essential to consult with a healthcare professional to ensure there are no interactions or contraindications based on your specific health profile.
Conclusion
Creatine is a powerful and well-researched supplement with a range of benefits for athletes, bodybuilders, and potentially even for brain health. As with any supplement, it’s crucial to be informed, understand potential side effects, and consult with a healthcare professional. By dispelling myths and focusing on science, we can make the most of what creatine has to offer.