Updated:
This guide has been substantially revised to include newer evidence on creatine and kidney function, hair loss, strength, body composition, cognition, postmenopausal women and safety.
Creatine used to be easy to understand. Lifters took it because it helped them train harder and get stronger.
Now someone is taking it for menopause. Someone else is worried it will ruin their kidneys. And someone who has never touched a barbell is considering it for their brain while quietly wondering what that daily scoop might do to their hairline.
Creatine deserves neither the old fear nor the new mythology.
Creatine: the short answer
If you are standing in front of a tub wondering what matters, start here.
- Creatine works best where the evidence is deepest: resistance-training strength, repeated high-intensity exercise and somewhat greater lean-mass gains alongside training.
- Creatine monohydrate is the default form to buy. More expensive alternatives have not convincingly shown that they work better.
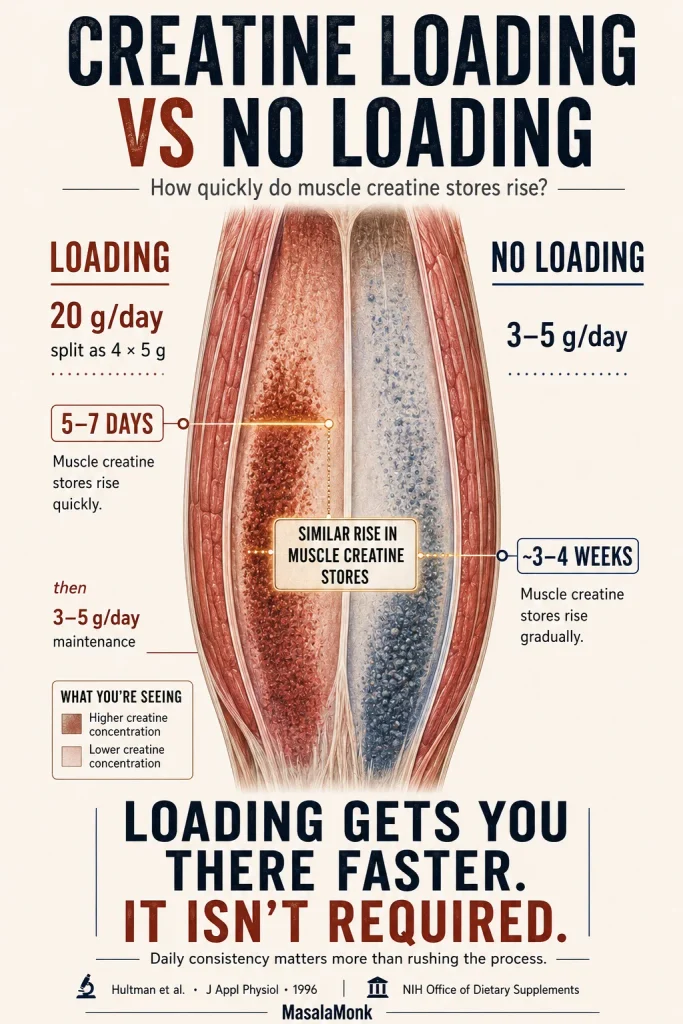
- For most healthy adults who choose to supplement, 3–5 g/day is a simple routine. Loading is optional: about 20 g/day split into four doses for 5–7 days raises stores faster, while a smaller daily dose gets there more gradually.
- Consistency matters more than a perfect workout window. Rest days use the same daily routine, and routine cycling is not established as necessary.
- Early scale weight can rise. Water associated with muscle can contribute, so a quick increase does not tell you that you gained the same amount of fat—or pure new muscle.
- The healthy-adult safety literature is reassuring, while newer claims deserve different levels of confidence. Creatinine-based kidney tests can be affected by creatine use; direct hair-loss evidence is reassuring; memory and postmenopausal findings are promising but narrower than the marketing often suggests.
Creatine monohydrate remains the most studied form, and the NIH Office of Dietary Supplements summarizes the common loading and non-loading approaches used in research.
What is creatine actually good for?
The internet tends to flatten very different claims into one enormous list of “creatine benefits.”
The evidence falls into very different tiers.

| Outcome | Where the evidence stands |
|---|---|
| Strength with resistance training | Strong |
| Repeated high-intensity exercise | Strong |
| Additional lean-mass gains with resistance training | Strong |
| Lean mass and strength in some older adults alongside resistance training | Good evidence |
| Lean mass and strength after menopause, particularly with resistance training | Promising / increasingly supported |
| Memory and some cognitive outcomes | Promising, but mixed overall |
| Long-duration endurance performance | No meaningful overall benefit established |
| Soreness and faster recovery from every workout | Mixed |
| Direct fat loss | Not established |
That difference between established, promising and plausible matters throughout this subject.
What creatine does inside your muscles
Your body already makes creatine, and foods such as meat and fish provide additional dietary creatine.
Most of the body’s creatine is stored in skeletal muscle. Some exists as phosphocreatine, which helps regenerate ATP when energy demand rises very quickly.
You do not need the biochemistry-textbook version to understand the practical consequence.
Think of phosphocreatine as part of a small, rapidly available energy reserve. Increasing muscle creatine gives that system more capacity.
That becomes particularly useful when the work is hard, short and repeated: another heavy set, another sprint, another explosive effort.
What will you actually notice after starting creatine?
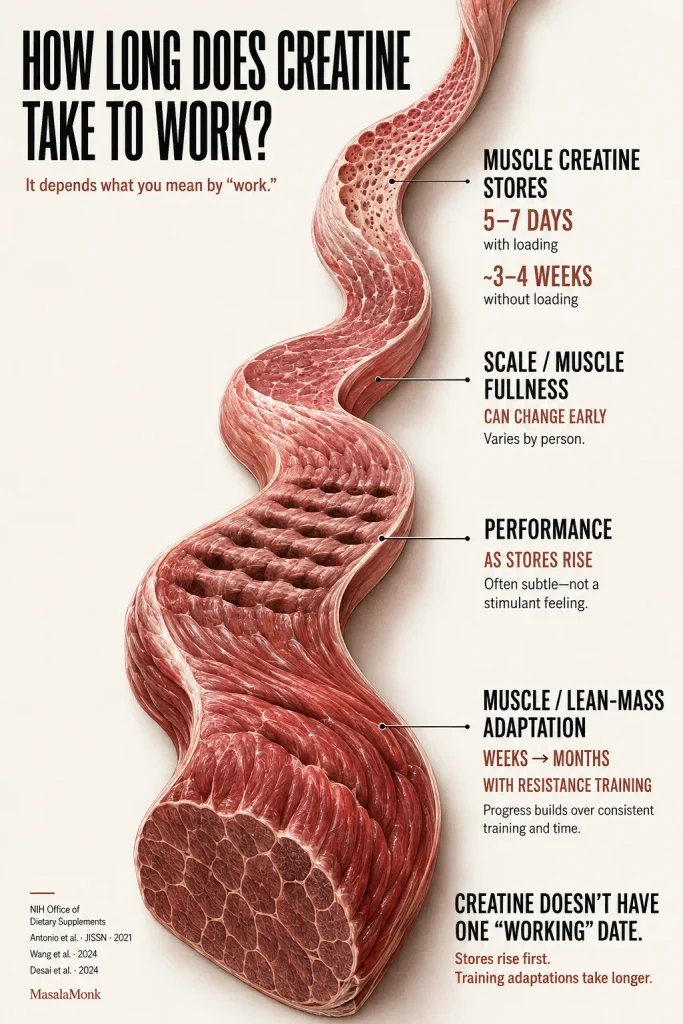
Imagine you begin taking 3–5 g of creatine monohydrate every day.
Your muscle creatine stores gradually rise. Loading makes that happen faster; smaller daily dosing gets there more gradually. NIH Office of Dietary Supplements
The scale may move before your gym numbers do.
Your muscles may look a little fuller.
And you may feel…exactly the same.
That last part catches people out. Creatine is not caffeine. There is no required buzz or dramatic moment when it “kicks in.” Its benefit often appears in repeated work: maintaining performance a little better, completing slightly more useful training, or accumulating better sessions over time.
If you have taken creatine for three weeks and are thinking, I can’t feel anything, that does not automatically mean you need more.
What about over months rather than days?
This is where supplementation and training become much more interesting.
A 2024 meta-analysis of resistance training and body composition found that adults under 50 who combined creatine with resistance training gained about 1.14 kg more lean body mass than those doing resistance training without creatine. Small favourable changes in body-fat measures were also reported.
That is not evidence that one scoop manufactures a kilogram of muscle. It is evidence that creatine can help resistance training produce somewhat greater adaptations over time.
Where creatine earns its reputation
Strength
This remains one of the clearest cases for taking creatine.
A 2025 systematic review and meta-analysis of 69 studies involving 1,937 adults separated several common strength tests instead of collapsing them into one upper- or lower-body number. Compared with placebo, creatine plus resistance training produced statistically significant pooled improvements in bench/chest press strength (+1.43 kg) and squat strength (+5.64 kg).
The same analysis did not find statistically significant overall differences for leg press or handgrip strength. It also reported significant improvements in vertical jump and Wingate peak power, reinforcing that creatine’s performance signal depends partly on the outcome being tested.
Those values are pooled group averages, not predictions for your next personal record. Different exercises, populations, training programs and study designs produce different estimates. Overall, resistance training tends to produce somewhat greater strength and power gains when creatine is added, but there is no single universal “creatine strength increase.”

Repeated high-intensity exercise
Creatine also performs well in activities built around short, hard efforts with limited recovery:
- resistance training;
- repeated sprints;
- explosive efforts;
- sports involving repeated bursts of high power.
That is exactly where the phosphocreatine system is most relevant.
Lean mass—if there is a training stimulus
Creatine can increase water associated with muscle fairly quickly. Over longer resistance-training interventions, it can also help produce greater lean-mass gains. See the 2024 body-composition meta-analysis.
Both are real.
Two popular summaries are both too simple: “Creatine gains are just water” and “every kilogram of extra lean mass is pure new muscle.” The early and long-term changes are not the same thing.
What creatine is less impressive at
A useful creatine guide should also tell you where enthusiasm needs cooling.
Long-duration endurance
Creatine is particularly good at supporting intense, repeatable muscular work. It has not shown the same clear advantage for prolonged endurance performance.
A systematic review and meta-analysis in trained participants found no meaningful overall endurance-performance benefit from creatine monohydrate.
A 2026 scoping review of endurance and mixed-sport research adds a useful distinction. The more favourable signals tended to appear in selected contexts involving repeated high-intensity efforts, sprint finishes and power-endurance demands, while aerobic outcomes remained limited or inconsistent.
That is why “creatine for runners” is not a yes-or-no question. A distance athlete who also strength trains, attacks hills, performs repeated hard surges or relies on a finishing sprint has different demands from someone concerned only with prolonged steady-state endurance. Creatine is not a proven general endurance booster; its physiological fit is stronger when the event temporarily becomes intense.

Direct fat loss
Creatine is not a fat burner.
Resistance-training studies sometimes show favourable body-composition changes when creatine is added, but that should not be rewritten as “creatine melts fat.” Diet, energy intake, daily activity and training remain the important variables if fat loss is the goal.
Soreness and recovery
Recovery research is much less consistent than the strength literature.
One systematic review found no meaningful improvements in soreness, muscle-strength recovery, inflammation or range of motion after muscle-damaging exercise, although creatine kinase was reduced at one time point. Other meta-analytic work has found potentially favourable changes in some muscle-damage markers but substantial heterogeneity.
Creatine may eventually prove useful for particular recovery outcomes. It is not something I would buy primarily because I want tomorrow’s leg-day soreness to disappear.
The scale went up. Did creatine make you fat?
You start creatine on Monday.
By the weekend, the scale is 800 grams higher.
If you are trying to lose fat, that can be unsettling.
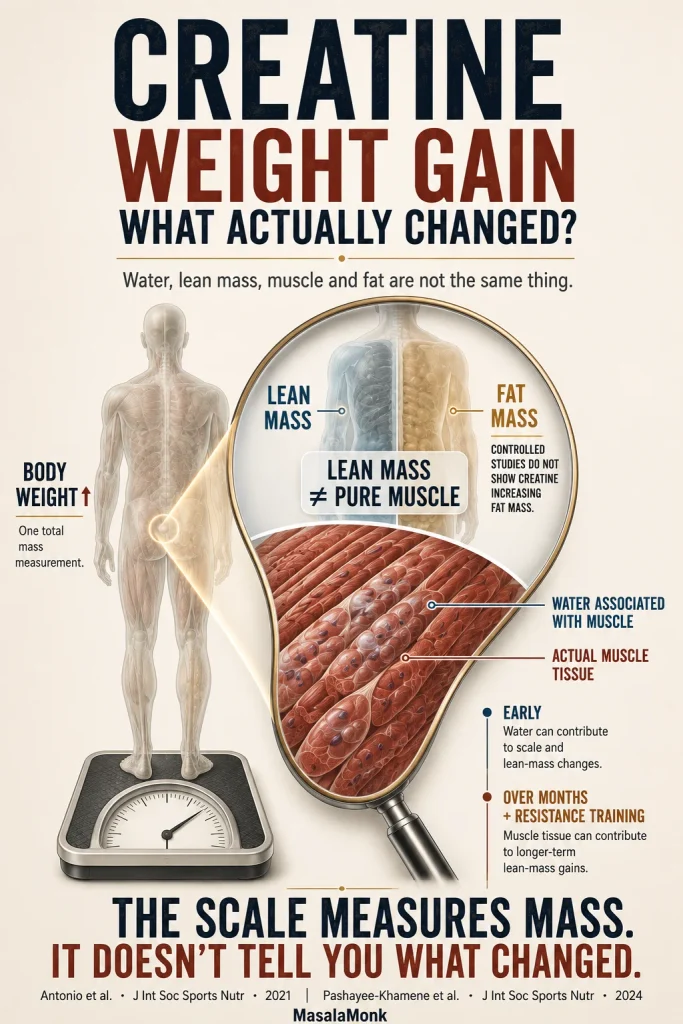
But the scale cannot tell you whether that change came from body fat, muscle tissue, glycogen, water, food and fluid still in the digestive system, or several of these together.
Creatine increases muscle creatine storage, and water accompanies that process. An early increase in body mass can therefore happen far faster than you could plausibly build the same amount of new muscle tissue.
It is also not the same as gaining 800 grams of fat.
Water, lean mass and muscle are different things
| What you notice | What may be happening |
|---|---|
| Scale rises relatively quickly | Increased water can contribute |
| Muscles look somewhat fuller | More intramuscular water may contribute |
| A scan reports more lean mass | Lean mass includes water and other non-fat tissues |
| Strength and lean mass increase over months | Training adaptations and creatine can both contribute |
| Body fat | Creatine does not simply turn into fat |
The opposite mistake happens too. If a scan reports an extra kilogram of “lean mass,” that should not automatically be described as a kilogram of newly built muscle fibre.
If the water part is what worries you, that is a separate question from scale weight: see creatine, hydration and cramps.
Creatine and the brain: interesting science, incomplete answers
There is real biology behind the brain question.
The brain has enormous energy demands and uses a creatine-phosphocreatine system too. Supplementation can increase brain creatine, though the response appears more complicated than loading skeletal muscle. 2024 systematic review
Where things become difficult is translating that mechanism into noticeable cognitive outcomes.
A 2024 meta-analysis of 16 randomized trials involving 492 adults found improvements in memory, some measures of attention time, and processing speed. It did not find significant improvements in overall cognition or executive function, and confidence in the findings differed by outcome.
Another systematic review reached a more cautious conclusion, describing the cognitive findings as equivocal despite evidence that creatine can increase brain creatine. Read the review.
That disagreement is exactly why brain claims deserve more restraint than muscle claims.

What about sleep deprivation?
Creatine is particularly interesting when the brain is under unusually high energetic stress, including sleep deprivation.
Positive findings in those conditions deserve investigation. They do not mean creatine can substitute for sleep or that an experimental high-dose protocol should automatically become a normal “brain dose.”
Bottom line: memory has the most encouraging signal so far. Claims about universal focus, productivity, broad cognitive enhancement or prevention of neurodegenerative disease go beyond the current evidence.
The brain research is real. The marketing version is simply moving faster.
Creatine for women: the evidence is better than the old stereotype—and narrower than the new hype
Creatine spent years wrapped in male bodybuilding culture.
Now the pendulum is swinging hard in the other direction, with creatine sold to women for hormones, mood, menopause, muscle and cognition all at once.
The interesting evidence is narrower—and more useful—than that marketing bundle.
Women who train
Women use the same phosphocreatine energy system and can increase tissue creatine through supplementation. Female-specific research, however, is smaller than the overall creatine literature. We should not turn “women can benefit” into “women always respond better.”
After menopause
This is one area where newer research genuinely strengthens the case.
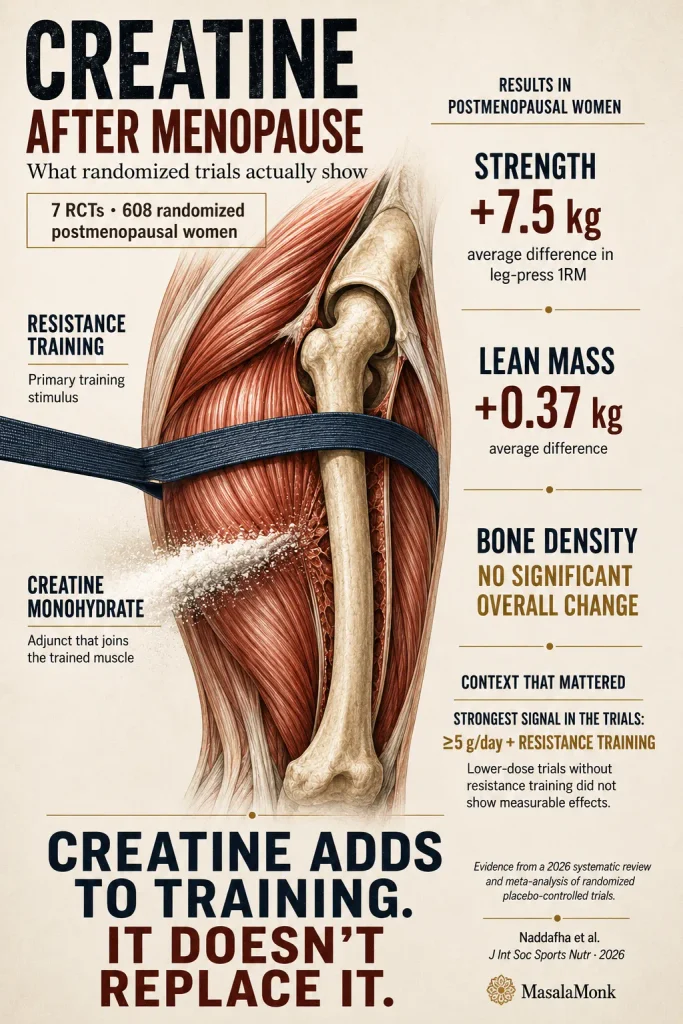
A 2026 systematic review and meta-analysis included seven randomized trials and 608 postmenopausal women overall. Five lean-mass comparisons involving 338 participants favoured creatine by about 0.37 kg, while three studies involving 111 participants contributed to the leg-press analysis, which favoured creatine by roughly 7.5 kg.
The clearest benefits appeared when at least 5 g/day was paired with resistance training. Overall bone density did not significantly improve. Most studies carried at least some risk-of-bias concerns, so the findings are encouraging rather than permission to attach every menopause claim imaginable to creatine.
That is a much stronger reason for interest than vague promises of “hormonal support.”
Creatine as you get older
The resistance-training partnership also matters in older adults.
A 2025 systematic review and meta-analysis found that creatine added to resistance training improved lower-body strength and lean tissue mass compared with resistance training plus placebo in older adults.
That makes creatine an interesting adjunct when preserving strength and function matters increasingly with age.
No scoop, however, reproduces what progressive strength training asks your muscles, bones and nervous system to do.
Vegetarians and vegans may start from a different baseline
Dietary creatine comes mainly from animal foods.
People eating little or no meat may therefore begin with lower creatine stores, leaving more room for those stores to rise after supplementation. A systematic review of vegetarian and omnivorous athletes found that tissue creatine often increased more in vegetarian participants, while studies were mixed on whether their exercise-performance gains were greater than those of omnivores.
That does not guarantee that every vegetarian or vegan will gain more strength, muscle or cognitive benefit than every omnivore.
Lower baseline stores help explain why biological responses can differ. They do not guarantee a particular visible result.
Is creatine safe?
For healthy adults taking commonly studied doses, creatine has an unusually large safety literature for a sports supplement.
A 2025 safety analysis covering 685 human creatine trials compared reported side effects across 12,839 creatine participants and 13,452 placebo participants. Overall participant-level side-effect reporting was 4.60% with creatine and 4.21% with placebo, a difference that was not statistically significant.
A separate 2026 study-level analysis across 684 randomized trials asked a different question: whether adverse effects showed a meaningful pattern as creatine dose or duration increased. Reported effects were generally infrequent and mild, and the analysis did not identify a consistent clinically meaningful dose- or duration-response pattern versus placebo.
That combination is reassuring: symptoms occur in both supplement and placebo groups, and the broad randomized-trial literature does not show the escalating safety pattern often implied online. It is still not evidence that every possible person in every medical situation should take creatine without thought.

For a symptom-by-symptom discussion of gastrointestinal complaints, water retention and other reported effects, see our dedicated guide to creatine side effects.
Creatine, creatinine and your kidneys
Imagine you have been taking creatine for several months.
You get routine blood work.
Your creatinine comes back higher.
After years of hearing that creatine “damages kidneys,” connecting those dots would be easy.
The test itself makes the story more complicated.
Creatine and creatinine are related, but not interchangeable
Creatine is the compound being supplemented.
Creatinine is a breakdown product.
Serum creatinine is also commonly used to estimate kidney filtration.
If creatine supplementation changes creatinine production or metabolism, a kidney estimate that relies on creatinine can move even when actual filtration has not deteriorated in the same way.
Two 2026 analyses help show why the blood test can look worse even when kidney filtration has not necessarily become worse.
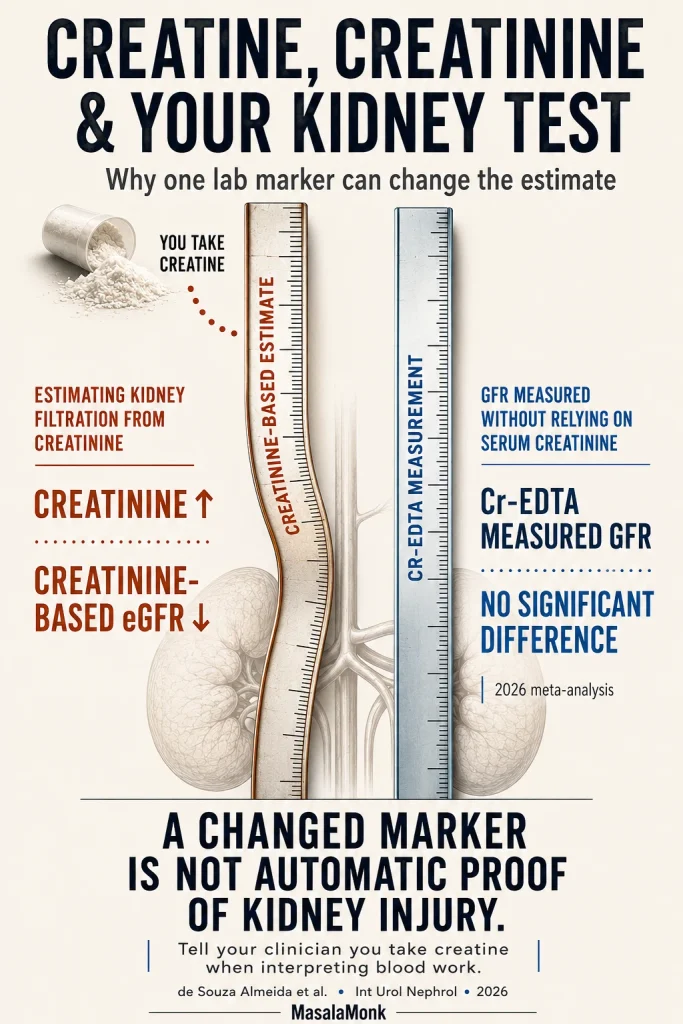
One meta-analysis of randomized trials found that supplementation increased serum creatinine by an average of about 0.13 mg/dL but did not find significant differences in urea or estimated GFR overall.
A second 2026 kidney-health meta-analysis went a step further. Across 26 studies, serum creatinine increased and creatinine-based GFR estimates decreased. But when filtration was assessed using Cr-EDTA, there was no statistically significant difference between creatine and control groups. Other kidney markers including albuminuria and proteinuria were also not significantly different.
The practical lesson: a creatinine-based estimate can be affected by something that changes creatinine metabolism. A higher result deserves clinical interpretation, but it is not automatic proof that creatine injured the kidneys.
So should you ignore a high creatinine result?
No.
A changed laboratory result deserves appropriate interpretation. Tell the clinician reviewing your blood work that you take creatine. They can consider supplementation alongside your medical history, other laboratory markers and—when clinically appropriate—measures that are less dependent on creatinine.
The point is not to self-diagnose yourself as healthy. It is also not to diagnose yourself with creatine-induced kidney damage from a single number.
What if you already have kidney disease?
That is a different situation from a healthy adult taking a sports supplement.
Research in people with kidney disease is much more limited, and Mayo Clinic recommends that people with kidney disease discuss creatine with their healthcare team.
Does creatine cause hair loss?
This rumour survived because there was just enough science underneath it to sound convincing.
Where the worry came from
A small 2009 study in rugby players reported changes in dihydrotestosterone (DHT) during creatine supplementation.
DHT is relevant to androgenetic hair loss in genetically susceptible people.
A plausible concern therefore emerged:
creatine → higher DHT → hair loss.
One important detail disappeared as the story travelled around gyms and the internet.
The study did not measure hair loss.
Then researchers measured the hair
In 2025, researchers conducted a randomized controlled trial specifically examining creatine and hair-follicle health.
Forty-five resistance-trained men aged 18–40 were assigned to 5 g/day of creatine monohydrate or placebo for 12 weeks.
Researchers measured total testosterone, free testosterone, DHT, hair density, follicular-unit count and cumulative hair thickness.
They found no significant differences in DHT or measured hair outcomes between creatine and placebo. Read the randomized trial.
That is much more direct evidence than the creatine-hair debate had previously.
It is also one 12-week trial in young resistance-trained men. It cannot answer every possible lifetime question about every population.
But we can no longer accurately say that nobody has directly tested creatine and hair loss. They have. In that first direct randomized trial, the results did not support the claim.

“But I started creatine and saw more hair in the shower”
That can be genuinely unnerving.
The difficult question is not whether you saw more hair. The difficult question is whether creatine caused it.
Hair shedding can change with genetics, age, illness, stress, calorie restriction, nutritional problems, medications and ordinary variation. When a new supplement and a new symptom appear close together, connecting them is natural.
Anecdotes are useful for spotting questions worth studying. Controlled trials are what help us test causation.
Does creatine dehydrate you?
Creatine increases water associated with muscle.
That fact somehow became a rule that creatine users must spend all day chasing a giant water target.
You do not need a special four- or five-litre creatine quota.
Hydration needs vary with body size, climate, sweat rate, exercise volume, diet, health and individual physiology.
If you are training outside in hot, humid weather, your fluid and electrolyte needs may be substantial because you are losing more fluid through sweat.
Creatine itself does not create an arbitrary universal number everyone must drink. Controlled evidence has not supported the old claim that recommended creatine use inherently causes dehydration or muscle cramping; a 2025 safety review found no significant adverse effect on hydration or thermoregulation in the controlled literature it assessed.
Hydrate according to your actual circumstances rather than a creatine-specific internet ritual.

If creatine bothers your stomach
Gastrointestinal discomfort is one of the more plausible practical complaints, particularly when somebody suddenly tries to consume a large loading dose.
Before spending more money on an exotic creatine form, simplify.
- skip loading;
- keep each dose smaller;
- split loading doses through the day;
- take creatine with food if that feels better;
- check whether your supplement contains sweeteners, stimulants or other ingredients that may be responsible.
The traditional loading protocol itself divides approximately 20 g across four doses rather than taking it all at once. NIH dosing guidance.
For many people, the stomach-friendly solution is simply 3–5 g/day without loading.
How to take creatine without overthinking it
This can be a remarkably simple supplement.
| Situation | Practical approach |
|---|---|
| You want the simplest routine | 3–5 g creatine monohydrate daily |
| You want faster saturation | ~20 g/day split into 4 doses for 5–7 days, then 3–5 g/day |
| Loading upsets your stomach | Skip it |
| It’s a rest day | Take your normal daily amount |
| You forgot yesterday | Resume your normal dose today |
| You stop using creatine | No taper is required |
Both loading and gradual daily dosing are well-established research approaches. NIH Office of Dietary Supplements

Is 3 grams enough?
For many people, yes.
The NIH describes non-loading research protocols around 3–6 g/day, including weight-adjusted approaches of roughly 0.03–0.1 g/kg/day, used over several weeks. See the dosing overview.
That does not mean the average recreational user needs a calculator. A consistent 3–5 g/day is much easier to follow than turning a simple supplement into body-weight mathematics.
Five grams is convenient. It is not a magical biological threshold.
Do you need to load?
No.
Loading mostly answers: How quickly do I want my muscle creatine stores to rise?
It does not answer: Will creatine eventually work if I don’t load it?
If you have a competition or a specific short timeline, reaching saturation quickly may matter. For a long-term gym routine, a slower daily approach is perfectly reasonable.
Before or after your workout?
For most users, the available timing literature does not support chasing a precise pre- versus post-workout window. Methodological limitations still prevent a firm recommendation for one ideal strategy. Review of creatine timing around exercise.
A 2026 randomized crossover pilot in 11 physically active men reported better acute lifting performance when creatine was consumed before exercise rather than during or after it. Interesting? Certainly. Enough to establish a new universal dosing rule? No—the authors themselves describe the findings as exploratory and in need of confirmation in larger studies.
Regular intake remains the more useful priority.
Morning works. Lunch works. After training works.
Choose a routine you will remember.
What about rest days?
Take your normal dose.
Creatine works through elevated tissue stores. Your muscles do not reset because today happens to be a rest day.
You forgot yesterday
Resume your normal amount.
There is no need to double today’s scoop or restart loading. One missed day does not erase weeks of accumulated muscle creatine.
Do you need to cycle creatine?
Routine creatine cycling has no established evidence-based requirement.
Gym culture borrowed “cycling” language from substances where cycling has entirely different biological reasons. Creatine is not an anabolic steroid.
What happens when you stop?
Muscle creatine stores gradually move toward baseline.
Some water-associated body weight may fall.
You do not need to taper, and there is no recognised creatine withdrawal syndrome.
Muscle that you genuinely built through months of training does not suddenly vanish because the supplement left your shaker.
Can you take creatine with coffee?
For ordinary coffee drinkers taking normal creatine doses, the evidence does not justify a blanket rule that caffeine and creatine must always be separated.
The reason the internet argument sounds contradictory is that the small research base has tested different ways of combining them. Two systematic reviews each identified only about ten relevant studies. One review found that acute caffeine taken after a creatine-loading phase generally did not erase caffeine’s ergogenic effect, whereas chronic caffeine consumed throughout loading produced mixed results: some studies suggested interference, several found no interaction and one reported synergy.
A second systematic review similarly found that acute caffeine after loading produced an additional ergogenic effect over creatine alone in three of five studies, while daily caffeine during loading produced an additive benefit in only one of five studies.
That is not enough evidence to invent a mandatory two-, four- or six-hour separation rule. Your morning coffee does not automatically cancel your creatine, but chronic high-caffeine use during a loading phase is less settled. If combining large doses makes your stomach miserable, separating or simplifying them is sensible.

Which type of creatine should you buy?
This is the easiest part.
Creatine monohydrate.
It has the deepest evidence base, a long history of use and usually the lowest price.
A systematic review examining alternative creatine forms found very few direct comparisons with monohydrate and no consistent evidence that newer forms outperform it.
| Form | What to know |
|---|---|
| Creatine monohydrate | Best-studied default |
| Micronized creatine monohydrate | Same form, smaller particles; may mix more easily |
| Creatine HCl | Marketed with advantages that have not convincingly beaten monohydrate in evidence |
| Buffered creatine | No established practical superiority over monohydrate |
The NIH likewise notes that more expensive alternatives have not been proven superior for increasing muscle creatine, digestibility, stability or safety.

“Micronized” is not a different type of creatine
Despite the label, micronized creatine is still creatine monohydrate.
The term simply means the powder has been processed into smaller particles, which may help it disperse more easily in liquid without changing the underlying form of creatine.
Product quality matters more than impressive wording
Choose a reputable manufacturer.
If you compete in tested sport, independent sport certification may be particularly valuable because contamination with prohibited substances is a separate issue from whether creatine itself works.
You do not need a proprietary “ultra-anabolic matrix.” You need the product to contain what the label says it contains.
Who should be more cautious?
Healthy-adult evidence cannot automatically be transplanted into every population.
Known kidney disease
Discuss creatine with the healthcare team managing your kidney health rather than extrapolating from healthy-adult trials. Mayo Clinic creatine guidance.
Pregnancy and breastfeeding
Creatine is being investigated in maternal and fetal physiology, but routine supplementation during pregnancy and breastfeeding does not have the depth of human safety evidence available for adult sports supplementation. A recent safety review notes that evidence remains lacking in pregnancy, while the NIH LactMed creatine monograph reports that human milk levels after supplementation have not been studied and advises avoiding supplementation unless prescribed until more data are available.
Individual clinical advice is more appropriate here than extrapolating from gym studies.
Adolescents
It is no longer accurate to say that creatine has never been studied in teenagers.
A 2026 systematic review found five eligible studies and reported no consistent short-term kidney, liver or cardiometabolic safety signals during the study periods. It also emphasized how limited the evidence remains and the need for larger studies with longer follow-up.
So the evidence is not zero. It is also nowhere near as deep as the adult literature.
Medical conditions and medications
If you are managing a medical condition or take medication that affects kidney function, fluid balance or another relevant system, disclose supplement use to your healthcare professional.
“Available without a prescription” does not mean “irrelevant to medical care.”
Frequently asked creatine questions
Everyday use and common questions
Can I mix creatine with whey protein?
Yes. Protein and creatine do different jobs, and there is no reason they have to live in separate drinks. If putting both in the same shake helps you remember your creatine, that is a perfectly good routine. For broader nutrition context, our guide to what protein does explains the role of dietary protein in more detail.
Can I take creatine on an empty stomach?
Yes, if you tolerate it. When your stomach dislikes it, take creatine with food. There is no benefit to making a simple supplement uncomfortable.
Is creatine a steroid?
No. Creatine is not an anabolic steroid. It is a compound your body naturally makes and uses in the creatine–phosphocreatine energy system; supplementation increases creatine availability rather than working through the hormonal mechanisms that define anabolic steroids.
Training, sport and long-term use
What if I take creatine but don’t work out?
Your tissue creatine stores can still increase. But many of the outcomes people want—more strength, more muscle and better training performance—depend on actually creating a training stimulus. The scoop cannot perform the repetitions for you. See the strength evidence for the training context.
Can runners take creatine?
Yes. The better question is whether it suits the runner’s goals. Someone who strength trains, sprints or performs repeated high-intensity intervals may have more reason to use creatine than someone concerned only with long-duration endurance. The dedicated endurance meta-analysis found no significant overall performance benefit in trained populations; see the full creatine-for-runners and endurance discussion.
How long can you take creatine?
There is no evidence-based rule telling healthy adults that creatine must be stopped after an arbitrary number of weeks. Mayo Clinic currently describes recommended oral doses as likely safe for many people for up to five years. That reflects the duration supported by available longer-term evidence; it does not mean creatine suddenly becomes unsafe on the first day of year six.
The 2026 analysis of 684 randomized trials also found no consistent pattern of clinically meaningful adverse effects increasing with dose or duration at the study level. Science cannot give us lifetime data on every possible user, but the available evidence does not support the familiar rule that healthy adults must routinely cycle off because continuous creatine inevitably becomes dangerous. For the broader context, see the creatine safety section.
So, is creatine worth taking?
Creatine has travelled through two opposite reputations.
First it was the suspicious bodybuilding powder supposedly responsible for cramps, kidney damage and baldness.
Now it is in danger of becoming a universal wellness supplement for muscle, menopause, memory, mood, longevity and brain optimisation.
Neither version fits the evidence particularly well.
Creatine is excellent at a fairly specific job. It supports the body’s rapid-energy system, and that translates into strong evidence for repeated high-intensity performance, greater strength gains and modestly greater lean-mass gains alongside resistance training.
The newer possibilities—in cognition, aging and postmenopausal women—deserve curiosity without being promoted to certainty before the evidence gets there.
And ordinary creatine use is much less complicated than supplement culture has made it.
For a healthy adult who decides it fits their goals:
Use creatine monohydrate.
Take around 3–5 grams each day.
Be consistent.
Then put considerably more thought into your training, food and sleep than into the timing of the scoop.
Key research used for this September 2026 update
How this guide was researched: priority was given to systematic reviews, meta-analyses, randomized controlled trials and major evidence-based clinical or sports-nutrition resources. Community questions were useful for identifying what readers are confused or worried about, but anecdotes were not treated as proof of benefit or harm. Where individual studies carried important limitations, we also considered sample size, study duration, risk of bias and relevant author disclosures when deciding how strongly to describe a finding.
Core performance, kidney and safety evidence
- NIH Office of Dietary Supplements. Dietary Supplements for Exercise and Athletic Performance: Health Professional Fact Sheet. Dosing, loading, forms, safety context and high-intensity exercise guidance.
- Desai I, et al. (2024). The Effect of Creatine Supplementation on Resistance Training-Based Changes to Body Composition: A Systematic Review and Meta-analysis. Journal of Strength and Conditioning Research.
- Kazeminasab F, et al. (2025). The Effects of Creatine Supplementation on Upper- and Lower-Body Strength and Power: A Systematic Review and Meta-Analysis. Nutrients.
- Tsiaras A, et al. (2026). The effect of creatine supplementation on kidney function: a systematic review and meta-analysis of randomized controlled trials. Journal of Renal Nutrition.
- de Souza Almeida A, et al. (2026). Impact of creatine supplementation on kidney health: a systematic review and meta-analysis. International Urology and Nephrology.
- Lak M, et al. (2025). Does creatine cause hair loss? A 12-week randomized controlled trial. Journal of the International Society of Sports Nutrition.
- Kreider RB, et al. (2025). Safety of creatine supplementation: analysis of the prevalence of reported side effects in clinical trials and adverse event reports. Journal of the International Society of Sports Nutrition.
- Gonzalez DE, et al. (2026). Creatine Supplementation Dose and Duration Are Not Associated with Increased Side Effects: A Structured Review and Study-Level Dose-Response Analysis of Randomized Controlled Trials. Sports.
Cognition, special populations and performance contexts
- Naddafha S, et al. (2026). Creatine monohydrate for lean mass, strength, and bone density in postmenopausal women: a systematic review and meta-analysis. Journal of the International Society of Sports Nutrition.
- Xu C, et al. (2024). The effects of creatine supplementation on cognitive function in adults: a systematic review and meta-analysis. Frontiers in Nutrition.
- McMorris T, et al. (2024). Creatine supplementation research fails to support the theoretical basis for an effect on cognition: Evidence from a systematic review. Behavioural Brain Research.
- Liu S, et al. (2025). The impact of creatine supplementation associated with resistance training on muscular strength and lean tissue mass in the aged: a systematic review and meta-analysis. European Review of Aging and Physical Activity.
- Fernández-Landa J, et al. (2023). Effects of Creatine Monohydrate on Endurance Performance in a Trained Population: A Systematic Review and Meta-analysis. Sports Medicine.
- Wesołowski I, et al. (2026). Creatine Supplementation in Endurance and Mixed-Sport Contexts: A Scoping Review of Performance, Recovery, and Body Composition. Nutrients.
- Northeast B, Clifford T. (2021). The Effect of Creatine Supplementation on Markers of Exercise-Induced Muscle Damage: A Systematic Review and Meta-Analysis of Human Intervention Trials. International Journal of Sport Nutrition and Exercise Metabolism.
- Ribeiro F, et al. (2021). Timing of Creatine Supplementation around Exercise: A Real Concern? Nutrients.
- Ben Maaoui K, et al. (2026). Acute Creatine Ingestion Before Resistance Training Enhances Strength Performance More than Ingestion During or After Training: A Randomized Crossover Pilot Trial. Nutrients.
- Kaviani M, Shaw K, Chilibeck PD. (2020). Benefits of Creatine Supplementation for Vegetarians Compared to Omnivorous Athletes: A Systematic Review. International Journal of Environmental Research and Public Health.
Forms, caffeine and clinical guidance
- Longobardi I, et al. (2025). A short review of the most common safety concerns regarding creatine ingestion. Frontiers in Nutrition.
- Fazio C, et al. (2022). Efficacy of Alternative Forms of Creatine Supplementation on Improving Performance and Body Composition in Healthy Subjects: A Systematic Review. Journal of Strength and Conditioning Research.
- Elosegui S, et al. (2022). Interaction Between Caffeine and Creatine When Used as Concurrent Ergogenic Supplements: A Systematic Review. International Journal of Sport Nutrition and Exercise Metabolism.
- Marinho AH, et al. (2023). Effects of creatine and caffeine ingestion in combination on exercise performance: A systematic review. Critical Reviews in Food Science and Nutrition.
- Rubinchuk A, et al. (2026). Evaluating the Safety of Creatine Monohydrate in Adolescents: A Systematic Review of Renal, Hepatic, and Cardiometabolic Outcomes. Cureus.
- Drugs and Lactation Database (LactMed): Creatine. National Library of Medicine; revised July 15, 2025.
- Mayo Clinic — Creatine. Clinical overview of uses, safety, kidney caution and longer-term use.