Posted on — 5 Comments

Side Effects of Mounjaro (Tirzepatide): What’s Common, What’s Serious & How to Handle Them

SIDE EFFECTS OF MOUNJARO (TIRZEPATIDE): What's Common, What's Serious & How to Handle Them

If you’re researching Mounjaro side effects, you’re not alone. Right from the first dose, most people want clear, compassionate guidance: what typically happens, how long it lasts, and—crucially—how to make side effects easier to live with. Because searches also show a lot of concern about Mounjaro body aches, Mounjaro muscle pain, Mounjaro joint pain, and leg cramps on Mounjaro, this guide goes beyond the gastrointestinal (GI) issues that dominated the trials and addresses what real people feel day to day. For orientation on frequency, timing, and red flags, the definitive summary remains the Mounjaro prescribing information (May 2025); meanwhile, large clinical programs such as the SURMOUNT-1 trial (NEJM) and the SURPASS-2 trial (NEJM) consistently show GI effects lead early and usually settle with time.

Plain-Language Reminder (Not Medical Advice): Bodies differ. If a symptom feels severe, persistent, or simply “not you,” talk with your clinician rather than trying to tough it out. Informational only—this article is educational, not medical advice. Decisions about starting, stopping, or adjusting medication should be made with your own clinician.


Common Mounjaro Side Effects (GI) — Why They Happen, When They Peak, and What Actually Helps

Why this happens. Tirzepatide slows gastric emptying and shifts gut-hormone signaling. Consequently, larger or fattier meals can “sit heavy,” nausea tends to cluster around initiation and step-ups, bowel habits may swing toward diarrhea or constipation, and reflux/burping can show up after late dinners. Fortunately, the gut adapts; with simple meal structure changes, hydration, and thoughtful dose pacing, most people feel steadily better. For frequencies and timing, see the Mounjaro prescribing information (May 2025) and the SURMOUNT-1 trial (NEJM).

Nausea On Mounjaro (Most Common GI Side Effect)

What’s going on. Slower stomach emptying + dose increases.
Today’s fixes.

  • Smaller, earlier, lower-fat meals; slow the pace; skip “hero portions.”
  • Sit upright 30–60 minutes after eating; sip fluids between meals.
  • Gentle helpers: ginger tea/lozenges; cooler foods if aromas trigger queasiness.
    Call sooner if: Fluids won’t stay down, dizziness appears, or nausea lingers beyond a few days at a stable dose.

Vomiting On Mounjaro (Less Common—Prevent Dehydration First)

Immediate goal: Hydration. Tiny, frequent sips; on rough days use oral rehydration. For simple ratios and options, see our post on electrolytes for diarrhea: best natural drinks & remedies.
Food texture: Bland, low-fat, easy to digest (broth, yogurt, rice, crackers).
Training: Pause high-intensity workouts until rehydrated.
Red flags: Repeated vomiting, very low urine, faintness, or dark urine → call promptly.

Diarrhea On Mounjaro (Triggers And Fixes)

Replace losses early: Fluids + electrolytes at the first sign.
Shift the plate: Add soluble fiber (ripe bananas, applesauce, oats, psyllium) once cramps ease.
Trim common triggers: Greasy foods, alcohol, very spicy dishes, and sugar alcohols (sorbitol/xylitol) often worsen things—reduce them for now.

Constipation On Mounjaro (Slow Transit After Step-Ups)

Build the base: Water, fiber (vegetables, berries, oats, chia), and movement.
Bathroom routine: A short walk after meals plus a daily, unhurried “appointment.”
If needed: Ask about a gentle osmotic option.

Before you start a fiber supplement, read this practical take on Metamucil’s day-to-day side effects.

Heartburn, Reflux, And Burping (Dyspepsia)

Structure meals: Smaller portions, earlier dinners, and avoid lying down within 3 hours of eating.
Usual culprits: High-fat meals, chocolate, mint, citrus, caffeine.
At night: Slight head-of-bed elevation; left-side sleep can help.

Abdominal Pain Or Bloating (Ordinary Vs Concerning)

Start simple: Slow your eating speed; favor lower-fat meals; walk 10–15 minutes after eating.
However: Severe, persistent, or radiating pain—especially with vomiting or fever—warrants prompt evaluation to rule out gallbladder or pancreas issues (details in the prescribing information).

Educational note—this is not medical advice. GI symptoms can quietly drain fluids and minerals. Consequently, dehydration often ripples outward as leg cramps on Mounjaro and generalized “achey” days. Because that matters to readers, let’s go there next.


Mounjaro Body Aches, Mounjaro Muscle Pain, And Leg Cramps On Mounjaro — Why They Happen And How To Ease Them

Short answer. In the trials, musculoskeletal pain was not among the most frequent adverse events; GI symptoms dominated. Even so, some people report myalgia, generalized aches, cramps, or transient arthralgia in real life—especially around dose escalations. Very rarely, case reports describe rhabdomyolysis (severe muscle breakdown) shortly after starting or stepping up tirzepatide. For the official overview, consult the Mounjaro prescribing information (May 2025); for a rare but notable signal, see a 2025 rhabdomyolysis case report.

Why Mounjaro Muscle Pain And Body Aches Show Up For Some People

  1. Dehydration And Electrolyte Shifts
    Because nausea, vomiting, or diarrhea reduce fluid and minerals, dips in sodium or potassium can provoke cramps and soreness. Moreover, volume depletion strains the kidneys, which is one reason the label emphasizes hydration.
  2. Rapid Weight Loss, Posture Changes, And New Routines
    As weight drops, posture and gait adapt. Meanwhile, many people ramp up activity at the same time. Consequently, transient muscle soreness and joint “awareness” are common and usually settle with smart pacing.
  3. Very Rare Muscle Injury (Know The Red Flags)
    Severe pain, true weakness, or cola-colored urine after a dose change warrants same-day assessment to rule out rhabdomyolysis.

Leg Cramps On Mounjaro — Quick Wins That Work

  • Rehydrate, then replace electrolytes on GI-symptom days (don’t wait). For simple at-home options, see DIY natural electrolyte drinks for dehydration.
  • Ease into training for a week after each escalation; choose low-impact movement, light cycling, or walking.
  • Stretch in the evening; add a brief morning warm-up.
  • Call promptly if cramps are severe, frequent, or accompanied by dark urine or weakness.

Mounjaro Joint Pain — Typical Vs Not Typical

  • Typical: Fleeting stiffness or “joint awareness” while body mechanics shift. Hydration + gentle, regular movement (walking, swimming, cycling) usually helps.
  • Not typical: Hot, swollen joints, fever, or motion-limited pain—seek care rather than self-managing.

A One-Week Plan To Reduce Mounjaro Muscle Pain And Body Aches

  • Day 1–2 (after a step-up): front-load fluids; schedule short walks after meals; keep meals smaller and lower-fat; hold off on strenuous training.
  • Day 3–4: add a 10–15 minute mobility routine (hips, calves, thoracic spine); resume light cycling or brisk walking; maintain protein at each meal.
  • Day 5–7: trial a short, low-volume resistance circuit (2–3 sessions this week); if aches spike again, extend your time at the current dose before escalating.

Informational only—please individualize with your clinician.


Hair Loss On Mounjaro — 2025 Label Update, Why Shedding Happens, And What Genuinely Helps

Some people notice hair loss on Mounjaro, yet most shedding resembles telogen effluvium—a temporary, nonscarring shed triggered by rapid weight loss or nutrition gaps. In May 2025, “alopecia” was added to the label’s postmarketing section (reported after use; not proven common in trials). See the Mounjaro prescribing information (May 2025). For a straightforward primer on TE, a helpful overview is this dermatology review of telogen effluvium.

Why Telogen Effluvium Follows Rapid Weight Change

During calorie or protein deficits, the body prioritizes essentials over hair production. Consequently, more follicles enter the resting (telogen) phase, and diffuse shedding appears 2–3 months later. Reassuringly, TE is reversible once intake and weight stabilize, although it does take weeks to show improvement and months to reveal obvious regrowth.

Where Mounjaro Fits

Tirzepatide can suppress appetite and accelerate weight loss; meanwhile, early GI side effects may further dent intake. Put simply, short stretches of low protein and low micronutrients are enough to push susceptible follicles into telogen.

What Actually Helps (Practical, Doable Steps)

  • Stabilize Intake Before Dose Jumps. If appetite is poor or GI symptoms flare, pause escalation or extend your time at the current dose until eating normalizes.
  • Keep Protein Steady. A pragmatic starting range during active weight loss is ~1.2–1.6 g/kg/day (individualized with your clinician), spread across meals to protect lean mass and hair. (See our post on how to eat 100 grams of protein a day if you need a plan).
  • Check The Usual Nutrients. Ask about ferritin/iron, zinc, and vitamin D if shedding is significant or prolonged; correct deficits with guidance.
  • Avoid Extreme Deficits. On low-appetite days, rely on easy, higher-protein, lower-fat options (Greek yogurt, eggs, tofu, cottage cheese, smoothies). Meanwhile, stay ahead of dehydration.
  • Give It Time. Expect 6–12 weeks for shedding to calm and several months for visible regrowth. Reduce heat styling and tight hairstyles while new growth returns.

Educational note—this is not medical advice. Patchy loss, scalp inflammation, or prolonged heavy shedding deserves a medical work-up.


Mounjaro Vision Changes — Blurry Vision, Diabetic Retinopathy, And Keeping An Eye On Emerging Data

Most people will not develop vision problems on tirzepatide. However, if you already have diabetic retinopathy, rapid glucose improvement can temporarily worsen retinopathy or cause transient blur; therefore, extra monitoring is sensible. This precaution is described in the Mounjaro prescribing information (May 2025). Separately, an observational cohort in 2025 reported a class-level association between GLP-1 medicines and neovascular age-related macular degeneration (nAMD); although absolute risk was small and causality is unproven, it’s a timely reminder to keep routine eye checks (see the JAMA Ophthalmology 2025 cohort).

Why Vision Can Shift When Glucose Improves Rapidly

As sugars normalize, the lens and retina adjust; transient blur or short-term retinopathy changes can appear, then stabilize. Notably, this is not unique to tirzepatide; it can occur with any rapid glycemic improvement.

Practical Steps That Protect Your Eyes

  • Book An Eye Exam if you have a history of retinopathy or if new blur appears; bring recent glucose logs so your eye doctor can see your rate of change.
  • Aim For Steadier Glucose via regular meals, dose pacing, sleep, and gentle movement—fewer spikes and dips often mean fewer visual swings.
  • Do Not Stop Abruptly on your own; call your clinician if vision symptoms appear.

Vision Red Flags—Call Urgently

  • Sudden vision loss or a dark “curtain.”
  • Flashes or a shower of new floaters.
  • Eye pain, severe headache, or nausea with visual changes.

Information only—urgent changes deserve urgent care.


Mounjaro Dosing And Timeline — When Side Effects Tend To Show Up And How To Smooth The Ride

Most Mounjaro side effects cluster at initiation and each dose increase. Because the body adapts, your biggest lever is dose pacing plus a few supportive habits. For official dosing language, see the Mounjaro prescribing information (May 2025). For peri-procedural considerations (aspiration risk with anesthesia/deep sedation), a concise summary is available from The Medical Letter peri-procedural guidance (2024).

Standard Step-Ups (And Why Slower Often Feels Better)

Many people follow 4-week steps: 2.5 → 5 → 7.5 → 10 → 12.5 → 15 mg. However, if you reliably hit a rough patch at each increase, you can ask to stay longer at a tolerable dose or stretch a step to 6–8 weeks. Consequently, the “shock” to gastric emptying and appetite signals is smaller, and rescue meds are often unnecessary.

What To Expect By Week (Common, Not Universal)

  • Week 1–2 At A New Dose: Nausea peaks; stools may swing; appetite dips most here.
  • Week 3–4: Symptoms usually fade; energy stabilizes; workouts resume.
  • Within 48–72 Hours Of An Injection: Many people feel a mini-wave of queasiness/fullness on “shot day” and the next day; earlier dinners and smaller portions help.

“Shot-Day” Playbook (Copy And Use)

  • Night Before: Earlier, lighter dinner.
  • Dose Day: Smaller, more frequent meals; avoid very high-fat feasts; keep fluids handy.
  • Walk After Meals: 10–15 minutes reduces fullness and burping.
  • If Appetite Tanks: Rely on easy proteins (yogurt, eggs, tofu, cottage cheese, smoothies).
  • Training: Delay high-intensity sessions 48–72 hours if you’re routinely queasy after injections.

Travel, Big Events, And Procedures

  • Travel Week: Hold at your current dose rather than escalating right before a flight.
  • Big Events: Coordinate injection timing (with your prescriber) so the queasiest window doesn’t land on your most important day.
  • Anesthesia & Endoscopy: GLP-1s delay gastric emptying; instead of stopping on your own, coordinate with your surgical/anesthesia team for individualized instructions (see The Medical Letter peri-procedural guidance (2024)).

Educational disclaimer: These are general strategies, not individualized medical advice.


Serious Side Effects Of Mounjaro — Clear Warning Signs, In Plain English

Most people never experience these, yet it’s important to know what to watch for. Full details live in the Mounjaro prescribing information (May 2025).

Pancreas And Gallbladder — When Stomach Pain Isn’t “Just GI”

  • Acute Pancreatitis: Sudden, severe upper-abdominal pain (often radiating to the back) with nausea/vomiting → same-day assessment.
  • Gallbladder Disease: Right-upper-quadrant pain (sometimes after meals) ± fever or jaundice → prompt evaluation.

Kidneys — Dehydration Can Snowball

Repeated vomiting/diarrhea plus dizziness or very low urine can tip you toward acute kidney injury. If fluids aren’t staying down, you may need IV hydration and labs—don’t wait for things to get worse.

Vision — Who Needs Closer Monitoring

If you have diabetic retinopathy, rapid glucose improvement can temporarily worsen retinopathy or cause blur—book an eye exam (see prescribing info). Meanwhile, the JAMA Ophthalmology 2025 cohort suggested a small class-level nAMD association; keep routine checks regardless.

Hypersensitivity — Don’t Second-Guess This

Swelling of lips/face/tongue, hives, trouble breathing, or wheezing after an injection = urgent care.

Stomach And Anesthesia — Aspiration Risk Is Manageable With Planning

GLP-1s slow gastric emptying. For procedures with anesthesia or deep sedation, approaches are individualized—based on your symptoms and the procedure type—rather than a blanket stop. Coordinate with your care team (see The Medical Letter peri-procedural guidance (2024)).

Muscle — Rare But Serious

Rhabdomyolysis is rare but serious. Severe muscle pain, true weakness, or cola-colored urine after starting or increasing dose needs same-day evaluation (see the 2025 case report in the references list).

Thyroid Boxed Warning — Who Should Avoid

Tirzepatide carries a boxed warning for thyroid C-cell tumors seen in rodents. People with a personal/family history of medullary thyroid carcinoma or MEN2 should not use it. If you have thyroid nodules or concerns, talk to your clinician.

Informational only—follow your clinician’s advice for your situation.


Quick “Should I Call?” Filter For Mounjaro Side Effects

Call the same day if you have:

  • Severe abdominal pain (especially with vomiting).
  • Persistent vomiting/diarrhea plus dizziness or very low urine.
  • Sudden vision changes (especially if you’ve had retinopathy).
  • Allergic-type symptoms (swelling, breathing trouble, hives).
  • Severe muscle pain/weakness or dark urine.

When in doubt, it’s okay (and wise) to call.


Everyday Habits That Reduce Mounjaro Side Effects (A Practical Toolkit)

Hydration & Electrolytes. Set a daily fluid target; on rough GI days, use an oral rehydration solution. Consequently, you’ll often see fewer leg cramps on Mounjaro, less “whole-body ache,” and steadier energy.

Protein At Every Meal. Even distribution—breakfast, lunch, dinner—supports recovery, preserves lean mass, and reduces “all-over” soreness during weight loss.

Movement Hygiene. Brief post-meal walks, 2–3 short resistance sessions weekly, and daily mobility for tight spots (neck, hips, calves) go a long way. Build gradually; don’t leap.

Dose Pacing. If symptoms surge at every increase, extend the step. Many people feel dramatically better with an extra week or two at a tolerable dose.

Educational reminder—this is not personalized medical advice.


References


Final Disclaimers

  • This article is informational and educational. It does not replace personalized medical advice, diagnosis, or treatment.
  • Dose pacing, nutrition, and symptom management should be coordinated with your clinician.
  • If you believe you’re experiencing a medical emergency, call your local emergency number immediately.

FAQs on Side Effects of Mounjaro

Informational only—these FAQs are educational, not medical advice. If a symptom is severe, persistent, or feels “not you,” please speak with your clinician.

1) Do Mounjaro Side Effects Happen Right Away Or Later?

Most Mounjaro side effects appear during the first few weeks and again after each dose increase. However, they often ease as your body adapts. If a new symptom appears suddenly or feels severe, check in with your clinician.

2) Are Mounjaro Body Aches Normal?

Mounjaro body aches can happen, especially during dose escalations. They’re often related to dehydration, electrolyte shifts, or routine changes. Consequently, steady fluids, light movement, and dose pacing usually help.

3) Can Mounjaro Cause Muscle Pain Or Muscle Aches?

Yes, Mounjaro muscle pain can occur for some people. It’s commonly mild and linked to volume depletion or new exercise. However, severe pain, true weakness, or dark “cola” urine needs same-day medical review.

4) What About Mounjaro Joint Pain—Is That Expected?

Some experience Mounjaro joint pain or “joint awareness,” especially as weight, posture, and activity change. Gentle mobility, hydration, and gradual training can reduce it. Hot, swollen joints or fever require evaluation.

5) Why Do I Get Leg Cramps On Mounjaro?

Leg cramps on Mounjaro often trace back to low fluids or electrolytes, particularly after nausea, vomiting, or diarrhea. Therefore, rehydrate early, replace electrolytes, and stretch in the evening.

6) I Have Neck Pain On Mounjaro—Should I Worry?

Mounjaro neck pain is usually muscle tension or posture-related as activity patterns shift. Still, if pain is severe, radiates, or includes numbness/tingling or weakness, seek medical advice.

7) Does Mounjaro Cause Hip Pain Or Knee Pain?

Some report Mounjaro hip pain or Mounjaro knee pain, typically from changes in gait during weight loss or from ramping workouts too fast. Gradual progressions, supportive footwear, and low-impact cardio help.

8) Can Mounjaro Cause Body Aches After The First Dose?

Yes—first-dose days and step-up weeks are the most likely times. Fortunately, aches often fade within days as hydration and meal structure improve.

9) Is Muscle Weakness A Side Effect Of Mounjaro?

Minor fatigue can appear during appetite suppression. However, true weakness—especially with severe muscle pain or dark urine—needs urgent care to rule out serious issues.

10) What Are The Most Common Mounjaro GI Side Effects?

Nausea, diarrhea, decreased appetite, constipation, and heartburn/burping are the headliners. They tend to cluster early and settle with smaller, earlier, lower-fat meals plus dose pacing.

11) Does Mounjaro Cause Diarrhea Or Constipation—And What Helps?

Both can happen. For diarrhea, replace fluids/electrolytes early and trim triggers like greasy meals or sugar alcohols. For constipation, build fluids, fiber, and movement; then consider a gentle osmotic if needed.

12) Why Am I Burping So Much On Mounjaro?

Slower gastric emptying and large/high-fat meals can increase burping and belching. Therefore, eat smaller portions, dine earlier, and stay upright after meals. Left-side sleeping can also help.

13) Does Mounjaro Cause Heartburn Or Indigestion?

It can. Structure meals (smaller, earlier), reduce trigger foods (very fatty meals, mint, citrus, caffeine), and elevate the head of the bed. Persistent or severe reflux deserves a check-in.

14) Can Mounjaro Cause Headaches?

Headaches may appear when hydration, caffeine, or sleep patterns change. Steady fluids, regular meals, and consistent bedtime often help. However, sudden or severe headaches need medical advice.

15) Why Do I Feel Tired On Mounjaro?

Mounjaro tiredness can stem from lower calorie intake, dehydration, or sleep disruption. Consequently, aim for balanced meals with protein, sip fluids regularly, and respect recovery on dose-change weeks.

16) Is Hair Loss On Mounjaro A Real Thing?

Yes—some people notice hair loss on Mounjaro, commonly a temporary shedding pattern called telogen effluvium. It often follows rapid weight loss or nutrition gaps and improves as intake stabilizes.

17) Can Mounjaro Affect Vision Or Cause Blurry Vision?

Mounjaro vision changes are uncommon. Yet, if you have diabetic retinopathy or your sugars are improving rapidly, transient blur can occur. Therefore, schedule an eye exam if vision changes appear.

18) Do Mounjaro Side Effects Differ By Dose (2.5 mg vs 5 mg vs 10 mg, etc.)?

Side effects often flare at each dose increase. Many people do better by staying longer at a comfortable dose before stepping up. In other words, slower titration can mean smoother weeks.

19) Are There Serious Side Effects Of Mounjaro I Should Know?

Yes, but they’re uncommon. Red flags include severe abdominal pain (with vomiting), signs of dehydration with very low urine, allergic reactions (swelling, hives, breathing trouble), sudden vision changes, or severe muscle pain/weakness with dark urine.

20) Does Mounjaro Cause Body Aches After Each Weekly Shot?

Some feel a mini-wave of queasiness or body aches within 48–72 hours of the injection. Consequently, earlier lighter dinners, steady fluids, and gentle movement can make “shot days” easier.

21) How Long Do Mounjaro Side Effects Last?

Many symptoms settle within 1–3 weeks at a given dose. If a side effect doesn’t ease—or it worsens—despite basic strategies, it’s time to check in with your clinician.

22) Can I Prevent Mounjaro Side Effects Before They Start?

You can reduce risk: escalate doses slowly, keep meals smaller and earlier, hydrate daily, and plan light exercise plus sleep consistency during step-up weeks.

23) Are Mounjaro Side Effects Different For Weight Loss vs Diabetes?

The pattern is similar—GI effects lead—yet timing and intensity can differ by individual factors (diet, speed of glucose improvement, titration, baseline health). Personalization matters.

24) Does Mounjaro Cause Long-Term Side Effects?

Most side effects are short-term and dose-related. However, any persistent or worrisome symptom—especially visual changes, gallbladder-type pain, or severe muscle issues—warrants medical review.

25) Can Mounjaro Cause Aches And Pains Weeks After Starting?

Yes, especially around dose changes or big routine shifts. Meanwhile, hydration, electrolytes, protein at meals, and gentler training usually turn the corner within days.

26) What Should I Do If I Have Severe Nausea Or Vomiting On Mounjaro?

Prioritize fluids and call sooner rather than later. Tiny sips of oral rehydration, bland foods, and a quieter activity plan help—but inability to keep fluids down is a reason to seek care.

27) What If I Have Persistent Diarrhea On Mounjaro?

Rehydrate early, step back from greasy/spicy foods and sugar alcohols, and add soluble fiber after cramps ease. If diarrhea persists, especially with dizziness or very low urine, call your clinician.

28) Are Injection-Site Reactions Common?

Mild redness or itch can appear; rotating sites and letting alcohol dry before injecting usually helps. However, spreading rash, warmth, or swelling deserves a check.

29) Does Mounjaro Raise Or Lower Blood Pressure?

Weight loss and improved insulin sensitivity can lower blood pressure in some people over time. Nevertheless, watch for dehydration on rough GI days, which can make you feel light-headed.

30) When Should I Call A Clinician About Mounjaro Side Effects?

Call the same day for: severe abdominal pain, persistent vomiting/diarrhea with dizziness or low urine, sudden vision changes, allergic-type symptoms, or severe muscle pain/weakness with dark urine.


Friendly reminder: everyone’s response is unique. Therefore, if something feels off, you don’t need to wait—reach out to your clinician for personalized guidance.


Posted on — 6 Comments

Iron Deficiency Anemia Symptoms: 15 Signs You Are Iron Deficient

IRON DEFICIENCY ANEMIA SYMPTOMS: 15 SIGNS YOU ARE IRON DEFICIENT

Iron deficiency symptoms are among the most common health complaints worldwide — yet they’re also some of the most overlooked. Iron may be a small trace mineral, but it has a massive role: it helps produce hemoglobin, the protein in red blood cells that delivers oxygen throughout your body. Without enough iron, every cell in your body is deprived of oxygen, and the effects can be felt in your energy, focus, immunity, and even your mood.

At first, low iron symptoms may appear mild — perhaps you feel a bit more tired than usual or notice your nails breaking more easily. But over time, untreated deficiency can lead to Iron Deficiency Anemia (IDA), a condition that affects more than 1.2 billion people worldwide. From unexplained fatigue and hair loss to shortness of breath, chest pain, and brain fog, the signs of anemia can sneak up slowly yet impact nearly every part of daily life.

This guide breaks down the 15 most common iron deficiency symptoms, explores how they can look different in men and women, and shares practical strategies to restore healthy iron levels through diet, supplements, and medical support. If you’ve been wondering whether your tiredness, headaches, or mood changes could be related to low iron, this is your complete evidence-based resource.


🩸 What Is Iron Deficiency Anemia?

Iron Deficiency Anemia (IDA) occurs when your body doesn’t have enough iron to produce adequate hemoglobin — the oxygen-carrying part of red blood cells.

Without sufficient hemoglobin, your body is literally starved of oxygen. The result is a cascade of iron deficiency symptoms that affect everything from your physical energy to your brain function.

Primary Causes of Iron Deficiency Anemia

  • Poor dietary intake (especially common in vegetarians and vegans)
  • Heavy menstrual bleeding
  • Gastrointestinal issues such as ulcers, IBD, or celiac disease
  • Pregnancy (higher iron demands)
  • Chronic blood loss, including internal bleeding or frequent blood donation

Do Read: Iron Power: Essential Tips for a Healthy Pregnancy


🚨 15 Iron Deficiency Symptoms (Anemia Signs You Shouldn’t Ignore)

Iron deficiency anemia often develops slowly, and its signs can be surprisingly easy to dismiss. At first, you may simply feel a little tired or notice subtle changes in your appearance. However, as iron stores drop further, the symptoms intensify and begin to interfere with daily life. Below are the 15 most common anemia symptoms and low iron warning signs to watch for:


1. Persistent Fatigue — The Most Common Iron Deficiency Symptom

Even after a full night’s sleep, you still feel exhausted. This happens because low iron reduces hemoglobin, which means less oxygen reaches your muscles and tissues. The result? Energy levels plummet, leaving you drained all the time.


2. Pale or Yellowish Skin — A Visible Anemia Sign

One of the easiest low iron signs to spot is pallor. When hemoglobin levels drop, your blood loses its healthy red color. This can make your skin, lips, gums, and even the inner eyelids look pale or yellowish.


3. Shortness of Breath — A Classic Low Iron Symptom

Simple activities like walking across the room or climbing stairs suddenly leave you breathless. Since your body isn’t carrying enough oxygen, even small efforts can feel like a workout.


4. Heart Palpitations — Anemia Symptom Linked to Oxygen Shortage

Your heart may race, skip beats, or pound harder than usual. This happens because your cardiovascular system is working overtime to circulate what little oxygen is available. In severe cases, these palpitations can feel alarming.


5. Cold Hands and Feet — Circulatory Symptom of Low Iron

Poor oxygen delivery means your circulation suffers. Many people with iron deficiency anemia notice icy hands and feet, even in warm weather, because their blood flow is compromised.


6. Frequent Headaches or Dizziness — Brain-Related Iron Deficiency Symptoms

When the brain doesn’t get enough oxygen, you may develop pressure headaches, lightheadedness, or even spells of vertigo. This is one of the anemia symptoms most often mistaken for stress or dehydration.


7. Brittle or Spoon-Shaped Nails — Nail Changes from Iron Deficiency

Your nails may become thin, weak, or break easily. In some cases, they curve upward into a spoon-like shape, a condition known as koilonychia — a distinctive sign of chronic low iron.


8. Hair Loss or Thinning — A Low Iron Symptom Affecting Follicles

Iron is essential for healthy hair growth. When your body is deficient, hair follicles weaken, which may cause excessive shedding, thinning, or slower regrowth.


9. Sore or Swollen Tongue — Glossitis as an Anemia Sign

A smooth, inflamed, or painful tongue may point to iron deficiency anemia. Sometimes the tongue appears unusually red or swollen, and mouth sores may also develop.


10. Restless Legs Syndrome — Neurological Symptom of Low Iron

An uncontrollable urge to move your legs, especially at night, is strongly linked to low iron levels in the brain. This symptom can severely disrupt sleep quality.


11. Craving Non-Food Items (Pica) — Severe Iron Deficiency Warning Sign

People with advanced iron deficiency sometimes crave substances like ice, dirt, or chalk. This unusual condition, called pica, is considered a red flag for serious anemia symptoms.


12. Poor Concentration and Brain Fog — Cognitive Low Iron Symptom

Since your brain relies on oxygen for focus and memory, iron deficiency can lead to mental fatigue. Brain fog, poor productivity, and difficulty concentrating are common complaints.


13. Weakened Immunity — A Hidden Iron Deficiency Symptom

Iron plays a vital role in immune defense. Low levels can leave you prone to frequent infections, slow wound healing, and lingering colds or flu.


14. Chest Pain or Tightness — Serious Anemia Symptom

In severe cases, oxygen deprivation forces the heart to work harder, leading to chest pain or tightness. If this symptom appears, medical attention is urgent.


15. Mood Changes — Depression or Irritability from Low Iron

Iron supports neurotransmitters like dopamine and serotonin. When stores run low, mood swings, irritability, and even depression can surface as overlooked iron deficiency symptoms.


👨‍⚕️ Does Iron Deficiency Affect Men Differently?

While more common in women (due to menstruation and pregnancy), men are not immune to iron deficiency. In fact, symptoms in men often go unrecognized or misdiagnosed because they aren’t routinely screened.

Top Causes in Men:

  • Poor diet
  • Hidden GI bleeding (from ulcers, colon polyps, etc.)
  • Long-distance running (foot-strike hemolysis)
  • Regular blood donation

Unique Red Flags in Men:

  • Sudden fatigue or drop in exercise performance
  • Decreased libido or testosterone levels
  • Muscle weakness
  • Brain fog or irritability

If you’re a man experiencing these symptoms — especially if they appear suddenly — don’t ignore them.

Do Read: Iron: Mineral for Vitality and Health


🧪 How Is Iron Deficiency Diagnosed?

Iron deficiency anemia cannot be confirmed just by “feeling tired” — it requires proper blood tests for anemia and iron levels. Doctors usually order a series of lab tests to understand whether you simply have low iron stores or if it has already progressed to anemia. Here’s what to expect:

1. Complete Blood Count (CBC)

This is often the first test for diagnosing iron deficiency anemia. It measures hemoglobin, hematocrit, and red blood cell size. Low values often indicate anemia, but CBC alone cannot reveal how depleted your iron stores are.


2. Serum Ferritin

Ferritin reflects the amount of stored iron in your body. A ferritin level below 45 ng/mL is strongly suggestive of iron deficiency — even if hemoglobin levels are still in the “normal” range. This makes ferritin one of the most reliable early markers of low iron.


3. Serum Iron, TIBC, and Transferrin Saturation

  • Serum Iron measures the iron circulating in your blood at that moment.
  • Total Iron Binding Capacity (TIBC) indicates how much iron your blood could carry if more were available.
  • Transferrin Saturation (TSAT) shows the percentage of transferrin (the transport protein for iron) that is actually loaded with iron.

When combined, these results give a complete picture of iron metabolism and help doctors differentiate between iron deficiency, chronic disease, or other causes of anemia.


🔍 Pro Tip for Patients

If you suspect low iron symptoms like fatigue, hair loss, or brain fog, don’t just settle for a CBC. Always request a serum ferritin test. A normal hemoglobin level does not rule out early iron deficiency — ferritin often drops first, long before anemia is visible on standard blood counts.


🥦 Best Ways to Boost Your Iron Levels Naturally

If you’ve been diagnosed with iron deficiency anemia or you’re simply looking to prevent it, the good news is that there are several effective iron deficiency anemia treatment options. From dietary changes to medical interventions, you can restore healthy iron levels and regain your energy. Let’s walk through the most effective ways to treat iron deficiency step by step.


1. Eat More Iron-Rich Foods

The foundation of any iron deficiency anemia treatment plan starts with nutrition. Both heme iron (from animal foods) and non-heme iron (from plant-based sources) play a vital role in restoring iron levels.

✅ Best iron-rich foods include:

  • Red meat (beef, lamb, liver) – highly absorbable heme iron
  • Poultry and fish – lighter but still excellent sources
  • Dark leafy greens (spinach, kale, Swiss chard) – great for vegetarians
  • Lentils, chickpeas, beans – protein-packed plant-based options
  • Tofu and tempeh – soy-based, iron-dense foods
  • Fortified cereals and grains – quick and convenient
  • Pumpkin seeds and quinoa – nutrient-rich superfoods

👉 Pro tip: Combining both heme and non-heme iron foods in meals makes your iron deficiency treatment more effective.


2. Enhance Iron Absorption

Simply eating iron is not enough — how your body absorbs it matters. This step is crucial in treating iron deficiency anemia naturally.

✅ To improve absorption:

  • Pair meals with Vitamin C-rich foods like citrus, bell peppers, or tomatoes.
  • Try cooking in a cast iron skillet, which can naturally increase iron content in food.
  • Avoid tea, coffee, and milk during meals, as they interfere with absorption.

👉 Pro tip: Think of simple pairings — spinach + lemon juice, or lentils + tomatoes — for maximum absorption.


3. Consider Iron Supplements

When diet alone isn’t enough, iron supplements become an essential part of iron deficiency anemia treatment. They are especially important for those with heavy menstrual cycles, chronic conditions, or very low iron levels.

✅ Most common options:

  • Ferrous sulfate – the standard, cost-effective choice.
  • Iron bisglycinate – easier on the stomach, great for long-term use.

💊 How to use supplements effectively:

  • Take on an empty stomach, ideally with Vitamin C.
  • Avoid taking alongside calcium, tea, or coffee.
  • Start slow if digestive issues occur, then increase as tolerated.

👉 Pro tip: Always consult your doctor before starting supplements to avoid overloading your system.


4. IV Iron Therapy (Advanced Treatment Option)

For people with severe anemia, absorption issues, or urgent medical needs, IV iron therapy is a highly effective treatment for iron deficiency anemia.

  • It bypasses the digestive system and replenishes iron quickly.
  • Works faster than oral supplements.
  • Usually recommended only when other treatments aren’t effective.

👉 Pro tip: This should always be discussed with a healthcare professional, as IV iron therapy is a medical procedure.


✅ Bottom line: The most effective iron deficiency anemia treatment is often a combination of approaches. Start with iron-rich foods, enhance absorption with smart pairings, use iron supplements if necessary, and reserve IV iron for more serious cases. With consistent care, most people notice improved energy, focus, and overall health within just a few weeks.

Do Read: Healthy Iron Rich Pancake- Kid Friendly Recipe


🧾 Final Thoughts

Iron deficiency anemia doesn’t always make a dramatic entrance — instead, it creeps in quietly through signs like persistent fatigue, brain fog, brittle nails, and thinning hair. These subtle changes are easy to dismiss, but over time they can steal your energy, affect your mood, and impact your overall quality of life.

The encouraging news? Iron deficiency is one of the most easily diagnosed and treatable nutritional deficiencies. With the right blood tests, a tailored diet, and — if needed — iron supplements, most people can restore healthy levels within a few months. In other words, this condition is not just manageable, it’s completely reversible when addressed early.

If you’ve recognized yourself in the symptoms of iron deficiency anemia, don’t wait. Taking action now can help you reclaim your focus, boost your energy, and protect your long-term health. Your body — and your mind — will thank you for listening to those early whispers before they become a roar.


📌 Stay Informed. Stay Empowered.

Feeling tired shouldn’t be your normal. Don’t guess — get tested, eat smart, and supplement wisely.

➡️ For more wellness guides and nutrition-backed advice, visit MasalaMonk.com — where we break down ancient wisdom and modern science for better living.

🧠 Frequently Asked Questions (FAQs) About Iron Deficiency Anemia

1. What is the most common symptom of iron deficiency anemia?

The single most common and often first-noticed symptom of iron deficiency anemia is persistent fatigue. This isn’t the normal tiredness you feel after a long day — it’s a deep exhaustion that lingers even after adequate rest or sleep. Because iron plays a crucial role in transporting oxygen to your cells, low iron levels mean your muscles, organs, and brain don’t receive the oxygen they need. As a result, your energy supply runs low, leaving you drained, sluggish, and less productive throughout the day.

2. Can you be iron deficient without being anemic?

Yes — this condition is called iron deficiency without anemia (IDWA). In this case, your ferritin (iron storage) levels may be depleted, yet your hemoglobin remains in the “normal” range. Many people mistakenly believe they are fine because their blood counts appear healthy. However, the body can still show symptoms such as chronic fatigue, poor concentration, hair loss, or restless legs. In other words, even without full-blown anemia, low iron can negatively impact your health and daily performance.

3. How is iron deficiency anemia diagnosed?

Diagnosing iron deficiency anemia typically requires a combination of blood tests rather than relying on one single marker. Doctors often start with a Complete Blood Count (CBC) to check hemoglobin and red blood cell size. Next, serum ferritin is measured to assess iron stores — values below 45 ng/mL strongly suggest deficiency, even if hemoglobin is normal. Additional tests, such as serum iron, Total Iron Binding Capacity (TIBC), and transferrin saturation, provide a complete picture of how your body is using and transporting iron. Together, these tests ensure nothing is missed.

4. What are unusual or hidden symptoms of iron deficiency anemia?

Beyond the “classic” signs like fatigue and pale skin, unusual iron deficiency symptoms can also appear. For example, some people develop pica — a craving for non-food substances like ice, chalk, or even dirt. Others may experience restless legs syndrome, where an uncontrollable urge to move the legs disrupts sleep. Another lesser-known sign is beeturia — reddish-colored urine after eating beets, which may indicate altered iron metabolism. While these symptoms might seem unrelated, together they can be powerful red flags of low iron levels.

5. Is iron deficiency anemia common in men?

While women are more frequently affected due to menstruation and pregnancy, iron deficiency in men is still a significant concern. In fact, when men develop anemia, it’s often linked to hidden causes such as gastrointestinal bleeding from ulcers, colon polyps, or even colorectal cancer. Men may also experience low iron from poor diets, frequent blood donation, or endurance sports like long-distance running. Because routine screening for men is less common, many cases go undiagnosed until symptoms such as fatigue, reduced exercise performance, or low testosterone become noticeable.

6. How long does it take to correct iron deficiency anemia?

The timeline for recovery depends on the severity of your deficiency. Most people notice improvement in symptoms like fatigue and focus within 2 to 4 weeks of treatment. However, restoring iron stores completely can take 3 to 6 months or longer, especially if the underlying cause (like heavy menstrual bleeding or GI bleeding) is not addressed. Consistency with supplements, diet changes, and medical follow-up plays a big role in how quickly you’ll recover.

7. What foods should I avoid when trying to absorb more iron?

When boosting iron intake, it’s just as important to know what blocks iron absorption as it is to eat iron-rich foods. Be cautious with tea and coffee, which contain tannins that bind iron and make it harder to absorb. Similarly, calcium-rich foods (like milk or cheese) and high-fiber cereals (with phytates) can interfere when consumed alongside iron-rich meals. A better strategy is to consume these foods at different times of the day and pair your iron intake with vitamin C sources such as citrus fruits, which enhance absorption.

8. Can iron supplements cause side effects?

Yes. While iron supplements are highly effective, some types can cause side effects. Ferrous sulfate, the most commonly prescribed form, may lead to constipation, nausea, or dark stools. If you experience digestive discomfort, switching to gentler forms like iron bisglycinate or ferrous gluconate can help. Drinking plenty of water, adding fiber to your diet, and starting with a lower dose before building up can also reduce side effects. Always consult your doctor before switching supplements.

9. What’s the best time to take iron supplements?

The most effective way to take iron supplements is on an empty stomach — ideally one hour before meals. Taking them with a small dose of vitamin C (such as orange juice) improves absorption significantly. On the other hand, avoid pairing iron with milk, coffee, or calcium supplements, as these reduce absorption. If taking iron on an empty stomach upsets your stomach, you can take it with a small snack, but avoid blockers during that meal. Consistency is key, so pick a routine you can stick to daily.

10. When should I see a doctor about low iron symptoms?

You should see a healthcare professional if you notice persistent iron deficiency symptoms such as unexplained fatigue, pale skin, shortness of breath, dizziness, or rapid heartbeat. These may indicate anemia or another underlying issue that requires medical evaluation. Because low iron can sometimes signal hidden conditions — like gastrointestinal bleeding or chronic disease — it’s essential not to self-diagnose. A simple blood test can confirm whether you have iron deficiency anemia and help guide safe, effective treatment.

📚 Scientific References

  1. American Family Physician (AAFP). Iron Deficiency Anemia: Guidelines from the American Gastroenterological Association. August 2021. Link
    → Establishes serum ferritin < 45 ng/mL as a reliable threshold for diagnosing iron deficiency anemia.
  2. Medscape. Iron Deficiency Anemia Guidelines Summary. Updated 2023. Link
    → Outlines modern diagnostic strategies, including ferritin, TIBC, and transferrin saturation.
  3. JAMA Network Open (via Health.com). Large Percentage of U.S. Adults Are Iron Deficient, Study Finds. 2024. Link
    → Recent population-based study highlighting prevalence of both absolute and functional iron deficiency.
  4. Medscape. Iron Deficiency Anemia: Overview. Updated 2023. Link
    → Detailed overview of signs, symptoms, and complications — from fatigue and pica to glossitis and cognitive changes.
  5. Xinyu Mei, et al. Iron deficiency anemia in children: A comprehensive review. Journal of Xiangya Medicine (2021). Link
    → Explains the physiological stages of iron depletion and its clinical manifestations.
  6. Wikipedia. Iron-Deficiency Anemia. Link
    → Concise summary of causes, mechanisms, and risk factors, including blood loss, diet, and malabsorption.
  7. P.M.C. (PubMed Central). Iron Deficiency and Oxidative Stress in Red Blood Cells. Link
    → Demonstrates how low iron contributes to oxidative stress and red blood cell damage.
  8. ScienceDirect. Oxidative Stress in Children with Mild Iron Deficiency Anemia. 2023. Link
    → Shows that even mild anemia can impair antioxidant defenses and overall cellular health.
Posted on — 1 Comment

Side Effects of Wegovy: What Users Are Reporting

Wegovy Side Effects:

Wegovy (semaglutide) has changed the weight loss conversation worldwide. For many, it offers hope where diet and willpower alone have failed. But as anyone scrolling through Reddit or support groups quickly learns, the Wegovy journey can be bumpy. Side effects—ranging from mild annoyances to distressing surprises—are commonplace. If you’re about to start Wegovy or are somewhere along your journey, here’s what you truly need to know, in the words of those who’ve been there, plus hard-won tips from both medical experts and the user community.


What Most People Experience: The GI Rollercoaster

Ask anyone who’s taken Wegovy about side effects and you’ll hear about nausea, vomiting, diarrhea, and constipation—sometimes all at once, sometimes switching back and forth without warning. In fact, up to 70% of people experience some kind of digestive trouble, and it’s the most frequent reason people pause, lower their dose, or quit entirely.

One user put it bluntly:

“Wegovy is a miracle for weight loss, but my gut hates me right now. Week 3 and I feel like I’m either glued to the bathroom or terrified to leave the house.”

Another echoed the unpredictable nature:

“It started as mild nausea, then suddenly I was hit with the worst diarrhea of my life. Then I’d have days where I just couldn’t go at all. I learned to keep Imodium and stool softeners on hand.”

Many find that GI symptoms are worst right after injections (usually once a week), with symptoms peaking during dose increases. The first two months are often the hardest. For some, symptoms fade; for others, they linger or even recur months later.

Notable user themes:

  • Food aversion: Some find that even thinking about food makes them queasy. “The ‘food ick’ was real for me. I’d open the fridge and gag. Lost 10 lbs in 3 weeks but it wasn’t fun.”
  • Vomiting surprises: Several people describe sudden, “thick” vomit episodes with little warning—even after months of smooth sailing.
  • Constipation frustration: Others say constipation is so severe it’s “like passing rocks.” Some have gone over a week without relief, requiring interventions like Miralax, prunes, or prescription meds.

Fatigue, Brain Fog, and the Unexpected Tiredness

Beyond GI drama, fatigue is another common thread, especially in the early weeks or after dose increases. Some users describe a “zombie” feeling, sleeping 10-12 hours and still waking up tired.

One Redditor wrote:

“After my second shot I slept all weekend. Just…exhausted. It’s like my body was busy adapting and I couldn’t do anything else.”

Others talk about brain fog—feeling scattered, forgetful, or struggling to concentrate. This sometimes fades after the first month, but for a minority, it can persist and requires adjusting routines to accommodate lower energy.

Practical user strategies:

  • Plan demanding activities for times you’re most alert.
  • Listen to your body—rest is part of the process.
  • Check your hydration and nutrition (low blood sugar or dehydration can worsen tiredness).

Appetite Suppression: When “Food Noise” Goes Silent

One of Wegovy’s biggest draws is its ability to silence cravings—sometimes too well. People talk about going an entire day without realizing they haven’t eaten, or having to force down protein shakes because nothing sounds appealing.

“My hunger disappeared. I had to set alarms to remind myself to eat because I’d go 8 hours and not even think about food. Kind of amazing, but also weirdly unsettling.”

Some people find this liberating (“No more nightly kitchen raids!”), while others worry about under-eating and nutrient deficiencies. A few mention developing an almost fear of eating, associating meals with potential nausea.


Lesser-Known Side Effects and Surprises

Hair Loss

A growing number of users—especially women—report hair thinning after several months. This tends to occur in people losing weight rapidly, but some attribute it directly to Wegovy.

“Three months in, the weight was flying off, but so was my hair. My shower drain looked like a cat was shedding. It eventually slowed down, but it was scary.”

Medical experts believe this is often telogen effluvium, a temporary shedding triggered by rapid changes in weight, stress, or diet. It typically resolves within a few months, especially with good nutrition.

Mental Health and Mood Shifts

While some report improved mental clarity or reduced anxiety (possibly from breaking food-related cycles), others note increased irritability, anxiety, insomnia, and even depression:

“I felt more snappy and down after a month on Wegovy. I wasn’t expecting mental effects, but they were real.”

Some rare cases of mood changes or suicidal thoughts have been documented, prompting ongoing research and caution for those with a mental health history.

Sleep Changes

  • Vivid dreams and even nightmares are reported, mostly during dose escalation or when feeling unwell.
  • Some mention insomnia or disrupted sleep patterns, especially on injection days.

Vision Issues and Rare Risks

Emerging reports have highlighted cases of sudden vision changes, such as non-arteritic anterior ischemic optic neuropathy (NAION) and, less commonly, macular degeneration. These are rare but very serious.

“I had blurry vision after starting Wegovy, which eventually resolved. But after reading about the risks, I went to get my eyes checked—better safe than sorry.”

Muscle Loss Concerns

Rapid weight loss can mean losing muscle as well as fat. Recent studies show that people on semaglutide can lose a concerning amount of lean mass—especially older adults and those eating too little protein.

“After 4 months and 40 lbs lost, I noticed I felt weaker. My doctor had me increase protein and start lifting weights, which helped.”

Gallbladder and Pancreatitis

  • Several users have reported gallstones, gallbladder attacks, or even pancreatitis.
  • Symptoms include severe upper abdominal pain, especially if accompanied by vomiting or fever—these warrant immediate medical attention.

Dry Mouth, Taste Changes, and “Ozempic Mouth”

Persistent dry mouth, an altered or metallic taste, and mouth discomfort (“Ozempic mouth”) are increasingly common reports.

“I was constantly thirsty and my mouth felt like sandpaper. Chewing sugar-free gum helped a bit.”


Late-Onset and Long-Term Effects: Not Just an Early Hurdle

While many expect the first month to be the hardest, several users describe side effects re-emerging after months of stability.

“I was fine for nearly a year, then the nausea and vomiting returned out of nowhere. My doc said it can happen if you lose a lot of weight or change your dose.”

This late-onset phenomenon reminds users to remain vigilant, track symptoms, and never assume they’re “done” with side effects.


Positive Side Effects: Surprising Benefits

It’s not all negative. Some people notice unexpected improvements:

  • Less joint pain (possibly from weight loss, but sometimes noted before major loss occurs)
  • Improved mood, reduced food-related anxiety, and greater focus
  • Better control over impulsive behaviors, including those unrelated to food

One user shared:

“My skin picking got better, and my ADHD symptoms actually improved. I wasn’t expecting that!”


When to Get Help: Red Flags You Shouldn’t Ignore

While most symptoms can be managed at home, some should trigger an immediate call to your doctor or a trip to urgent care:

  • Severe or persistent vomiting/diarrhea (risk of dehydration)
  • Severe abdominal pain, especially with fever or vomiting (possible pancreatitis/gallbladder attack)
  • Sudden changes in vision
  • Allergic reactions: swelling, trouble breathing, rash
  • Serious mood changes, thoughts of self-harm or suicide

Most Common Side Effects: What to Expect

Gastrointestinal (GI) Upset: The #1 Complaint

  • Nausea and Vomiting: Up to 44% of users experience nausea, sometimes leading to vomiting. This typically peaks after an injection and during dose escalations.
  • Constipation: Very common. Some users say, “I didn’t go for a week.” Others battle alternating diarrhea and constipation.
  • Diarrhea and Abdominal Cramps: For some, it’s diarrhea instead—sometimes severe enough to interfere with work or sleep.
  • Heartburn, Bloating, and Burping: Not unusual, and sometimes persistent.

Reddit User:

“Started fine, but in week three, the nausea and vomiting hit hard. Some days I couldn’t keep food down, other days it was just a low-level queasiness.” (reddit.com)

Fatigue and Low Energy

  • Many users describe overwhelming tiredness, especially during the first few weeks. This can come and go, sometimes lasting for months.
  • Some also report dizziness, headaches, or difficulty concentrating.

Practical Tip:
Plan your most demanding tasks for times when you feel your best, and prioritize rest if you feel wiped out.

Appetite Suppression & “Food Apathy”

  • This is the intended effect, but for some, it’s so strong they forget to eat or struggle to meet basic nutrition needs.
  • “Food noise” (constant food thoughts) often vanishes—but so can interest in eating altogether.

Injection Site Issues

  • Mild redness, irritation, or swelling at the injection site is common, but usually fades quickly.

Lesser-Known and Rare Risks

Hair Loss (Telogen Effluvium)

  • A surprising number of users—especially women—report increased hair shedding after months of use. While often temporary, it can be distressing.

Mood and Mental Health Shifts

  • Some users report increased anxiety, irritability, or even episodes of depression.
  • Conversely, others notice reduced anxiety and improved focus.

Vision Issues

  • Rare but serious: sudden changes in vision (including partial blindness) have been reported and are now acknowledged by regulatory agencies as possible, albeit very rare, risks.

Muscle Loss

  • Recent research highlights significant muscle loss with rapid weight reduction—especially if protein intake is low or resistance exercise is lacking.

Pancreatitis and Gallbladder Problems

  • Rare but very serious: severe abdominal pain, especially with vomiting or fever, may signal these complications. Immediate medical attention is required.

Dry Mouth and Taste Changes

  • Increasingly reported: persistent dry mouth (“Ozempic mouth”) and sometimes metallic or altered taste.

User Voices: Real Stories from the Wegovy Community

A. Long-Term Surprises

“I was a year in, doing great—then suddenly the nausea came back. Dry heaving in the morning, unpredictable diarrhea. Had to rethink my meal timing and go back to basics.”

B. First-Dose Shocks

“Day one, I felt like I’d been hit by a truck. Fatigue, a weird dizzy fog, constipation for a week… but after a month, things got much easier.”

C. Sudden “Food Ick”

“Just looking at food made me queasy for weeks. Lost 10 pounds in the first month without really trying, but needed protein shakes to keep from feeling weak.”

D. Positive “Side Benefits”

“My anxiety’s been better, and my joint pain improved—wasn’t expecting that at all.”

E. Persistent Minor Annoyances

“Burping, heartburn, burning bladder feeling… small stuff, but it adds up when you’re dealing with it every day.”


How Real Users Cope: Practical, Battle-Tested Advice

Go Slow and Listen to Your Body

  • Many users find that sticking to the slowest possible dose escalation dramatically reduces side effects.
  • If side effects become unmanageable, don’t hesitate to ask your prescriber to pause or reduce the dose. Pushing through can backfire.

Dietary Hacks

  • Eat small, bland meals—think crackers, rice, bananas, boiled chicken.
  • Avoid greasy, spicy, or high-fiber foods on injection days if you’re prone to GI symptoms.
  • Protein shakes, Greek yogurt, and eggs are popular among users struggling to eat enough.

“I kept a log of what made me feel sick and what I could tolerate. Plain toast saved me on bad days.”

Hydration Is Crucial

  • Aim for at least 8 glasses of water per day, more if experiencing diarrhea or vomiting.
  • Electrolyte solutions (like Pedialyte) can help if you’re losing fluids quickly.

Manage Constipation and Diarrhea

  • For constipation: fiber supplements (as tolerated), stool softeners, and gentle laxatives.
  • For diarrhea: Imodium (with your doctor’s approval), and a bland, binding diet.

Combatting Dry Mouth and Taste Changes

  • Sugar-free gum, lozenges, and frequent sips of water.
  • A humidifier at night can help with mouth dryness.

Protect Your Muscles

  • Include resistance training (even light weights or bands) 2-3 times a week.
  • Ensure adequate protein intake (at least 1.2–1.6 grams per kg of body weight daily).
  • Don’t shy away from consulting a dietitian.

Track Symptoms and Patterns

  • Many users keep journals noting side effects, food intake, and injection days. This can help identify triggers or trends and is invaluable when discussing issues with your doctor.

Mental Health Self-Care

  • Reach out to friends, family, or support groups.
  • Don’t dismiss changes in mood or mental health. Seek professional support if needed.

Tap Into Community Wisdom

Reddit’s r/WegovyWeightLoss and similar forums are goldmines for practical solutions, solidarity, and humor. You’re not alone, and someone has probably found a workaround for whatever you’re dealing with.


Living With Wegovy: The Honest Truth

Wegovy is not a magic pill. For most, it’s a tradeoff—a chance at significant weight loss, but often at the cost of temporary (or sometimes persistent) side effects. Some breeze through with minor issues. Others face tougher challenges, ranging from manageable to severe.

What sets successful users apart is not just luck, but preparation and adaptability:

  • They start slow, adjust fast, and ask for help early.
  • They’re not afraid to pause or step back if their body needs it.
  • They invest in their nutrition, movement, and mental health as much as in the medication itself.

If you’re about to start Wegovy or are deep into the journey, know this: you’re not crazy, you’re not weak, and you’re definitely not alone. Real people all over the world are working through the same side effects, making adjustments, and finding ways to thrive.


Have a Wegovy Story?

What have you experienced on Wegovy? What’s helped, what hasn’t, and what do you wish you’d known sooner? Sharing stories not only helps others, it helps us all advocate for better care and more honest conversations about this powerful, complicated medication.


Disclaimer: This post is based on real-world reports and expert advice, but it is not a substitute for personalized medical care. Always consult your healthcare provider about medication questions and side effect management.

Wegovy Side Effects: Top 10 FAQs

1. What are the most common side effects of Wegovy?
The most common side effects are gastrointestinal—nausea, vomiting, diarrhea, constipation, and abdominal pain. Fatigue and headaches are also reported. Most symptoms are worst in the first 1–2 months or after dose increases, then often improve.

2. Are Wegovy side effects permanent?
Most side effects are temporary and lessen over time, especially GI symptoms. However, some users experience side effects that persist or reappear later, such as fatigue or GI issues after months of use.

3. What should I do if I get severe nausea or vomiting?
Stay hydrated and stick to bland foods. Talk to your provider about anti-nausea medications. If vomiting is severe or persistent, pause the next dose and consult your doctor right away.

4. Is hair loss normal with Wegovy?
Hair thinning (telogen effluvium) can occur, especially with rapid weight loss. It is typically temporary and can be minimized with good nutrition, stress management, and proper protein intake.

5. How can I prevent muscle loss while on Wegovy?
Prioritize protein intake (1.2–1.6g/kg of body weight) and incorporate resistance or strength training 2–3 times per week to help preserve muscle.

6. What are the rare but serious side effects I should watch for?
Serious risks include pancreatitis, gallbladder problems, vision changes, severe allergic reactions, and (rarely) mood changes or suicidal thoughts. Seek immediate medical help for severe abdominal pain, vision changes, or mental health crises.

7. Can Wegovy affect mental health?
Some users report mood swings, irritability, anxiety, or even depression, though others notice improvements. Be alert for mental health changes and reach out for professional support if needed.

8. What can help with dry mouth or taste changes?
Drink plenty of water, use sugar-free gum or lozenges, and consider a humidifier at night. Most taste and dry mouth issues are mild and manageable.

9. Is it okay to pause or reduce my dose if side effects are bad?
Yes, many users benefit from slowing down dose increases or even dropping back to a lower dose temporarily. Always coordinate changes with your healthcare provider.

10. Where can I find real support and advice from others using Wegovy?
Online communities like Reddit’s r/WegovyWeightLoss, Facebook groups, and patient forums are excellent places to share experiences, find advice, and get moral support from people on the same journey.

Posted on — Leave a comment

Nettle Tea for Radiant Skin and Luscious Hair

NETTLE TEA FOR RADIANT SKIN AND LUSCIOUS HAIR

When you think of glowing skin and luxurious hair, stinging nettle (Urtica dioica) might not be the first plant that comes to mind. But this prickly wild herb—once notorious for its painful sting—has quietly earned superstar status among herbalists, beauty experts, and wellness enthusiasts. In this post, we’ll explore why nettle tea is having a major moment, what the latest science says, and how to make this ancient tonic work for you—inside and out.


Why Nettle? A Quick Introduction

Nettle is not a new trend. It’s been used for centuries as a healing tonic across Europe, Asia, and North America. What’s changed? Modern research is now catching up to folk wisdom, revealing how nettle supports healthy skin, robust hair, and overall wellbeing.

Key nutrients in nettle leaves:

  • Vitamins A, C, D, E, and several B vitamins
  • Iron, magnesium, silica, calcium, potassium
  • Polyphenols and antioxidants

Nettle delivers a rare combination: deep nourishment, anti-inflammatory action, hormone-balancing effects, and gentle detox—all in a single cup of tea.


How Nettle Tea Benefits Skin and Hair (with Latest Evidence)

1. Nutrient-Rich for Cellular Repair

Your skin and hair are some of the first places to show nutrient imbalances or oxidative stress. Nettle tea provides bioavailable vitamins and minerals critical for:

  • Collagen synthesis (vitamin C, silica)
  • Wound healing (vitamin K, magnesium)
  • Strong, shiny hair shafts (iron, folate, biotin)

2. Anti-Inflammatory and Antioxidant Effects

Nettle contains carotenoids, polyphenols, and flavonoids that help calm chronic inflammation—a root cause of acne, eczema, redness, and even scalp irritation. By fighting free radicals, nettle may help prevent premature aging and dullness.

2025 Research Spotlight:
In silico studies confirm nettle’s antioxidants effectively neutralize skin-damaging free radicals and reduce inflammatory markers in both scalp and dermal cells.

3. DHT Blocking for Hair Growth

One of nettle’s standout benefits: it inhibits 5α‑reductase, the enzyme that converts testosterone to DHT—a key player in pattern hair loss. While more research is needed on nettle tea specifically, clinical trials with nettle-based shampoos and serums found:

  • Up to 90% reduction in hair loss after 6 months (compared to ~40% in placebo group)
  • Increased hair density and reduced shedding

4. Improves Scalp and Skin Circulation

Compounds like beta-sitosterol in nettle help enhance microcirculation. This means more oxygen and nutrients reach your scalp and skin, supporting growth and repair.

5. Sebum Regulation

Nettle has a natural balancing effect on oil production, making it a smart addition for both oily and combination skin types, as well as greasy scalp and hair.


How to Use Nettle for Beauty: Tea, Topical, and More

Here’s how to make nettle part of your beauty routine for maximum benefit:

1. Drink It: Daily Nettle Tea Ritual

  • How: Steep 1-2 teaspoons of dried nettle leaf in hot water for 5–10 minutes. Strain and enjoy 1–2 cups per day.
  • Flavor tip: Add a squeeze of lemon, honey, or mint to offset the earthy taste.
  • What to expect: Gradual, steady improvements. Most people report brighter skin and thicker hair after 2–3 months of regular use.

Pro Tip:
Nettle’s natural diuretic effect helps flush toxins, but be sure to stay hydrated!

2. Apply Topically: Rinses, Oils, and Masks

DIY Nettle Hair Rinse:

  • Steep 1–2 tablespoons dried nettle in 2 cups boiling water.
  • Cool, strain, and pour over clean, damp hair as a final rinse.
  • Massage gently into scalp; do not rinse out immediately.

Nettle-Infused Face Mist:

  • Brew strong nettle tea, allow to cool, and pour into a spray bottle.
  • Mist onto cleansed skin as a natural toner to soothe inflammation and balance oil.

Nettle Oil for Scalp:

  • Blend nettle-infused oil (or purchase pre-made) with a few drops of rosemary or peppermint oil.
  • Massage into scalp weekly to stimulate follicles and ease dryness or dandruff.

3. Supplements and Serums

  • Capsules or tinctures: Consider 500–1000 mg/day, but check with your doctor, especially if you take medication.
  • Serums and shampoos: Look for high-quality, standardized nettle extract near the top of ingredient lists.

Real-World Stories

“I started using nettle tea as a last resort for postpartum hair shedding. Three months in, my hair feels stronger and I have fewer breakouts. The results are real!”
— Jane D., London

“Nettle rinses brought shine back to my curls and calmed my itchy scalp. I wish I’d known about this years ago!”
— Tyler S., NYC


What Science Still Can’t Prove (Yet)

While early results and centuries of folk wisdom are promising, large-scale clinical trials on nettle tea for skin and hair are limited. Most studies focus on topical extracts, not tea. Individual response can vary based on genetics, hormones, and overall lifestyle.


Are There Any Side Effects?

  • Nettle is safe for most adults when used appropriately.
  • If you are pregnant, breastfeeding, or on blood thinners or diuretics, consult your healthcare provider first.
  • Some people report mild digestive upset or allergic reactions—start with a small amount and monitor your response.

Making Nettle Tea a Ritual (That Sticks)

  • Start a 30-day nettle challenge: Take a selfie before, and again at 4 and 8 weeks to track progress.
  • Pair with mindful moments—use tea time as a reset from your daily hustle.
  • Invite a friend to join—rituals are easier (and more fun) together!

Final Take: Should You Try Nettle Tea?

If you’re seeking a simple, holistic way to support radiant skin and healthy hair, nettle tea is an easy, affordable, and evidence-backed place to start. While it’s not a miracle cure, it’s a powerful ally—especially when combined with good sleep, a balanced diet, and gentle self-care.

Ready to get started?
Brew a cup, embrace the ritual, and let nature’s pharmacy nourish you from root to tip.

FAQs: Nettle Tea for Skin and Hair

1. Can anyone drink nettle tea, or are there people who should avoid it?
Most healthy adults can safely enjoy nettle tea. However, pregnant or breastfeeding individuals, and those taking blood thinners, blood pressure medications, or diuretics should consult their healthcare provider before starting nettle due to possible interactions.

2. How quickly can I expect to see results in my skin or hair after starting nettle tea?
Most people notice subtle improvements in 4–8 weeks of consistent use, but individual response varies based on lifestyle, diet, and genetics. For some, hair shedding decreases after a month; for others, it may take longer.

3. Does nettle tea taste good? Can I improve the flavor?
Nettle tea has an earthy, grassy flavor. To make it tastier, add lemon, honey, fresh mint, or blend it with green or herbal teas.

4. Is there a difference between using nettle tea and nettle extract for hair and skin?
Nettle extract (used in serums or shampoos) is more concentrated for topical benefits and often used in clinical studies. Nettle tea offers systemic support and nutrient intake, best for overall health and gentle, ongoing benefits.

5. Can I use nettle tea directly on my hair and skin?
Yes! Use cooled, strained nettle tea as a hair rinse, facial mist, or gentle toner. Always patch-test before widespread use, especially if you have sensitive skin.

6. Where can I buy high-quality nettle tea?
Look for organic dried nettle leaves from health food stores, reputable online herbal retailers, or specialty tea shops. Avoid products with fillers or artificial flavors.

7. Can I make nettle tea from fresh nettle leaves?
Yes, but always wear gloves to avoid stings before steeping. Rinse thoroughly and steep as you would dried nettle (using a bit more volume for fresh leaves).

8. Are there any side effects of drinking too much nettle tea?
Overconsumption may cause upset stomach, mild diuretic effects (increased urination), or rare allergic reactions. Stick to 1–2 cups daily unless otherwise advised by your doctor.

9. Will nettle tea interfere with other supplements or medications?
It may interact with blood pressure drugs, blood thinners, and diuretics. Always check with your healthcare provider if you are on regular medication.

10. Can I combine nettle tea with other natural remedies for better results?
Absolutely! Many people pair nettle with herbs like horsetail, rosemary, or saw palmetto for enhanced hair benefits. For skin, pair with chamomile or calendula. Always introduce new botanicals one at a time to monitor effects.

Posted on — Leave a comment

Creatine Uncovered: The Science, Benefits, and Myths

Athletic woman in a sunlit gym holding a clear shaker beside a small bowl and scoop of white creatine powder, with the title “Creatine Uncovered: The science, benefits & myths.”

Updated:

This guide has been substantially revised to include newer evidence on creatine and kidney function, hair loss, strength, body composition, cognition, postmenopausal women and safety.

Creatine used to be easy to understand. Lifters took it because it helped them train harder and get stronger.

Now someone is taking it for menopause. Someone else is worried it will ruin their kidneys. And someone who has never touched a barbell is considering it for their brain while quietly wondering what that daily scoop might do to their hairline.

Creatine deserves neither the old fear nor the new mythology.

Creatine: the short answer

If you are standing in front of a tub wondering what matters, start here.

  • Creatine works best where the evidence is deepest: resistance-training strength, repeated high-intensity exercise and somewhat greater lean-mass gains alongside training.
  • Creatine monohydrate is the default form to buy. More expensive alternatives have not convincingly shown that they work better.
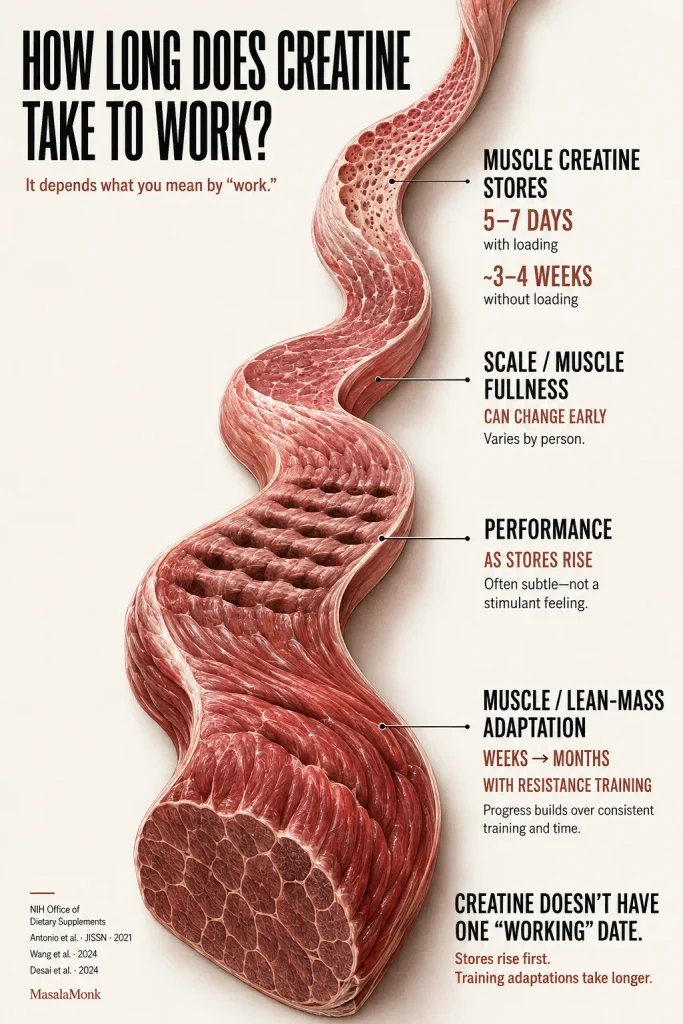
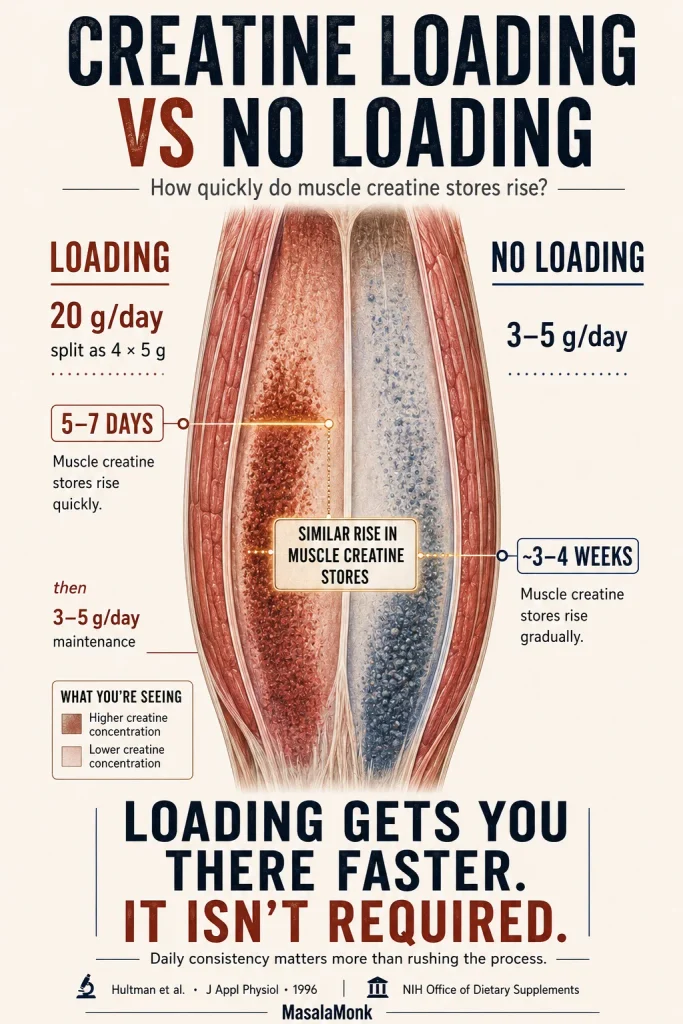
  • For most healthy adults who choose to supplement, 3–5 g/day is a simple routine. Loading is optional: about 20 g/day split into four doses for 5–7 days raises stores faster, while a smaller daily dose gets there more gradually.
  • Consistency matters more than a perfect workout window. Rest days use the same daily routine, and routine cycling is not established as necessary.
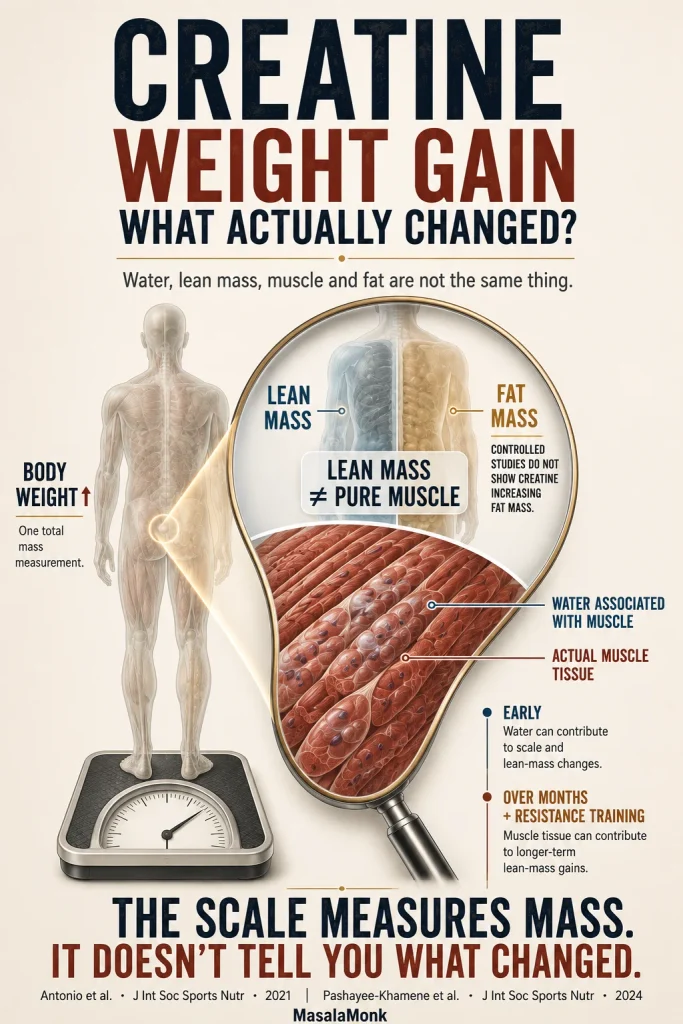
  • Early scale weight can rise. Water associated with muscle can contribute, so a quick increase does not tell you that you gained the same amount of fat—or pure new muscle.
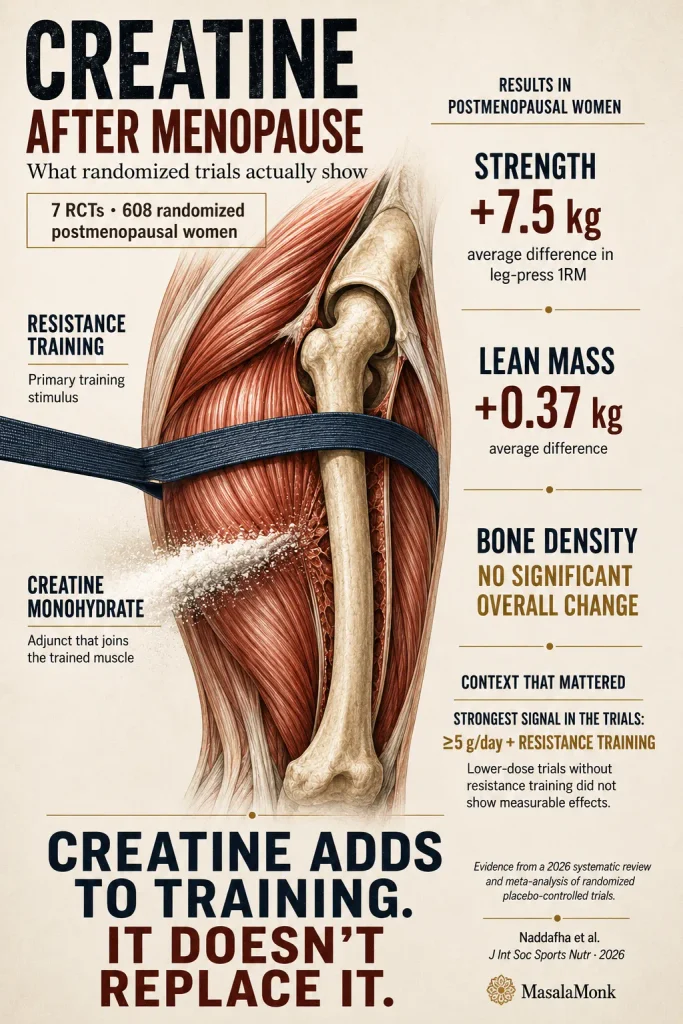
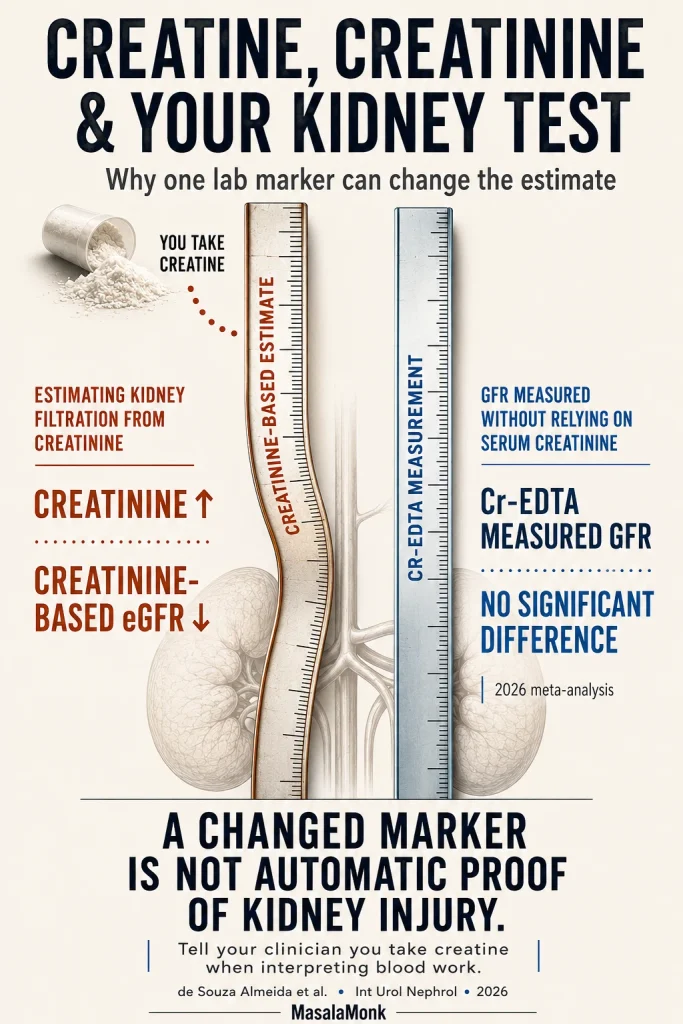
  • The healthy-adult safety literature is reassuring, while newer claims deserve different levels of confidence. Creatinine-based kidney tests can be affected by creatine use; direct hair-loss evidence is reassuring; memory and postmenopausal findings are promising but narrower than the marketing often suggests.

Creatine monohydrate remains the most studied form, and the NIH Office of Dietary Supplements summarizes the common loading and non-loading approaches used in research.

What is creatine actually good for?

The internet tends to flatten very different claims into one enormous list of “creatine benefits.”

The evidence falls into very different tiers.

Creatine evidence graphic organizing benefits by strength of research, with the clearest support for strength, repeated high-intensity performance and resistance-training outcomes, while cognition and recovery are less certain and endurance benefits are weaker.
Use the evidence hierarchy as a filter whenever you encounter a new creatine benefit claim. Ask what researchers actually measured: a real performance or health outcome, a surrogate marker, or merely a plausible mechanism. Mechanisms are useful reasons to investigate an idea; they should not automatically be promoted to the same status as replicated human outcomes.
OutcomeWhere the evidence stands
Strength with resistance trainingStrong
Repeated high-intensity exerciseStrong
Additional lean-mass gains with resistance trainingStrong
Lean mass and strength in some older adults alongside resistance trainingGood evidence
Lean mass and strength after menopause, particularly with resistance trainingPromising / increasingly supported
Memory and some cognitive outcomesPromising, but mixed overall
Long-duration endurance performanceNo meaningful overall benefit established
Soreness and faster recovery from every workoutMixed
Direct fat lossNot established
Where creatine has its strongest outcome evidence—and where expectations should stay lower.

That difference between established, promising and plausible matters throughout this subject.

What creatine does inside your muscles

Your body already makes creatine, and foods such as meat and fish provide additional dietary creatine.

Most of the body’s creatine is stored in skeletal muscle. Some exists as phosphocreatine, which helps regenerate ATP when energy demand rises very quickly.

You do not need the biochemistry-textbook version to understand the practical consequence.

Think of phosphocreatine as part of a small, rapidly available energy reserve. Increasing muscle creatine gives that system more capacity.

That becomes particularly useful when the work is hard, short and repeated: another heavy set, another sprint, another explosive effort.

What will you actually notice after starting creatine?

Imagine you begin taking 3–5 g of creatine monohydrate every day.

Your muscle creatine stores gradually rise. Loading makes that happen faster; smaller daily dosing gets there more gradually. NIH Office of Dietary Supplements

The scale may move before your gym numbers do.

Your muscles may look a little fuller.

And you may feel…exactly the same.

That last part catches people out. Creatine is not caffeine. There is no required buzz or dramatic moment when it “kicks in.” Its benefit often appears in repeated work: maintaining performance a little better, completing slightly more useful training, or accumulating better sessions over time.

If you have taken creatine for three weeks and are thinking, I can’t feel anything, that does not automatically mean you need more.

A continuous muscle-ribbon timeline shows creatine stores rising in about 5–7 days with loading or 3–4 weeks without loading, followed by possible performance changes and slower muscle or lean-mass adaptation over weeks to months with resistance training.
If you want to judge whether creatine is helping, “Can I feel it?” is a poor test. Instead, keep the routine stable and watch what happens across repeated training sessions. Creatine can be doing its job without producing a buzz, pump or obvious moment when it suddenly switches on.

What about over months rather than days?

This is where supplementation and training become much more interesting.

A 2024 meta-analysis of resistance training and body composition found that adults under 50 who combined creatine with resistance training gained about 1.14 kg more lean body mass than those doing resistance training without creatine. Small favourable changes in body-fat measures were also reported.

That is not evidence that one scoop manufactures a kilogram of muscle. It is evidence that creatine can help resistance training produce somewhat greater adaptations over time.

Where creatine earns its reputation

Strength

This remains one of the clearest cases for taking creatine.

A 2025 systematic review and meta-analysis of 69 studies involving 1,937 adults separated several common strength tests instead of collapsing them into one upper- or lower-body number. Compared with placebo, creatine plus resistance training produced statistically significant pooled improvements in bench/chest press strength (+1.43 kg) and squat strength (+5.64 kg).

The same analysis did not find statistically significant overall differences for leg press or handgrip strength. It also reported significant improvements in vertical jump and Wingate peak power, reinforcing that creatine’s performance signal depends partly on the outcome being tested.

Those values are pooled group averages, not predictions for your next personal record. Different exercises, populations, training programs and study designs produce different estimates. Overall, resistance training tends to produce somewhat greater strength and power gains when creatine is added, but there is no single universal “creatine strength increase.”

Four female athletes perform a bench or chest press, squat, leg press and handgrip test; pooled results show a 1.43 kg average improvement for bench or chest press and 5.64 kg for squat, with no significant overall difference for leg press or handgrip.
Exercise-specific results should not be read as “creatine works for squats but not leg press.” Different pooled outcomes contain different studies, people and training protocols. More importantly, creatine can add a modest training advantage on average, while the size of that advantage is not fixed across every exercise or lifter.

Repeated high-intensity exercise

Creatine also performs well in activities built around short, hard efforts with limited recovery:

  • resistance training;
  • repeated sprints;
  • explosive efforts;
  • sports involving repeated bursts of high power.

That is exactly where the phosphocreatine system is most relevant.

Lean mass—if there is a training stimulus

Creatine can increase water associated with muscle fairly quickly. Over longer resistance-training interventions, it can also help produce greater lean-mass gains. See the 2024 body-composition meta-analysis.

Both are real.

Two popular summaries are both too simple: “Creatine gains are just water” and “every kilogram of extra lean mass is pure new muscle.” The early and long-term changes are not the same thing.

What creatine is less impressive at

A useful creatine guide should also tell you where enthusiasm needs cooling.

Long-duration endurance

Creatine is particularly good at supporting intense, repeatable muscular work. It has not shown the same clear advantage for prolonged endurance performance.

A systematic review and meta-analysis in trained participants found no meaningful overall endurance-performance benefit from creatine monohydrate.

A 2026 scoping review of endurance and mixed-sport research adds a useful distinction. The more favourable signals tended to appear in selected contexts involving repeated high-intensity efforts, sprint finishes and power-endurance demands, while aerobic outcomes remained limited or inconsistent.

That is why “creatine for runners” is not a yes-or-no question. A distance athlete who also strength trains, attacks hills, performs repeated hard surges or relies on a finishing sprint has different demands from someone concerned only with prolonged steady-state endurance. Creatine is not a proven general endurance booster; its physiological fit is stronger when the event temporarily becomes intense.

The same female runner appears twice on a mountain road, first at a steady endurance pace and later accelerating hard; the graphic reports no significant pooled endurance benefit across 13 controlled studies but more favorable signals in short high-intensity efforts.
Being a “runner” does not answer whether creatine fits your goals. A runner who also strength trains, performs repeated sprints or relies on explosive race moments has a different performance profile from someone focused almost entirely on prolonged steady endurance. The decision should follow the demands of the sport—not the label attached to the athlete.

Direct fat loss

Creatine is not a fat burner.

Resistance-training studies sometimes show favourable body-composition changes when creatine is added, but that should not be rewritten as “creatine melts fat.” Diet, energy intake, daily activity and training remain the important variables if fat loss is the goal.

Soreness and recovery

Recovery research is much less consistent than the strength literature.

One systematic review found no meaningful improvements in soreness, muscle-strength recovery, inflammation or range of motion after muscle-damaging exercise, although creatine kinase was reduced at one time point. Other meta-analytic work has found potentially favourable changes in some muscle-damage markers but substantial heterogeneity.

Creatine may eventually prove useful for particular recovery outcomes. It is not something I would buy primarily because I want tomorrow’s leg-day soreness to disappear.

↑ Back to guide

The scale went up. Did creatine make you fat?

You start creatine on Monday.

By the weekend, the scale is 800 grams higher.

If you are trying to lose fat, that can be unsettling.

But the scale cannot tell you whether that change came from body fat, muscle tissue, glycogen, water, food and fluid still in the digestive system, or several of these together.

Creatine increases muscle creatine storage, and water accompanies that process. An early increase in body mass can therefore happen far faster than you could plausibly build the same amount of new muscle tissue.

It is also not the same as gaining 800 grams of fat.

Scale-to-body-composition graphic showing body weight separating into lean mass and fat mass, then magnifying lean mass into muscle tissue and associated water to explain why creatine-related weight gain does not reveal exactly what changed.
If body weight is one of your progress markers, note when you start creatine before interpreting a sudden change. The supplement can make the scale noisier before anything meaningful has happened to body fat, so one unexpectedly high week should not automatically trigger changes to an otherwise sensible nutrition or training plan.

Water, lean mass and muscle are different things

What you noticeWhat may be happening
Scale rises relatively quicklyIncreased water can contribute
Muscles look somewhat fullerMore intramuscular water may contribute
A scan reports more lean massLean mass includes water and other non-fat tissues
Strength and lean mass increase over monthsTraining adaptations and creatine can both contribute
Body fatCreatine does not simply turn into fat
What an early change in scale weight or “lean mass” can—and cannot—tell you.

The opposite mistake happens too. If a scan reports an extra kilogram of “lean mass,” that should not automatically be described as a kilogram of newly built muscle fibre.

If the water part is what worries you, that is a separate question from scale weight: see creatine, hydration and cramps.

Creatine and the brain: interesting science, incomplete answers

There is real biology behind the brain question.

The brain has enormous energy demands and uses a creatine-phosphocreatine system too. Supplementation can increase brain creatine, though the response appears more complicated than loading skeletal muscle. 2024 systematic review

Where things become difficult is translating that mechanism into noticeable cognitive outcomes.

A 2024 meta-analysis of 16 randomized trials involving 492 adults found improvements in memory, some measures of attention time, and processing speed. It did not find significant improvements in overall cognition or executive function, and confidence in the findings differed by outcome.

Another systematic review reached a more cautious conclusion, describing the cognitive findings as equivocal despite evidence that creatine can increase brain creatine. Read the review.

That disagreement is exactly why brain claims deserve more restraint than muscle claims.

A neutral brain model above a developing evidence sheet, with the strongest print for memory, a lighter low-certainty signal for attention and processing speed, and no significant pooled improvement shown for overall cognition or executive function.
A useful way to read any claim about creatine and the brain is to ask which cognitive ability actually improved. Better performance on a memory test does not automatically mean better concentration at work, greater productivity, higher intelligence or a noticeable everyday “brain boost.” Those are different claims requiring their own evidence.

What about sleep deprivation?

Creatine is particularly interesting when the brain is under unusually high energetic stress, including sleep deprivation.

Positive findings in those conditions deserve investigation. They do not mean creatine can substitute for sleep or that an experimental high-dose protocol should automatically become a normal “brain dose.”

Bottom line: memory has the most encouraging signal so far. Claims about universal focus, productivity, broad cognitive enhancement or prevention of neurodegenerative disease go beyond the current evidence.

The brain research is real. The marketing version is simply moving faster.

Creatine for women: the evidence is better than the old stereotype—and narrower than the new hype

Creatine spent years wrapped in male bodybuilding culture.

Now the pendulum is swinging hard in the other direction, with creatine sold to women for hormones, mood, menopause, muscle and cognition all at once.

The interesting evidence is narrower—and more useful—than that marketing bundle.

Women who train

Women use the same phosphocreatine energy system and can increase tissue creatine through supplementation. Female-specific research, however, is smaller than the overall creatine literature. We should not turn “women can benefit” into “women always respond better.”

After menopause

This is one area where newer research genuinely strengthens the case.

A 2026 systematic review and meta-analysis included seven randomized trials and 608 postmenopausal women overall. Five lean-mass comparisons involving 338 participants favoured creatine by about 0.37 kg, while three studies involving 111 participants contributed to the leg-press analysis, which favoured creatine by roughly 7.5 kg.

The clearest benefits appeared when at least 5 g/day was paired with resistance training. Overall bone density did not significantly improve. Most studies carried at least some risk-of-bias concerns, so the findings are encouraging rather than permission to attach every menopause claim imaginable to creatine.

That is a much stronger reason for interest than vague promises of “hormonal support.”

Postmenopause creatine graphic with a female muscle-and-bone model under resistance-training tension, summarizing seven randomized trials: average leg-press strength improved by 7.5 kg, lean mass by 0.37 kg, while bone density showed no significant overall change.
If the main reason for considering creatine after menopause is bone density, the current trials do not offer the same support they do for strength and lean mass. In practice, the evidence points toward creatine as a potential addition to resistance training—not as a stand-alone treatment for the many changes grouped under “menopause.”

Creatine as you get older

The resistance-training partnership also matters in older adults.

A 2025 systematic review and meta-analysis found that creatine added to resistance training improved lower-body strength and lean tissue mass compared with resistance training plus placebo in older adults.

That makes creatine an interesting adjunct when preserving strength and function matters increasingly with age.

No scoop, however, reproduces what progressive strength training asks your muscles, bones and nervous system to do.

Vegetarians and vegans may start from a different baseline

Dietary creatine comes mainly from animal foods.

People eating little or no meat may therefore begin with lower creatine stores, leaving more room for those stores to rise after supplementation. A systematic review of vegetarian and omnivorous athletes found that tissue creatine often increased more in vegetarian participants, while studies were mixed on whether their exercise-performance gains were greater than those of omnivores.

That does not guarantee that every vegetarian or vegan will gain more strength, muscle or cognitive benefit than every omnivore.

Lower baseline stores help explain why biological responses can differ. They do not guarantee a particular visible result.

↑ Back to guide

Is creatine safe?

For healthy adults taking commonly studied doses, creatine has an unusually large safety literature for a sports supplement.

A 2025 safety analysis covering 685 human creatine trials compared reported side effects across 12,839 creatine participants and 13,452 placebo participants. Overall participant-level side-effect reporting was 4.60% with creatine and 4.21% with placebo, a difference that was not statistically significant.

A separate 2026 study-level analysis across 684 randomized trials asked a different question: whether adverse effects showed a meaningful pattern as creatine dose or duration increased. Reported effects were generally infrequent and mild, and the analysis did not identify a consistent clinically meaningful dose- or duration-response pattern versus placebo.

That combination is reassuring: symptoms occur in both supplement and placebo groups, and the broad randomized-trial literature does not show the escalating safety pattern often implied online. It is still not evidence that every possible person in every medical situation should take creatine without thought.

An athletic woman sits in a gym holding a creatine drink beside loose creatine powder; callouts describe possible water-weight gain and GI upset, while a 685-trial comparison shows side-effect reporting of 4.60% with creatine and 4.21% with placebo, with no significant overall difference.
The placebo comparison matters because symptoms can appear during a trial even when creatine is not the cause. Therefore, a headache, stomach complaint or other symptom beginning after a new supplement deserves attention—but timing alone cannot establish causation. That distinction is useful well beyond creatine when evaluating supplement side-effect stories.

For a symptom-by-symptom discussion of gastrointestinal complaints, water retention and other reported effects, see our dedicated guide to creatine side effects.

Creatine, creatinine and your kidneys

Imagine you have been taking creatine for several months.

You get routine blood work.

Your creatinine comes back higher.

After years of hearing that creatine “damages kidneys,” connecting those dots would be easy.

The test itself makes the story more complicated.

Creatine and creatinine are related, but not interchangeable

Creatine is the compound being supplemented.

Creatinine is a breakdown product.

Serum creatinine is also commonly used to estimate kidney filtration.

If creatine supplementation changes creatinine production or metabolism, a kidney estimate that relies on creatinine can move even when actual filtration has not deteriorated in the same way.

Two 2026 analyses help show why the blood test can look worse even when kidney filtration has not necessarily become worse.

One meta-analysis of randomized trials found that supplementation increased serum creatinine by an average of about 0.13 mg/dL but did not find significant differences in urea or estimated GFR overall.

A second 2026 kidney-health meta-analysis went a step further. Across 26 studies, serum creatinine increased and creatinine-based GFR estimates decreased. But when filtration was assessed using Cr-EDTA, there was no statistically significant difference between creatine and control groups. Other kidney markers including albuminuria and proteinuria were also not significantly different.

The practical lesson: a creatinine-based estimate can be affected by something that changes creatinine metabolism. A higher result deserves clinical interpretation, but it is not automatic proof that creatine injured the kidneys.

Editorial kidney-test graphic separating creatine use, serum creatinine and kidney filtration, explaining that creatine can affect creatinine-based kidney estimates even when directly measured filtration does not show the same impairment.
There is an important measurement lesson here: when a supplement can change the marker used in an equation, the estimated result can move partly because the marker moved. That is why the directly measured filtration findings matter—they help separate a change in creatinine from evidence that kidney filtration itself deteriorated in the same way.

So should you ignore a high creatinine result?

No.

A changed laboratory result deserves appropriate interpretation. Tell the clinician reviewing your blood work that you take creatine. They can consider supplementation alongside your medical history, other laboratory markers and—when clinically appropriate—measures that are less dependent on creatinine.

The point is not to self-diagnose yourself as healthy. It is also not to diagnose yourself with creatine-induced kidney damage from a single number.

What if you already have kidney disease?

That is a different situation from a healthy adult taking a sports supplement.

Research in people with kidney disease is much more limited, and Mayo Clinic recommends that people with kidney disease discuss creatine with their healthcare team.

Does creatine cause hair loss?

This rumour survived because there was just enough science underneath it to sound convincing.

Where the worry came from

A small 2009 study in rugby players reported changes in dihydrotestosterone (DHT) during creatine supplementation.

DHT is relevant to androgenetic hair loss in genetically susceptible people.

A plausible concern therefore emerged:

creatine → higher DHT → hair loss.

One important detail disappeared as the story travelled around gyms and the internet.

The study did not measure hair loss.

Then researchers measured the hair

In 2025, researchers conducted a randomized controlled trial specifically examining creatine and hair-follicle health.

Forty-five resistance-trained men aged 18–40 were assigned to 5 g/day of creatine monohydrate or placebo for 12 weeks.

Researchers measured total testosterone, free testosterone, DHT, hair density, follicular-unit count and cumulative hair thickness.

They found no significant differences in DHT or measured hair outcomes between creatine and placebo. Read the randomized trial.

That is much more direct evidence than the creatine-hair debate had previously.

It is also one 12-week trial in young resistance-trained men. It cannot answer every possible lifetime question about every population.

But we can no longer accurately say that nobody has directly tested creatine and hair loss. They have. In that first direct randomized trial, the results did not support the claim.

Creatine hair-loss evidence timeline comparing the 2009 study that reported a DHT increase with a 2025 randomized trial that directly measured hair density, follicular units and hair thickness and found no significant difference between creatine and placebo.
This creatine–hair-loss story illustrates a broader evidence rule: changing a hormone associated with an outcome is not the same as measuring the outcome itself. A 2009 DHT finding raised a reasonable question; years later, researchers finally tested hair density and follicular measures directly. Surrogate signals and real-world outcomes should not be treated as interchangeable.

“But I started creatine and saw more hair in the shower”

That can be genuinely unnerving.

The difficult question is not whether you saw more hair. The difficult question is whether creatine caused it.

Hair shedding can change with genetics, age, illness, stress, calorie restriction, nutritional problems, medications and ordinary variation. When a new supplement and a new symptom appear close together, connecting them is natural.

Anecdotes are useful for spotting questions worth studying. Controlled trials are what help us test causation.

Does creatine dehydrate you?

Creatine increases water associated with muscle.

That fact somehow became a rule that creatine users must spend all day chasing a giant water target.

You do not need a special four- or five-litre creatine quota.

Hydration needs vary with body size, climate, sweat rate, exercise volume, diet, health and individual physiology.

If you are training outside in hot, humid weather, your fluid and electrolyte needs may be substantial because you are losing more fluid through sweat.

Creatine itself does not create an arbitrary universal number everyone must drink. Controlled evidence has not supported the old claim that recommended creatine use inherently causes dehydration or muscle cramping; a 2025 safety review found no significant adverse effect on hydration or thermoregulation in the controlled literature it assessed.

Hydrate according to your actual circumstances rather than a creatine-specific internet ritual.

A muscle specimen suspended in a clear fluid chamber under controlled heat illustrates that early water retention is not the same as dehydration; text notes that hydration and thermoregulation were not worsened, cramps were not shown to increase, and no universal creatine-specific water intake exists.
The same daily creatine dose can accompany completely different hydration needs. An air-conditioned rest day and a long outdoor session in hot, humid weather may require very different amounts of fluid and electrolytes—not because the creatine changed, but because sweat loss, exercise and environment did.

If creatine bothers your stomach

Gastrointestinal discomfort is one of the more plausible practical complaints, particularly when somebody suddenly tries to consume a large loading dose.

Before spending more money on an exotic creatine form, simplify.

  • skip loading;
  • keep each dose smaller;
  • split loading doses through the day;
  • take creatine with food if that feels better;
  • check whether your supplement contains sweeteners, stimulants or other ingredients that may be responsible.

The traditional loading protocol itself divides approximately 20 g across four doses rather than taking it all at once. NIH dosing guidance.

For many people, the stomach-friendly solution is simply 3–5 g/day without loading.

↑ Back to guide

How to take creatine without overthinking it

This can be a remarkably simple supplement.

SituationPractical approach
You want the simplest routine3–5 g creatine monohydrate daily
You want faster saturation~20 g/day split into 4 doses for 5–7 days, then 3–5 g/day
Loading upsets your stomachSkip it
It’s a rest dayTake your normal daily amount
You forgot yesterdayResume your normal dose today
You stop using creatineNo taper is required
A practical creatine dosing cheat sheet for everyday use.

Both loading and gradual daily dosing are well-established research approaches. NIH Office of Dietary Supplements

A continuous creatine-powder trail explains a simple daily routine: 3–5 g creatine monohydrate every day, the same approach on workout and rest days, optional loading, no proven perfect timing window, and no established need to cycle.
The easiest way to make creatine effective may be to make it boring. Attach the daily dose to a routine you already remember rather than building an elaborate supplement schedule around the clock. Consistency is easier to maintain when creatine becomes ordinary, not another task that requires perfect workout timing.

Is 3 grams enough?

For many people, yes.

The NIH describes non-loading research protocols around 3–6 g/day, including weight-adjusted approaches of roughly 0.03–0.1 g/kg/day, used over several weeks. See the dosing overview.

That does not mean the average recreational user needs a calculator. A consistent 3–5 g/day is much easier to follow than turning a simple supplement into body-weight mathematics.

Five grams is convenient. It is not a magical biological threshold.

Do you need to load?

No.

Loading mostly answers: How quickly do I want my muscle creatine stores to rise?

It does not answer: Will creatine eventually work if I don’t load it?

If you have a competition or a specific short timeline, reaching saturation quickly may matter. For a long-term gym routine, a slower daily approach is perfectly reasonable.

A skeletal-muscle visual compares creatine loading with no loading: 20 g/day split into four 5 g doses reaches elevated muscle creatine stores in about 5–7 days, while 3–5 g/day reaches a similar rise more gradually over about 3–4 weeks.
The real trade-off with a creatine loading phase is convenience. Faster saturation requires several larger doses across the day and can be harder on some stomachs; meanwhile, gradual daily dosing asks for more patience but less complexity. If reaching high stores quickly solves no real problem for you, speed itself may offer little practical value.

Before or after your workout?

For most users, the available timing literature does not support chasing a precise pre- versus post-workout window. Methodological limitations still prevent a firm recommendation for one ideal strategy. Review of creatine timing around exercise.

A 2026 randomized crossover pilot in 11 physically active men reported better acute lifting performance when creatine was consumed before exercise rather than during or after it. Interesting? Certainly. Enough to establish a new universal dosing rule? No—the authors themselves describe the findings as exploratory and in need of confirmation in larger studies.

Regular intake remains the more useful priority.

Morning works. Lunch works. After training works.

Choose a routine you will remember.

What about rest days?

Take your normal dose.

Creatine works through elevated tissue stores. Your muscles do not reset because today happens to be a rest day.

You forgot yesterday

Resume your normal amount.

There is no need to double today’s scoop or restart loading. One missed day does not erase weeks of accumulated muscle creatine.

Do you need to cycle creatine?

Routine creatine cycling has no established evidence-based requirement.

Gym culture borrowed “cycling” language from substances where cycling has entirely different biological reasons. Creatine is not an anabolic steroid.

What happens when you stop?

Muscle creatine stores gradually move toward baseline.

Some water-associated body weight may fall.

You do not need to taper, and there is no recognised creatine withdrawal syndrome.

Muscle that you genuinely built through months of training does not suddenly vanish because the supplement left your shaker.

Can you take creatine with coffee?

For ordinary coffee drinkers taking normal creatine doses, the evidence does not justify a blanket rule that caffeine and creatine must always be separated.

The reason the internet argument sounds contradictory is that the small research base has tested different ways of combining them. Two systematic reviews each identified only about ten relevant studies. One review found that acute caffeine taken after a creatine-loading phase generally did not erase caffeine’s ergogenic effect, whereas chronic caffeine consumed throughout loading produced mixed results: some studies suggested interference, several found no interaction and one reported synergy.

A second systematic review similarly found that acute caffeine after loading produced an additional ergogenic effect over creatine alone in three of five studies, while daily caffeine during loading produced an additive benefit in only one of five studies.

That is not enough evidence to invent a mandatory two-, four- or six-hour separation rule. Your morning coffee does not automatically cancel your creatine, but chronic high-caffeine use during a loading phase is less settled. If combining large doses makes your stomach miserable, separating or simplifying them is sensible.

The same athletic woman appears repeatedly mixing daily creatine and once drinking coffee before training, contrasting creatine as a daily strategy with caffeine as an acute stimulant; the graphic labels acute post-loading caffeine as generally compatible, chronic use during loading as mixed, and states that no universal separation rule exists.
When you see the claim that “caffeine blocks creatine,” ask how caffeine was actually used. Acute caffeine after a creatine-loading period and chronic high-caffeine intake during loading are different research situations, and they have not produced identical results. That distinction is more useful than inventing a universal coffee-versus-creatine rule.

Which type of creatine should you buy?

This is the easiest part.

Creatine monohydrate.

It has the deepest evidence base, a long history of use and usually the lowest price.

A systematic review examining alternative creatine forms found very few direct comparisons with monohydrate and no consistent evidence that newer forms outperform it.

FormWhat to know
Creatine monohydrateBest-studied default
Micronized creatine monohydrateSame form, smaller particles; may mix more easily
Creatine HClMarketed with advantages that have not convincingly beaten monohydrate in evidence
Buffered creatineNo established practical superiority over monohydrate
How common creatine forms compare with the monohydrate evidence base.

The NIH likewise notes that more expensive alternatives have not been proven superior for increasing muscle creatine, digestibility, stability or safety.

Laboratory-style comparison of creatine monohydrate, micronized monohydrate, creatine HCl and buffered creatine, showing micronized as finer-particle monohydrate, HCl as more soluble without proven better outcomes, and monohydrate as the most established reference form.
Once you have chosen creatine monohydrate, product quality matters more than increasingly exotic formulation language. For athletes subject to drug testing, independent sport certification may be especially valuable because contamination with prohibited substances is a different problem from whether creatine itself is effective.

“Micronized” is not a different type of creatine

Despite the label, micronized creatine is still creatine monohydrate.

The term simply means the powder has been processed into smaller particles, which may help it disperse more easily in liquid without changing the underlying form of creatine.

Product quality matters more than impressive wording

Choose a reputable manufacturer.

If you compete in tested sport, independent sport certification may be particularly valuable because contamination with prohibited substances is a separate issue from whether creatine itself works.

You do not need a proprietary “ultra-anabolic matrix.” You need the product to contain what the label says it contains.

Who should be more cautious?

Healthy-adult evidence cannot automatically be transplanted into every population.

Known kidney disease

Discuss creatine with the healthcare team managing your kidney health rather than extrapolating from healthy-adult trials. Mayo Clinic creatine guidance.

Pregnancy and breastfeeding

Creatine is being investigated in maternal and fetal physiology, but routine supplementation during pregnancy and breastfeeding does not have the depth of human safety evidence available for adult sports supplementation. A recent safety review notes that evidence remains lacking in pregnancy, while the NIH LactMed creatine monograph reports that human milk levels after supplementation have not been studied and advises avoiding supplementation unless prescribed until more data are available.

Individual clinical advice is more appropriate here than extrapolating from gym studies.

Adolescents

It is no longer accurate to say that creatine has never been studied in teenagers.

A 2026 systematic review found five eligible studies and reported no consistent short-term kidney, liver or cardiometabolic safety signals during the study periods. It also emphasized how limited the evidence remains and the need for larger studies with longer follow-up.

So the evidence is not zero. It is also nowhere near as deep as the adult literature.

Medical conditions and medications

If you are managing a medical condition or take medication that affects kidney function, fluid balance or another relevant system, disclose supplement use to your healthcare professional.

“Available without a prescription” does not mean “irrelevant to medical care.”

↑ Back to guide

Frequently asked creatine questions

Everyday use and common questions

Can I mix creatine with whey protein?

Yes. Protein and creatine do different jobs, and there is no reason they have to live in separate drinks. If putting both in the same shake helps you remember your creatine, that is a perfectly good routine. For broader nutrition context, our guide to what protein does explains the role of dietary protein in more detail.

Can I take creatine on an empty stomach?

Yes, if you tolerate it. When your stomach dislikes it, take creatine with food. There is no benefit to making a simple supplement uncomfortable.

Is creatine a steroid?

No. Creatine is not an anabolic steroid. It is a compound your body naturally makes and uses in the creatine–phosphocreatine energy system; supplementation increases creatine availability rather than working through the hormonal mechanisms that define anabolic steroids.

Training, sport and long-term use

What if I take creatine but don’t work out?

Your tissue creatine stores can still increase. But many of the outcomes people want—more strength, more muscle and better training performance—depend on actually creating a training stimulus. The scoop cannot perform the repetitions for you. See the strength evidence for the training context.

Can runners take creatine?

Yes. The better question is whether it suits the runner’s goals. Someone who strength trains, sprints or performs repeated high-intensity intervals may have more reason to use creatine than someone concerned only with long-duration endurance. The dedicated endurance meta-analysis found no significant overall performance benefit in trained populations; see the full creatine-for-runners and endurance discussion.

How long can you take creatine?

There is no evidence-based rule telling healthy adults that creatine must be stopped after an arbitrary number of weeks. Mayo Clinic currently describes recommended oral doses as likely safe for many people for up to five years. That reflects the duration supported by available longer-term evidence; it does not mean creatine suddenly becomes unsafe on the first day of year six.

The 2026 analysis of 684 randomized trials also found no consistent pattern of clinically meaningful adverse effects increasing with dose or duration at the study level. Science cannot give us lifetime data on every possible user, but the available evidence does not support the familiar rule that healthy adults must routinely cycle off because continuous creatine inevitably becomes dangerous. For the broader context, see the creatine safety section.

So, is creatine worth taking?

Creatine has travelled through two opposite reputations.

First it was the suspicious bodybuilding powder supposedly responsible for cramps, kidney damage and baldness.

Now it is in danger of becoming a universal wellness supplement for muscle, menopause, memory, mood, longevity and brain optimisation.

Neither version fits the evidence particularly well.

Creatine is excellent at a fairly specific job. It supports the body’s rapid-energy system, and that translates into strong evidence for repeated high-intensity performance, greater strength gains and modestly greater lean-mass gains alongside resistance training.

The newer possibilities—in cognition, aging and postmenopausal women—deserve curiosity without being promoted to certainty before the evidence gets there.

And ordinary creatine use is much less complicated than supplement culture has made it.

For a healthy adult who decides it fits their goals:

Use creatine monohydrate.

Take around 3–5 grams each day.

Be consistent.

Then put considerably more thought into your training, food and sleep than into the timing of the scoop.

Key research used for this September 2026 update

How this guide was researched: priority was given to systematic reviews, meta-analyses, randomized controlled trials and major evidence-based clinical or sports-nutrition resources. Community questions were useful for identifying what readers are confused or worried about, but anecdotes were not treated as proof of benefit or harm. Where individual studies carried important limitations, we also considered sample size, study duration, risk of bias and relevant author disclosures when deciding how strongly to describe a finding.

Core performance, kidney and safety evidence

  1. NIH Office of Dietary Supplements. Dietary Supplements for Exercise and Athletic Performance: Health Professional Fact Sheet. Dosing, loading, forms, safety context and high-intensity exercise guidance.
  2. Desai I, et al. (2024). The Effect of Creatine Supplementation on Resistance Training-Based Changes to Body Composition: A Systematic Review and Meta-analysis. Journal of Strength and Conditioning Research.
  3. Kazeminasab F, et al. (2025). The Effects of Creatine Supplementation on Upper- and Lower-Body Strength and Power: A Systematic Review and Meta-Analysis. Nutrients.
  4. Tsiaras A, et al. (2026). The effect of creatine supplementation on kidney function: a systematic review and meta-analysis of randomized controlled trials. Journal of Renal Nutrition.
  5. de Souza Almeida A, et al. (2026). Impact of creatine supplementation on kidney health: a systematic review and meta-analysis. International Urology and Nephrology.
  6. Lak M, et al. (2025). Does creatine cause hair loss? A 12-week randomized controlled trial. Journal of the International Society of Sports Nutrition.
  7. Kreider RB, et al. (2025). Safety of creatine supplementation: analysis of the prevalence of reported side effects in clinical trials and adverse event reports. Journal of the International Society of Sports Nutrition.
  8. Gonzalez DE, et al. (2026). Creatine Supplementation Dose and Duration Are Not Associated with Increased Side Effects: A Structured Review and Study-Level Dose-Response Analysis of Randomized Controlled Trials. Sports.

Cognition, special populations and performance contexts

  1. Naddafha S, et al. (2026). Creatine monohydrate for lean mass, strength, and bone density in postmenopausal women: a systematic review and meta-analysis. Journal of the International Society of Sports Nutrition.
  2. Xu C, et al. (2024). The effects of creatine supplementation on cognitive function in adults: a systematic review and meta-analysis. Frontiers in Nutrition.
  3. McMorris T, et al. (2024). Creatine supplementation research fails to support the theoretical basis for an effect on cognition: Evidence from a systematic review. Behavioural Brain Research.
  4. Liu S, et al. (2025). The impact of creatine supplementation associated with resistance training on muscular strength and lean tissue mass in the aged: a systematic review and meta-analysis. European Review of Aging and Physical Activity.
  5. Fernández-Landa J, et al. (2023). Effects of Creatine Monohydrate on Endurance Performance in a Trained Population: A Systematic Review and Meta-analysis. Sports Medicine.
  6. Wesołowski I, et al. (2026). Creatine Supplementation in Endurance and Mixed-Sport Contexts: A Scoping Review of Performance, Recovery, and Body Composition. Nutrients.
  7. Northeast B, Clifford T. (2021). The Effect of Creatine Supplementation on Markers of Exercise-Induced Muscle Damage: A Systematic Review and Meta-Analysis of Human Intervention Trials. International Journal of Sport Nutrition and Exercise Metabolism.
  8. Ribeiro F, et al. (2021). Timing of Creatine Supplementation around Exercise: A Real Concern? Nutrients.
  9. Ben Maaoui K, et al. (2026). Acute Creatine Ingestion Before Resistance Training Enhances Strength Performance More than Ingestion During or After Training: A Randomized Crossover Pilot Trial. Nutrients.
  10. Kaviani M, Shaw K, Chilibeck PD. (2020). Benefits of Creatine Supplementation for Vegetarians Compared to Omnivorous Athletes: A Systematic Review. International Journal of Environmental Research and Public Health.

Forms, caffeine and clinical guidance

  1. Longobardi I, et al. (2025). A short review of the most common safety concerns regarding creatine ingestion. Frontiers in Nutrition.
  2. Fazio C, et al. (2022). Efficacy of Alternative Forms of Creatine Supplementation on Improving Performance and Body Composition in Healthy Subjects: A Systematic Review. Journal of Strength and Conditioning Research.
  3. Elosegui S, et al. (2022). Interaction Between Caffeine and Creatine When Used as Concurrent Ergogenic Supplements: A Systematic Review. International Journal of Sport Nutrition and Exercise Metabolism.
  4. Marinho AH, et al. (2023). Effects of creatine and caffeine ingestion in combination on exercise performance: A systematic review. Critical Reviews in Food Science and Nutrition.
  5. Rubinchuk A, et al. (2026). Evaluating the Safety of Creatine Monohydrate in Adolescents: A Systematic Review of Renal, Hepatic, and Cardiometabolic Outcomes. Cureus.
  6. Drugs and Lactation Database (LactMed): Creatine. National Library of Medicine; revised July 15, 2025.
  7. Mayo Clinic — Creatine. Clinical overview of uses, safety, kidney caution and longer-term use.

↑ Back to top