Posted on — 5 Comments

Side Effects of Mounjaro (Tirzepatide): What’s Common, What’s Serious & How to Handle Them

SIDE EFFECTS OF MOUNJARO (TIRZEPATIDE): What's Common, What's Serious & How to Handle Them

If you’re researching Mounjaro side effects, you’re not alone. Right from the first dose, most people want clear, compassionate guidance: what typically happens, how long it lasts, and—crucially—how to make side effects easier to live with. Because searches also show a lot of concern about Mounjaro body aches, Mounjaro muscle pain, Mounjaro joint pain, and leg cramps on Mounjaro, this guide goes beyond the gastrointestinal (GI) issues that dominated the trials and addresses what real people feel day to day. For orientation on frequency, timing, and red flags, the definitive summary remains the Mounjaro prescribing information (May 2025); meanwhile, large clinical programs such as the SURMOUNT-1 trial (NEJM) and the SURPASS-2 trial (NEJM) consistently show GI effects lead early and usually settle with time.

Plain-Language Reminder (Not Medical Advice): Bodies differ. If a symptom feels severe, persistent, or simply “not you,” talk with your clinician rather than trying to tough it out. Informational only—this article is educational, not medical advice. Decisions about starting, stopping, or adjusting medication should be made with your own clinician.


Common Mounjaro Side Effects (GI) — Why They Happen, When They Peak, and What Actually Helps

Why this happens. Tirzepatide slows gastric emptying and shifts gut-hormone signaling. Consequently, larger or fattier meals can “sit heavy,” nausea tends to cluster around initiation and step-ups, bowel habits may swing toward diarrhea or constipation, and reflux/burping can show up after late dinners. Fortunately, the gut adapts; with simple meal structure changes, hydration, and thoughtful dose pacing, most people feel steadily better. For frequencies and timing, see the Mounjaro prescribing information (May 2025) and the SURMOUNT-1 trial (NEJM).

Nausea On Mounjaro (Most Common GI Side Effect)

What’s going on. Slower stomach emptying + dose increases.
Today’s fixes.

  • Smaller, earlier, lower-fat meals; slow the pace; skip “hero portions.”
  • Sit upright 30–60 minutes after eating; sip fluids between meals.
  • Gentle helpers: ginger tea/lozenges; cooler foods if aromas trigger queasiness.
    Call sooner if: Fluids won’t stay down, dizziness appears, or nausea lingers beyond a few days at a stable dose.

Vomiting On Mounjaro (Less Common—Prevent Dehydration First)

Immediate goal: Hydration. Tiny, frequent sips; on rough days use oral rehydration. For simple ratios and options, see our post on electrolytes for diarrhea: best natural drinks & remedies.
Food texture: Bland, low-fat, easy to digest (broth, yogurt, rice, crackers).
Training: Pause high-intensity workouts until rehydrated.
Red flags: Repeated vomiting, very low urine, faintness, or dark urine → call promptly.

Diarrhea On Mounjaro (Triggers And Fixes)

Replace losses early: Fluids + electrolytes at the first sign.
Shift the plate: Add soluble fiber (ripe bananas, applesauce, oats, psyllium) once cramps ease.
Trim common triggers: Greasy foods, alcohol, very spicy dishes, and sugar alcohols (sorbitol/xylitol) often worsen things—reduce them for now.

Constipation On Mounjaro (Slow Transit After Step-Ups)

Build the base: Water, fiber (vegetables, berries, oats, chia), and movement.
Bathroom routine: A short walk after meals plus a daily, unhurried “appointment.”
If needed: Ask about a gentle osmotic option.

Before you start a fiber supplement, read this practical take on Metamucil’s day-to-day side effects.

Heartburn, Reflux, And Burping (Dyspepsia)

Structure meals: Smaller portions, earlier dinners, and avoid lying down within 3 hours of eating.
Usual culprits: High-fat meals, chocolate, mint, citrus, caffeine.
At night: Slight head-of-bed elevation; left-side sleep can help.

Abdominal Pain Or Bloating (Ordinary Vs Concerning)

Start simple: Slow your eating speed; favor lower-fat meals; walk 10–15 minutes after eating.
However: Severe, persistent, or radiating pain—especially with vomiting or fever—warrants prompt evaluation to rule out gallbladder or pancreas issues (details in the prescribing information).

Educational note—this is not medical advice. GI symptoms can quietly drain fluids and minerals. Consequently, dehydration often ripples outward as leg cramps on Mounjaro and generalized “achey” days. Because that matters to readers, let’s go there next.


Mounjaro Body Aches, Mounjaro Muscle Pain, And Leg Cramps On Mounjaro — Why They Happen And How To Ease Them

Short answer. In the trials, musculoskeletal pain was not among the most frequent adverse events; GI symptoms dominated. Even so, some people report myalgia, generalized aches, cramps, or transient arthralgia in real life—especially around dose escalations. Very rarely, case reports describe rhabdomyolysis (severe muscle breakdown) shortly after starting or stepping up tirzepatide. For the official overview, consult the Mounjaro prescribing information (May 2025); for a rare but notable signal, see a 2025 rhabdomyolysis case report.

Why Mounjaro Muscle Pain And Body Aches Show Up For Some People

  1. Dehydration And Electrolyte Shifts
    Because nausea, vomiting, or diarrhea reduce fluid and minerals, dips in sodium or potassium can provoke cramps and soreness. Moreover, volume depletion strains the kidneys, which is one reason the label emphasizes hydration.
  2. Rapid Weight Loss, Posture Changes, And New Routines
    As weight drops, posture and gait adapt. Meanwhile, many people ramp up activity at the same time. Consequently, transient muscle soreness and joint “awareness” are common and usually settle with smart pacing.
  3. Very Rare Muscle Injury (Know The Red Flags)
    Severe pain, true weakness, or cola-colored urine after a dose change warrants same-day assessment to rule out rhabdomyolysis.

Leg Cramps On Mounjaro — Quick Wins That Work

  • Rehydrate, then replace electrolytes on GI-symptom days (don’t wait). For simple at-home options, see DIY natural electrolyte drinks for dehydration.
  • Ease into training for a week after each escalation; choose low-impact movement, light cycling, or walking.
  • Stretch in the evening; add a brief morning warm-up.
  • Call promptly if cramps are severe, frequent, or accompanied by dark urine or weakness.

Mounjaro Joint Pain — Typical Vs Not Typical

  • Typical: Fleeting stiffness or “joint awareness” while body mechanics shift. Hydration + gentle, regular movement (walking, swimming, cycling) usually helps.
  • Not typical: Hot, swollen joints, fever, or motion-limited pain—seek care rather than self-managing.

A One-Week Plan To Reduce Mounjaro Muscle Pain And Body Aches

  • Day 1–2 (after a step-up): front-load fluids; schedule short walks after meals; keep meals smaller and lower-fat; hold off on strenuous training.
  • Day 3–4: add a 10–15 minute mobility routine (hips, calves, thoracic spine); resume light cycling or brisk walking; maintain protein at each meal.
  • Day 5–7: trial a short, low-volume resistance circuit (2–3 sessions this week); if aches spike again, extend your time at the current dose before escalating.

Informational only—please individualize with your clinician.


Hair Loss On Mounjaro — 2025 Label Update, Why Shedding Happens, And What Genuinely Helps

Some people notice hair loss on Mounjaro, yet most shedding resembles telogen effluvium—a temporary, nonscarring shed triggered by rapid weight loss or nutrition gaps. In May 2025, “alopecia” was added to the label’s postmarketing section (reported after use; not proven common in trials). See the Mounjaro prescribing information (May 2025). For a straightforward primer on TE, a helpful overview is this dermatology review of telogen effluvium.

Why Telogen Effluvium Follows Rapid Weight Change

During calorie or protein deficits, the body prioritizes essentials over hair production. Consequently, more follicles enter the resting (telogen) phase, and diffuse shedding appears 2–3 months later. Reassuringly, TE is reversible once intake and weight stabilize, although it does take weeks to show improvement and months to reveal obvious regrowth.

Where Mounjaro Fits

Tirzepatide can suppress appetite and accelerate weight loss; meanwhile, early GI side effects may further dent intake. Put simply, short stretches of low protein and low micronutrients are enough to push susceptible follicles into telogen.

What Actually Helps (Practical, Doable Steps)

  • Stabilize Intake Before Dose Jumps. If appetite is poor or GI symptoms flare, pause escalation or extend your time at the current dose until eating normalizes.
  • Keep Protein Steady. A pragmatic starting range during active weight loss is ~1.2–1.6 g/kg/day (individualized with your clinician), spread across meals to protect lean mass and hair. (See our post on how to eat 100 grams of protein a day if you need a plan).
  • Check The Usual Nutrients. Ask about ferritin/iron, zinc, and vitamin D if shedding is significant or prolonged; correct deficits with guidance.
  • Avoid Extreme Deficits. On low-appetite days, rely on easy, higher-protein, lower-fat options (Greek yogurt, eggs, tofu, cottage cheese, smoothies). Meanwhile, stay ahead of dehydration.
  • Give It Time. Expect 6–12 weeks for shedding to calm and several months for visible regrowth. Reduce heat styling and tight hairstyles while new growth returns.

Educational note—this is not medical advice. Patchy loss, scalp inflammation, or prolonged heavy shedding deserves a medical work-up.


Mounjaro Vision Changes — Blurry Vision, Diabetic Retinopathy, And Keeping An Eye On Emerging Data

Most people will not develop vision problems on tirzepatide. However, if you already have diabetic retinopathy, rapid glucose improvement can temporarily worsen retinopathy or cause transient blur; therefore, extra monitoring is sensible. This precaution is described in the Mounjaro prescribing information (May 2025). Separately, an observational cohort in 2025 reported a class-level association between GLP-1 medicines and neovascular age-related macular degeneration (nAMD); although absolute risk was small and causality is unproven, it’s a timely reminder to keep routine eye checks (see the JAMA Ophthalmology 2025 cohort).

Why Vision Can Shift When Glucose Improves Rapidly

As sugars normalize, the lens and retina adjust; transient blur or short-term retinopathy changes can appear, then stabilize. Notably, this is not unique to tirzepatide; it can occur with any rapid glycemic improvement.

Practical Steps That Protect Your Eyes

  • Book An Eye Exam if you have a history of retinopathy or if new blur appears; bring recent glucose logs so your eye doctor can see your rate of change.
  • Aim For Steadier Glucose via regular meals, dose pacing, sleep, and gentle movement—fewer spikes and dips often mean fewer visual swings.
  • Do Not Stop Abruptly on your own; call your clinician if vision symptoms appear.

Vision Red Flags—Call Urgently

  • Sudden vision loss or a dark “curtain.”
  • Flashes or a shower of new floaters.
  • Eye pain, severe headache, or nausea with visual changes.

Information only—urgent changes deserve urgent care.


Mounjaro Dosing And Timeline — When Side Effects Tend To Show Up And How To Smooth The Ride

Most Mounjaro side effects cluster at initiation and each dose increase. Because the body adapts, your biggest lever is dose pacing plus a few supportive habits. For official dosing language, see the Mounjaro prescribing information (May 2025). For peri-procedural considerations (aspiration risk with anesthesia/deep sedation), a concise summary is available from The Medical Letter peri-procedural guidance (2024).

Standard Step-Ups (And Why Slower Often Feels Better)

Many people follow 4-week steps: 2.5 → 5 → 7.5 → 10 → 12.5 → 15 mg. However, if you reliably hit a rough patch at each increase, you can ask to stay longer at a tolerable dose or stretch a step to 6–8 weeks. Consequently, the “shock” to gastric emptying and appetite signals is smaller, and rescue meds are often unnecessary.

What To Expect By Week (Common, Not Universal)

  • Week 1–2 At A New Dose: Nausea peaks; stools may swing; appetite dips most here.
  • Week 3–4: Symptoms usually fade; energy stabilizes; workouts resume.
  • Within 48–72 Hours Of An Injection: Many people feel a mini-wave of queasiness/fullness on “shot day” and the next day; earlier dinners and smaller portions help.

“Shot-Day” Playbook (Copy And Use)

  • Night Before: Earlier, lighter dinner.
  • Dose Day: Smaller, more frequent meals; avoid very high-fat feasts; keep fluids handy.
  • Walk After Meals: 10–15 minutes reduces fullness and burping.
  • If Appetite Tanks: Rely on easy proteins (yogurt, eggs, tofu, cottage cheese, smoothies).
  • Training: Delay high-intensity sessions 48–72 hours if you’re routinely queasy after injections.

Travel, Big Events, And Procedures

  • Travel Week: Hold at your current dose rather than escalating right before a flight.
  • Big Events: Coordinate injection timing (with your prescriber) so the queasiest window doesn’t land on your most important day.
  • Anesthesia & Endoscopy: GLP-1s delay gastric emptying; instead of stopping on your own, coordinate with your surgical/anesthesia team for individualized instructions (see The Medical Letter peri-procedural guidance (2024)).

Educational disclaimer: These are general strategies, not individualized medical advice.


Serious Side Effects Of Mounjaro — Clear Warning Signs, In Plain English

Most people never experience these, yet it’s important to know what to watch for. Full details live in the Mounjaro prescribing information (May 2025).

Pancreas And Gallbladder — When Stomach Pain Isn’t “Just GI”

  • Acute Pancreatitis: Sudden, severe upper-abdominal pain (often radiating to the back) with nausea/vomiting → same-day assessment.
  • Gallbladder Disease: Right-upper-quadrant pain (sometimes after meals) ± fever or jaundice → prompt evaluation.

Kidneys — Dehydration Can Snowball

Repeated vomiting/diarrhea plus dizziness or very low urine can tip you toward acute kidney injury. If fluids aren’t staying down, you may need IV hydration and labs—don’t wait for things to get worse.

Vision — Who Needs Closer Monitoring

If you have diabetic retinopathy, rapid glucose improvement can temporarily worsen retinopathy or cause blur—book an eye exam (see prescribing info). Meanwhile, the JAMA Ophthalmology 2025 cohort suggested a small class-level nAMD association; keep routine checks regardless.

Hypersensitivity — Don’t Second-Guess This

Swelling of lips/face/tongue, hives, trouble breathing, or wheezing after an injection = urgent care.

Stomach And Anesthesia — Aspiration Risk Is Manageable With Planning

GLP-1s slow gastric emptying. For procedures with anesthesia or deep sedation, approaches are individualized—based on your symptoms and the procedure type—rather than a blanket stop. Coordinate with your care team (see The Medical Letter peri-procedural guidance (2024)).

Muscle — Rare But Serious

Rhabdomyolysis is rare but serious. Severe muscle pain, true weakness, or cola-colored urine after starting or increasing dose needs same-day evaluation (see the 2025 case report in the references list).

Thyroid Boxed Warning — Who Should Avoid

Tirzepatide carries a boxed warning for thyroid C-cell tumors seen in rodents. People with a personal/family history of medullary thyroid carcinoma or MEN2 should not use it. If you have thyroid nodules or concerns, talk to your clinician.

Informational only—follow your clinician’s advice for your situation.


Quick “Should I Call?” Filter For Mounjaro Side Effects

Call the same day if you have:

  • Severe abdominal pain (especially with vomiting).
  • Persistent vomiting/diarrhea plus dizziness or very low urine.
  • Sudden vision changes (especially if you’ve had retinopathy).
  • Allergic-type symptoms (swelling, breathing trouble, hives).
  • Severe muscle pain/weakness or dark urine.

When in doubt, it’s okay (and wise) to call.


Everyday Habits That Reduce Mounjaro Side Effects (A Practical Toolkit)

Hydration & Electrolytes. Set a daily fluid target; on rough GI days, use an oral rehydration solution. Consequently, you’ll often see fewer leg cramps on Mounjaro, less “whole-body ache,” and steadier energy.

Protein At Every Meal. Even distribution—breakfast, lunch, dinner—supports recovery, preserves lean mass, and reduces “all-over” soreness during weight loss.

Movement Hygiene. Brief post-meal walks, 2–3 short resistance sessions weekly, and daily mobility for tight spots (neck, hips, calves) go a long way. Build gradually; don’t leap.

Dose Pacing. If symptoms surge at every increase, extend the step. Many people feel dramatically better with an extra week or two at a tolerable dose.

Educational reminder—this is not personalized medical advice.


References


Final Disclaimers

  • This article is informational and educational. It does not replace personalized medical advice, diagnosis, or treatment.
  • Dose pacing, nutrition, and symptom management should be coordinated with your clinician.
  • If you believe you’re experiencing a medical emergency, call your local emergency number immediately.

FAQs on Side Effects of Mounjaro

Informational only—these FAQs are educational, not medical advice. If a symptom is severe, persistent, or feels “not you,” please speak with your clinician.

1) Do Mounjaro Side Effects Happen Right Away Or Later?

Most Mounjaro side effects appear during the first few weeks and again after each dose increase. However, they often ease as your body adapts. If a new symptom appears suddenly or feels severe, check in with your clinician.

2) Are Mounjaro Body Aches Normal?

Mounjaro body aches can happen, especially during dose escalations. They’re often related to dehydration, electrolyte shifts, or routine changes. Consequently, steady fluids, light movement, and dose pacing usually help.

3) Can Mounjaro Cause Muscle Pain Or Muscle Aches?

Yes, Mounjaro muscle pain can occur for some people. It’s commonly mild and linked to volume depletion or new exercise. However, severe pain, true weakness, or dark “cola” urine needs same-day medical review.

4) What About Mounjaro Joint Pain—Is That Expected?

Some experience Mounjaro joint pain or “joint awareness,” especially as weight, posture, and activity change. Gentle mobility, hydration, and gradual training can reduce it. Hot, swollen joints or fever require evaluation.

5) Why Do I Get Leg Cramps On Mounjaro?

Leg cramps on Mounjaro often trace back to low fluids or electrolytes, particularly after nausea, vomiting, or diarrhea. Therefore, rehydrate early, replace electrolytes, and stretch in the evening.

6) I Have Neck Pain On Mounjaro—Should I Worry?

Mounjaro neck pain is usually muscle tension or posture-related as activity patterns shift. Still, if pain is severe, radiates, or includes numbness/tingling or weakness, seek medical advice.

7) Does Mounjaro Cause Hip Pain Or Knee Pain?

Some report Mounjaro hip pain or Mounjaro knee pain, typically from changes in gait during weight loss or from ramping workouts too fast. Gradual progressions, supportive footwear, and low-impact cardio help.

8) Can Mounjaro Cause Body Aches After The First Dose?

Yes—first-dose days and step-up weeks are the most likely times. Fortunately, aches often fade within days as hydration and meal structure improve.

9) Is Muscle Weakness A Side Effect Of Mounjaro?

Minor fatigue can appear during appetite suppression. However, true weakness—especially with severe muscle pain or dark urine—needs urgent care to rule out serious issues.

10) What Are The Most Common Mounjaro GI Side Effects?

Nausea, diarrhea, decreased appetite, constipation, and heartburn/burping are the headliners. They tend to cluster early and settle with smaller, earlier, lower-fat meals plus dose pacing.

11) Does Mounjaro Cause Diarrhea Or Constipation—And What Helps?

Both can happen. For diarrhea, replace fluids/electrolytes early and trim triggers like greasy meals or sugar alcohols. For constipation, build fluids, fiber, and movement; then consider a gentle osmotic if needed.

12) Why Am I Burping So Much On Mounjaro?

Slower gastric emptying and large/high-fat meals can increase burping and belching. Therefore, eat smaller portions, dine earlier, and stay upright after meals. Left-side sleeping can also help.

13) Does Mounjaro Cause Heartburn Or Indigestion?

It can. Structure meals (smaller, earlier), reduce trigger foods (very fatty meals, mint, citrus, caffeine), and elevate the head of the bed. Persistent or severe reflux deserves a check-in.

14) Can Mounjaro Cause Headaches?

Headaches may appear when hydration, caffeine, or sleep patterns change. Steady fluids, regular meals, and consistent bedtime often help. However, sudden or severe headaches need medical advice.

15) Why Do I Feel Tired On Mounjaro?

Mounjaro tiredness can stem from lower calorie intake, dehydration, or sleep disruption. Consequently, aim for balanced meals with protein, sip fluids regularly, and respect recovery on dose-change weeks.

16) Is Hair Loss On Mounjaro A Real Thing?

Yes—some people notice hair loss on Mounjaro, commonly a temporary shedding pattern called telogen effluvium. It often follows rapid weight loss or nutrition gaps and improves as intake stabilizes.

17) Can Mounjaro Affect Vision Or Cause Blurry Vision?

Mounjaro vision changes are uncommon. Yet, if you have diabetic retinopathy or your sugars are improving rapidly, transient blur can occur. Therefore, schedule an eye exam if vision changes appear.

18) Do Mounjaro Side Effects Differ By Dose (2.5 mg vs 5 mg vs 10 mg, etc.)?

Side effects often flare at each dose increase. Many people do better by staying longer at a comfortable dose before stepping up. In other words, slower titration can mean smoother weeks.

19) Are There Serious Side Effects Of Mounjaro I Should Know?

Yes, but they’re uncommon. Red flags include severe abdominal pain (with vomiting), signs of dehydration with very low urine, allergic reactions (swelling, hives, breathing trouble), sudden vision changes, or severe muscle pain/weakness with dark urine.

20) Does Mounjaro Cause Body Aches After Each Weekly Shot?

Some feel a mini-wave of queasiness or body aches within 48–72 hours of the injection. Consequently, earlier lighter dinners, steady fluids, and gentle movement can make “shot days” easier.

21) How Long Do Mounjaro Side Effects Last?

Many symptoms settle within 1–3 weeks at a given dose. If a side effect doesn’t ease—or it worsens—despite basic strategies, it’s time to check in with your clinician.

22) Can I Prevent Mounjaro Side Effects Before They Start?

You can reduce risk: escalate doses slowly, keep meals smaller and earlier, hydrate daily, and plan light exercise plus sleep consistency during step-up weeks.

23) Are Mounjaro Side Effects Different For Weight Loss vs Diabetes?

The pattern is similar—GI effects lead—yet timing and intensity can differ by individual factors (diet, speed of glucose improvement, titration, baseline health). Personalization matters.

24) Does Mounjaro Cause Long-Term Side Effects?

Most side effects are short-term and dose-related. However, any persistent or worrisome symptom—especially visual changes, gallbladder-type pain, or severe muscle issues—warrants medical review.

25) Can Mounjaro Cause Aches And Pains Weeks After Starting?

Yes, especially around dose changes or big routine shifts. Meanwhile, hydration, electrolytes, protein at meals, and gentler training usually turn the corner within days.

26) What Should I Do If I Have Severe Nausea Or Vomiting On Mounjaro?

Prioritize fluids and call sooner rather than later. Tiny sips of oral rehydration, bland foods, and a quieter activity plan help—but inability to keep fluids down is a reason to seek care.

27) What If I Have Persistent Diarrhea On Mounjaro?

Rehydrate early, step back from greasy/spicy foods and sugar alcohols, and add soluble fiber after cramps ease. If diarrhea persists, especially with dizziness or very low urine, call your clinician.

28) Are Injection-Site Reactions Common?

Mild redness or itch can appear; rotating sites and letting alcohol dry before injecting usually helps. However, spreading rash, warmth, or swelling deserves a check.

29) Does Mounjaro Raise Or Lower Blood Pressure?

Weight loss and improved insulin sensitivity can lower blood pressure in some people over time. Nevertheless, watch for dehydration on rough GI days, which can make you feel light-headed.

30) When Should I Call A Clinician About Mounjaro Side Effects?

Call the same day for: severe abdominal pain, persistent vomiting/diarrhea with dizziness or low urine, sudden vision changes, allergic-type symptoms, or severe muscle pain/weakness with dark urine.


Friendly reminder: everyone’s response is unique. Therefore, if something feels off, you don’t need to wait—reach out to your clinician for personalized guidance.

Posted on — 2 Comments

Side Effects of Creatine: What You Need to Know

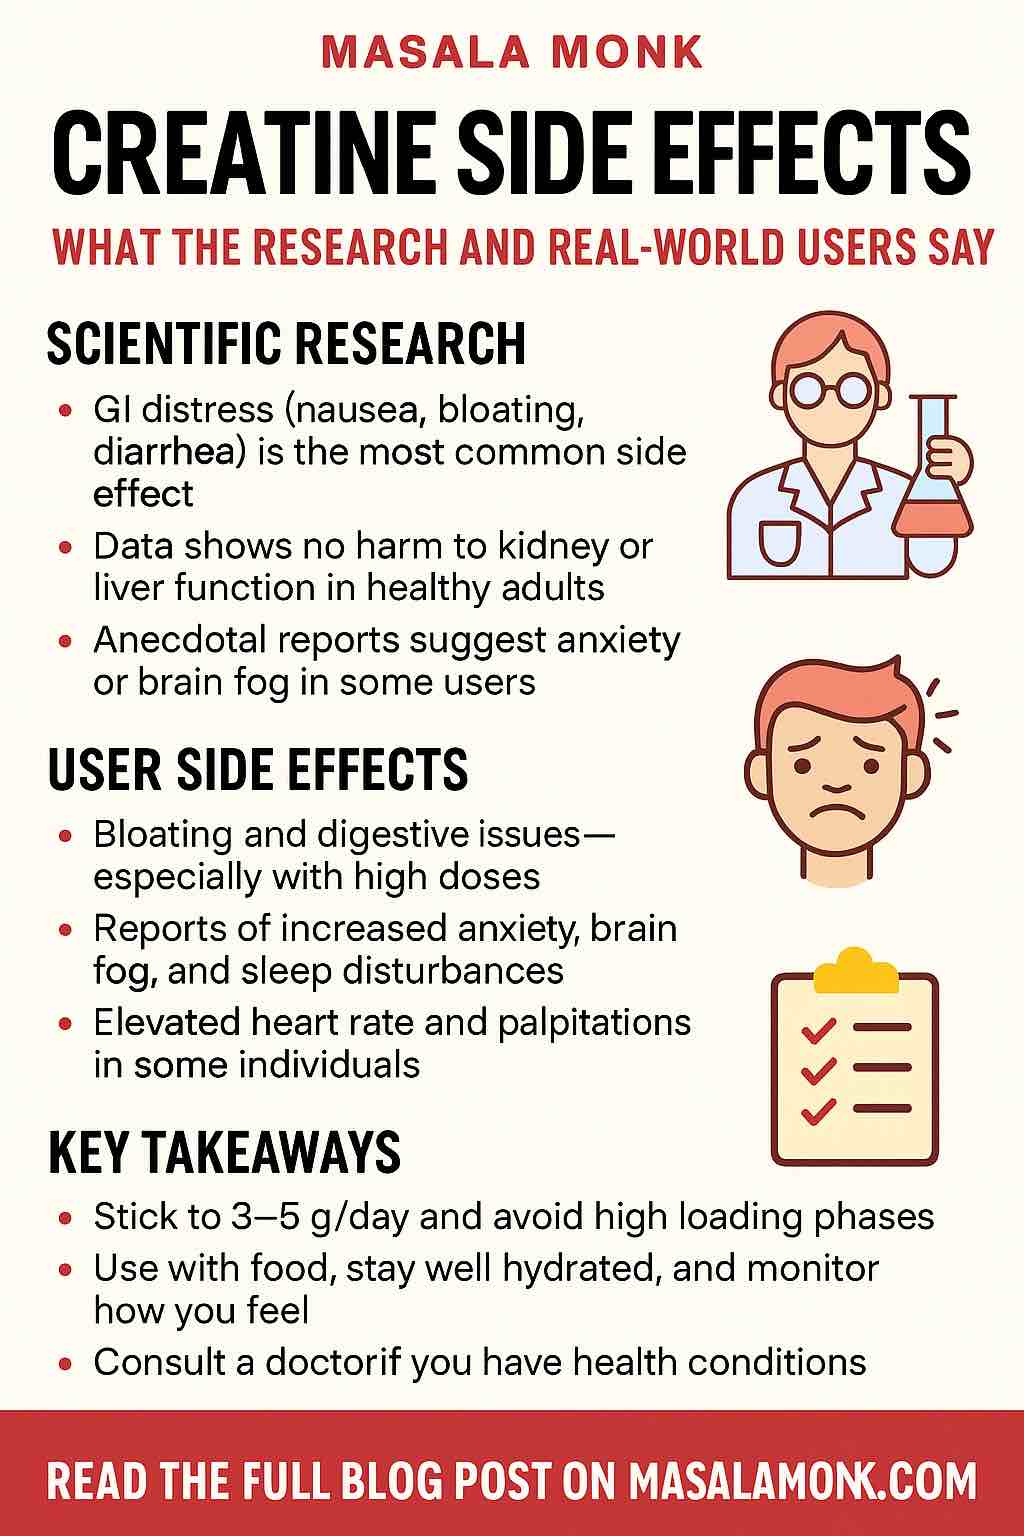
CREATINE SIDE EFFECTS

Creatine has long held the spotlight in the fitness and sports nutrition world, hailed for its ability to enhance muscle mass, strength, and performance. But as its popularity has surged among both athletes and everyday fitness enthusiasts, so too have concerns about its potential side effects. Is creatine really as safe as claimed? Or are there hidden downsides masked by its benefits?

In this detailed blog post, we’ll examine the most up-to-date clinical research as of 2025, compare that with real user experiences, and offer practical strategies to safely supplement creatine while minimizing risks. Whether you’re already taking creatine or just considering it, this guide will give you the nuanced understanding you need.


🔬 The Scientific Verdict: Creatine Is Largely Safe

A sweeping 2025 meta-analysis encompassing 685 clinical trials and over 25,000 participants has added significant weight to the scientific consensus: creatine is safe for healthy adults when used at recommended doses. In this landmark review, the incidence of side effects among creatine users (13.7%) was nearly identical to that of placebo users (13.2%).

This mirrors decades of smaller studies and expert opinions, such as those from the International Society of Sports Nutrition (ISSN), which affirm creatine’s safety profile across multiple health markers—especially when consumed as creatine monohydrate at 3–5 g/day.

However, “safe” doesn’t mean free from all side effects—particularly in individuals with certain sensitivities or preexisting health conditions. Let’s break this down in more detail.


🫰 Commonly Reported Side Effects (and What Science Says)

1. Gastrointestinal Discomfort

Clinical finding: Mild bloating, cramping, or diarrhea is the most frequently reported side effect, especially during high-dose loading phases (20 g/day).

User experience: Many Reddit and forum users report upset stomachs, gas, and nausea—particularly when taking creatine on an empty stomach.

Prevention tips:

  • Stick to 3–5 g/day; skip the loading phase.
  • Take with meals to improve tolerance.
  • Use micronized creatine monohydrate for better solubility.

2. Water Retention and Temporary Weight Gain

Clinical finding: Creatine draws water into muscle cells, leading to an initial weight increase of 1–2 kg. Long-term studies find no impact on total body water balance.

User experience: Many users report feeling “puffy” or bloated early in supplementation, but often note this dissipates over time.

Reality check: This is intramuscular water, not fat gain, and often enhances muscle fullness.

3. Sleep Disturbances and Night Sweats

Clinical finding: Largely anecdotal, with no confirmed link in clinical trials.

User experience: A noticeable subset report insomnia, vivid dreams, or night sweats—especially when dosing late in the day.

Prevention tips:

  • Take creatine earlier in the day.
  • Stay well hydrated.

4. Mood Effects, Anxiety, and Brain Fog

Clinical finding: Some evidence suggests creatine may help with cognitive function and mood in depression, but there are mixed reports in otherwise healthy users.

User experience: Some users describe brain fog, emotional dullness, or worsened anxiety—potentially linked to creatine’s role in brain energy metabolism or methylation pathways.

Caution: Those with a history of anxiety or bipolar disorder should consider starting with lower doses and consulting a healthcare provider.

5. Heart Rate & Palpitations

Clinical finding: No reliable evidence of cardiovascular stimulation.

User experience: A few individuals report increased heart rate or mild palpitations, which may be secondary to dehydration or anxiety rather than creatine itself.

Tip: Ensure proper hydration and evaluate for other confounding factors like caffeine intake.


🧬 The Most Debunked Myths About Creatine

  • Kidney Damage: No evidence supports kidney damage in healthy users at standard doses—even in long-term studies up to 5 years.
  • Liver Damage: Similarly, liver enzymes remain stable in clinical evaluations.
  • Hair Loss & Acne: No direct mechanistic link exists, though speculation around increased DHT remains unproven.
  • Cramping & Dehydration: In fact, some studies show fewer cramps due to enhanced muscle hydration.
  • Rhabdomyolysis: Creatine is not linked to rhabdomyolysis in healthy users; risk is more associated with extreme training or other medications.

🧰 Who Should Be Cautious?

  1. Individuals with Preexisting Kidney Conditions: Always consult a physician.
  2. Those with Bipolar Disorder or Mood Instability: Some case studies link creatine to manic episodes.
  3. Adolescents: Safe use is possible, but long-term data is still emerging.
  4. Pregnant or Breastfeeding Individuals: Insufficient evidence for safety.

⚡ Best Practices to Minimize Side Effects

  • Use a pure, micronized creatine monohydrate with third-party certification (e.g., NSF, Informed Sport).
  • Stick to 3–5 g/day—no need to load unless under guidance.
  • Take with a carb-rich meal to aid absorption and minimize GI issues.
  • Hydrate consistently, especially during workouts.
  • Avoid combining with stimulants if you’re sensitive to heart rate changes.

📊 Summary: Creatine Is Effective and Mostly Safe, But Not for Everyone

Creatine remains one of the most well-researched and effective supplements available—offering real benefits for muscle growth, performance, and even cognitive health. The risks? Generally mild and avoidable for most people, particularly when used responsibly. But it’s clear from both research and user reports that some individuals may experience side effects—especially when underlying health issues or poor supplementation practices are at play.

As with any supplement, personalization is key. Start low, monitor how you feel, and adjust as needed.


Have you experienced side effects from creatine, or found a strategy that worked for you? Share your insights in the comments—we’d love to hear from real users and keep the conversation evidence-informed and grounded in real-world use.

🔍 10 Frequently Asked Questions (FAQs)

1. Is creatine safe for long-term use?
Yes, long-term studies (up to 5 years) show no adverse effects in healthy individuals when taking recommended doses (3–5 g/day). Kidney and liver function remain unaffected.

2. What are the most common side effects of creatine?
The most frequently reported side effects are bloating, mild stomach discomfort, and temporary water retention—mostly during loading phases or when taken without food.

3. Can creatine cause anxiety or brain fog?
While rare, some users report increased anxiety or mental cloudiness. There’s limited scientific evidence, but people with anxiety disorders should start with lower doses and monitor their response.

4. Does creatine affect sleep or cause night sweats?
Clinical data doesn’t support a link, but anecdotal reports suggest it might in some individuals. Taking it earlier in the day and staying hydrated may help.

5. Is creatine bad for your kidneys?
No. Numerous studies confirm that creatine does not harm kidney function in healthy users. Those with pre-existing kidney issues should consult a healthcare provider first.

6. Can creatine worsen acid reflux or heartburn?
There’s no strong evidence, but a few users report increased reflux. Taking creatine with food and avoiding high doses may reduce this possibility.

7. Is it necessary to do a loading phase with creatine?
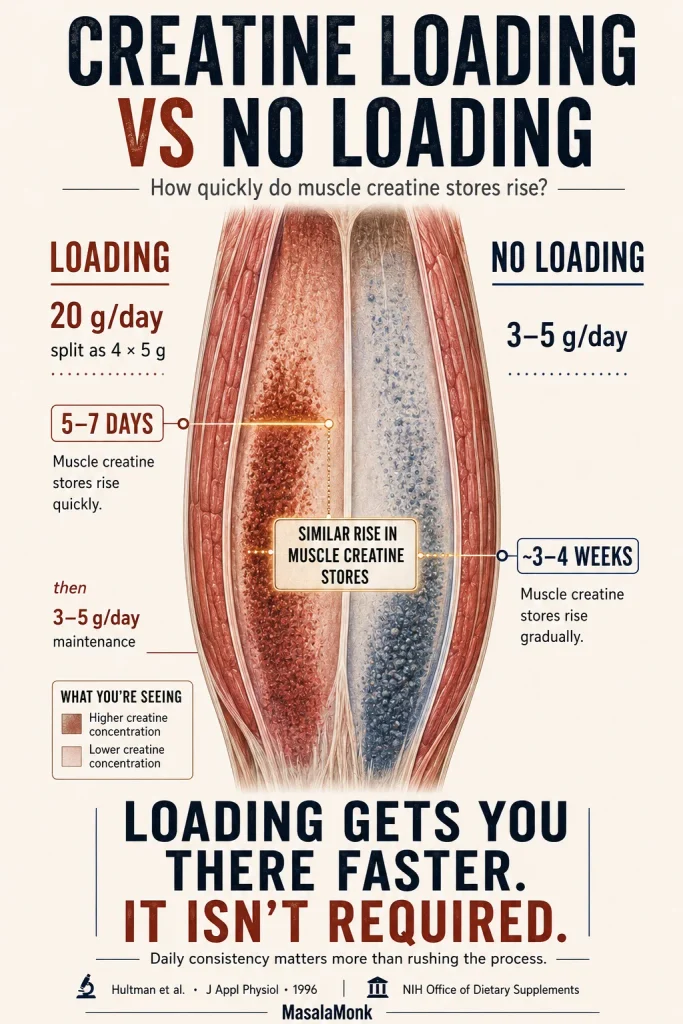
No. While loading (20 g/day for 5–7 days) saturates muscles faster, daily intake of 3–5 g reaches the same levels within 3–4 weeks and has fewer side effects.

8. Will creatine make me gain fat or look bloated?
Creatine increases water content in muscle cells, not fat. Some early bloating may occur, but it typically subsides and muscle definition often improves.

9. Are there differences in side effects between creatine monohydrate and other forms?
Creatine monohydrate is the most studied and generally best tolerated. Other forms (e.g., HCL, ethyl ester) claim better absorption but lack robust data and may not reduce side effects.

10. Can teenagers safely use creatine?
Some research supports safe use in adolescents involved in supervised athletic programs, but long-term safety data is limited. Parental guidance and medical consultation are advised.

Posted on — Leave a comment

Creatine Uncovered: The Science, Benefits, and Myths

Athletic woman in a sunlit gym holding a clear shaker beside a small bowl and scoop of white creatine powder, with the title “Creatine Uncovered: The science, benefits & myths.”

Updated:

This guide has been substantially revised to include newer evidence on creatine and kidney function, hair loss, strength, body composition, cognition, postmenopausal women and safety.

Creatine used to be easy to understand. Lifters took it because it helped them train harder and get stronger.

Now someone is taking it for menopause. Someone else is worried it will ruin their kidneys. And someone who has never touched a barbell is considering it for their brain while quietly wondering what that daily scoop might do to their hairline.

Creatine deserves neither the old fear nor the new mythology.

Creatine: the short answer

If you are standing in front of a tub wondering what matters, start here.

  • Creatine works best where the evidence is deepest: resistance-training strength, repeated high-intensity exercise and somewhat greater lean-mass gains alongside training.
  • Creatine monohydrate is the default form to buy. More expensive alternatives have not convincingly shown that they work better.
  • For most healthy adults who choose to supplement, 3–5 g/day is a simple routine. Loading is optional: about 20 g/day split into four doses for 5–7 days raises stores faster, while a smaller daily dose gets there more gradually.
  • Consistency matters more than a perfect workout window. Rest days use the same daily routine, and routine cycling is not established as necessary.
  • Early scale weight can rise. Water associated with muscle can contribute, so a quick increase does not tell you that you gained the same amount of fat—or pure new muscle.
  • The healthy-adult safety literature is reassuring, while newer claims deserve different levels of confidence. Creatinine-based kidney tests can be affected by creatine use; direct hair-loss evidence is reassuring; memory and postmenopausal findings are promising but narrower than the marketing often suggests.

Creatine monohydrate remains the most studied form, and the NIH Office of Dietary Supplements summarizes the common loading and non-loading approaches used in research.

What is creatine actually good for?

The internet tends to flatten very different claims into one enormous list of “creatine benefits.”

The evidence falls into very different tiers.

Creatine evidence graphic organizing benefits by strength of research, with the clearest support for strength, repeated high-intensity performance and resistance-training outcomes, while cognition and recovery are less certain and endurance benefits are weaker.
Use the evidence hierarchy as a filter whenever you encounter a new creatine benefit claim. Ask what researchers actually measured: a real performance or health outcome, a surrogate marker, or merely a plausible mechanism. Mechanisms are useful reasons to investigate an idea; they should not automatically be promoted to the same status as replicated human outcomes.
OutcomeWhere the evidence stands
Strength with resistance trainingStrong
Repeated high-intensity exerciseStrong
Additional lean-mass gains with resistance trainingStrong
Lean mass and strength in some older adults alongside resistance trainingGood evidence
Lean mass and strength after menopause, particularly with resistance trainingPromising / increasingly supported
Memory and some cognitive outcomesPromising, but mixed overall
Long-duration endurance performanceNo meaningful overall benefit established
Soreness and faster recovery from every workoutMixed
Direct fat lossNot established
Where creatine has its strongest outcome evidence—and where expectations should stay lower.

That difference between established, promising and plausible matters throughout this subject.

What creatine does inside your muscles

Your body already makes creatine, and foods such as meat and fish provide additional dietary creatine.

Most of the body’s creatine is stored in skeletal muscle. Some exists as phosphocreatine, which helps regenerate ATP when energy demand rises very quickly.

You do not need the biochemistry-textbook version to understand the practical consequence.

Think of phosphocreatine as part of a small, rapidly available energy reserve. Increasing muscle creatine gives that system more capacity.

That becomes particularly useful when the work is hard, short and repeated: another heavy set, another sprint, another explosive effort.

What will you actually notice after starting creatine?

Imagine you begin taking 3–5 g of creatine monohydrate every day.

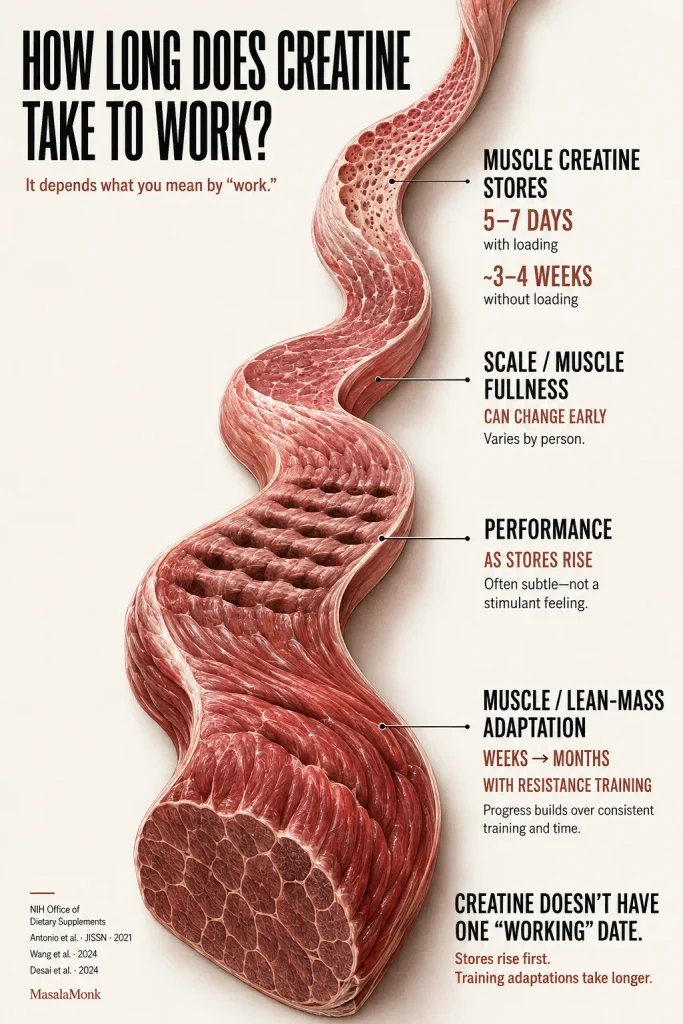
Your muscle creatine stores gradually rise. Loading makes that happen faster; smaller daily dosing gets there more gradually. NIH Office of Dietary Supplements

The scale may move before your gym numbers do.

Your muscles may look a little fuller.

And you may feel…exactly the same.

That last part catches people out. Creatine is not caffeine. There is no required buzz or dramatic moment when it “kicks in.” Its benefit often appears in repeated work: maintaining performance a little better, completing slightly more useful training, or accumulating better sessions over time.

If you have taken creatine for three weeks and are thinking, I can’t feel anything, that does not automatically mean you need more.

A continuous muscle-ribbon timeline shows creatine stores rising in about 5–7 days with loading or 3–4 weeks without loading, followed by possible performance changes and slower muscle or lean-mass adaptation over weeks to months with resistance training.
If you want to judge whether creatine is helping, “Can I feel it?” is a poor test. Instead, keep the routine stable and watch what happens across repeated training sessions. Creatine can be doing its job without producing a buzz, pump or obvious moment when it suddenly switches on.

What about over months rather than days?

This is where supplementation and training become much more interesting.

A 2024 meta-analysis of resistance training and body composition found that adults under 50 who combined creatine with resistance training gained about 1.14 kg more lean body mass than those doing resistance training without creatine. Small favourable changes in body-fat measures were also reported.

That is not evidence that one scoop manufactures a kilogram of muscle. It is evidence that creatine can help resistance training produce somewhat greater adaptations over time.

Where creatine earns its reputation

Strength

This remains one of the clearest cases for taking creatine.

A 2025 systematic review and meta-analysis of 69 studies involving 1,937 adults separated several common strength tests instead of collapsing them into one upper- or lower-body number. Compared with placebo, creatine plus resistance training produced statistically significant pooled improvements in bench/chest press strength (+1.43 kg) and squat strength (+5.64 kg).

The same analysis did not find statistically significant overall differences for leg press or handgrip strength. It also reported significant improvements in vertical jump and Wingate peak power, reinforcing that creatine’s performance signal depends partly on the outcome being tested.

Those values are pooled group averages, not predictions for your next personal record. Different exercises, populations, training programs and study designs produce different estimates. Overall, resistance training tends to produce somewhat greater strength and power gains when creatine is added, but there is no single universal “creatine strength increase.”

Four female athletes perform a bench or chest press, squat, leg press and handgrip test; pooled results show a 1.43 kg average improvement for bench or chest press and 5.64 kg for squat, with no significant overall difference for leg press or handgrip.
Exercise-specific results should not be read as “creatine works for squats but not leg press.” Different pooled outcomes contain different studies, people and training protocols. More importantly, creatine can add a modest training advantage on average, while the size of that advantage is not fixed across every exercise or lifter.

Repeated high-intensity exercise

Creatine also performs well in activities built around short, hard efforts with limited recovery:

  • resistance training;
  • repeated sprints;
  • explosive efforts;
  • sports involving repeated bursts of high power.

That is exactly where the phosphocreatine system is most relevant.

Lean mass—if there is a training stimulus

Creatine can increase water associated with muscle fairly quickly. Over longer resistance-training interventions, it can also help produce greater lean-mass gains. See the 2024 body-composition meta-analysis.

Both are real.

Two popular summaries are both too simple: “Creatine gains are just water” and “every kilogram of extra lean mass is pure new muscle.” The early and long-term changes are not the same thing.

What creatine is less impressive at

A useful creatine guide should also tell you where enthusiasm needs cooling.

Long-duration endurance

Creatine is particularly good at supporting intense, repeatable muscular work. It has not shown the same clear advantage for prolonged endurance performance.

A systematic review and meta-analysis in trained participants found no meaningful overall endurance-performance benefit from creatine monohydrate.

A 2026 scoping review of endurance and mixed-sport research adds a useful distinction. The more favourable signals tended to appear in selected contexts involving repeated high-intensity efforts, sprint finishes and power-endurance demands, while aerobic outcomes remained limited or inconsistent.

That is why “creatine for runners” is not a yes-or-no question. A distance athlete who also strength trains, attacks hills, performs repeated hard surges or relies on a finishing sprint has different demands from someone concerned only with prolonged steady-state endurance. Creatine is not a proven general endurance booster; its physiological fit is stronger when the event temporarily becomes intense.

The same female runner appears twice on a mountain road, first at a steady endurance pace and later accelerating hard; the graphic reports no significant pooled endurance benefit across 13 controlled studies but more favorable signals in short high-intensity efforts.
Being a “runner” does not answer whether creatine fits your goals. A runner who also strength trains, performs repeated sprints or relies on explosive race moments has a different performance profile from someone focused almost entirely on prolonged steady endurance. The decision should follow the demands of the sport—not the label attached to the athlete.

Direct fat loss

Creatine is not a fat burner.

Resistance-training studies sometimes show favourable body-composition changes when creatine is added, but that should not be rewritten as “creatine melts fat.” Diet, energy intake, daily activity and training remain the important variables if fat loss is the goal.

Soreness and recovery

Recovery research is much less consistent than the strength literature.

One systematic review found no meaningful improvements in soreness, muscle-strength recovery, inflammation or range of motion after muscle-damaging exercise, although creatine kinase was reduced at one time point. Other meta-analytic work has found potentially favourable changes in some muscle-damage markers but substantial heterogeneity.

Creatine may eventually prove useful for particular recovery outcomes. It is not something I would buy primarily because I want tomorrow’s leg-day soreness to disappear.

↑ Back to guide

The scale went up. Did creatine make you fat?

You start creatine on Monday.

By the weekend, the scale is 800 grams higher.

If you are trying to lose fat, that can be unsettling.

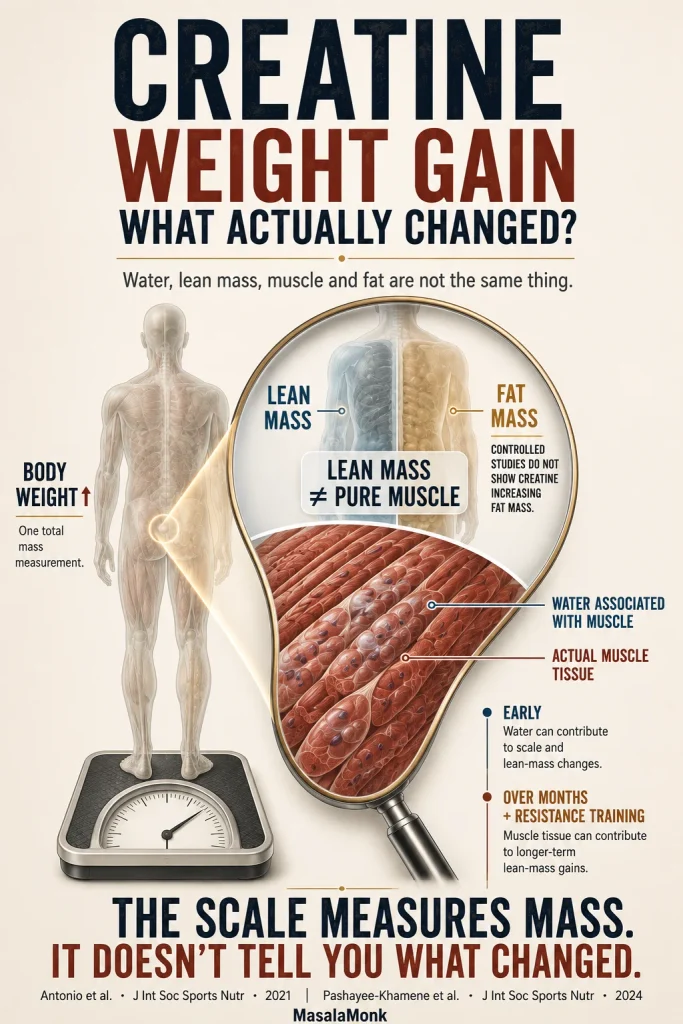
But the scale cannot tell you whether that change came from body fat, muscle tissue, glycogen, water, food and fluid still in the digestive system, or several of these together.

Creatine increases muscle creatine storage, and water accompanies that process. An early increase in body mass can therefore happen far faster than you could plausibly build the same amount of new muscle tissue.

It is also not the same as gaining 800 grams of fat.

Scale-to-body-composition graphic showing body weight separating into lean mass and fat mass, then magnifying lean mass into muscle tissue and associated water to explain why creatine-related weight gain does not reveal exactly what changed.
If body weight is one of your progress markers, note when you start creatine before interpreting a sudden change. The supplement can make the scale noisier before anything meaningful has happened to body fat, so one unexpectedly high week should not automatically trigger changes to an otherwise sensible nutrition or training plan.

Water, lean mass and muscle are different things

What you noticeWhat may be happening
Scale rises relatively quicklyIncreased water can contribute
Muscles look somewhat fullerMore intramuscular water may contribute
A scan reports more lean massLean mass includes water and other non-fat tissues
Strength and lean mass increase over monthsTraining adaptations and creatine can both contribute
Body fatCreatine does not simply turn into fat
What an early change in scale weight or “lean mass” can—and cannot—tell you.

The opposite mistake happens too. If a scan reports an extra kilogram of “lean mass,” that should not automatically be described as a kilogram of newly built muscle fibre.

If the water part is what worries you, that is a separate question from scale weight: see creatine, hydration and cramps.

Creatine and the brain: interesting science, incomplete answers

There is real biology behind the brain question.

The brain has enormous energy demands and uses a creatine-phosphocreatine system too. Supplementation can increase brain creatine, though the response appears more complicated than loading skeletal muscle. 2024 systematic review

Where things become difficult is translating that mechanism into noticeable cognitive outcomes.

A 2024 meta-analysis of 16 randomized trials involving 492 adults found improvements in memory, some measures of attention time, and processing speed. It did not find significant improvements in overall cognition or executive function, and confidence in the findings differed by outcome.

Another systematic review reached a more cautious conclusion, describing the cognitive findings as equivocal despite evidence that creatine can increase brain creatine. Read the review.

That disagreement is exactly why brain claims deserve more restraint than muscle claims.

A neutral brain model above a developing evidence sheet, with the strongest print for memory, a lighter low-certainty signal for attention and processing speed, and no significant pooled improvement shown for overall cognition or executive function.
A useful way to read any claim about creatine and the brain is to ask which cognitive ability actually improved. Better performance on a memory test does not automatically mean better concentration at work, greater productivity, higher intelligence or a noticeable everyday “brain boost.” Those are different claims requiring their own evidence.

What about sleep deprivation?

Creatine is particularly interesting when the brain is under unusually high energetic stress, including sleep deprivation.

Positive findings in those conditions deserve investigation. They do not mean creatine can substitute for sleep or that an experimental high-dose protocol should automatically become a normal “brain dose.”

Bottom line: memory has the most encouraging signal so far. Claims about universal focus, productivity, broad cognitive enhancement or prevention of neurodegenerative disease go beyond the current evidence.

The brain research is real. The marketing version is simply moving faster.

Creatine for women: the evidence is better than the old stereotype—and narrower than the new hype

Creatine spent years wrapped in male bodybuilding culture.

Now the pendulum is swinging hard in the other direction, with creatine sold to women for hormones, mood, menopause, muscle and cognition all at once.

The interesting evidence is narrower—and more useful—than that marketing bundle.

Women who train

Women use the same phosphocreatine energy system and can increase tissue creatine through supplementation. Female-specific research, however, is smaller than the overall creatine literature. We should not turn “women can benefit” into “women always respond better.”

After menopause

This is one area where newer research genuinely strengthens the case.

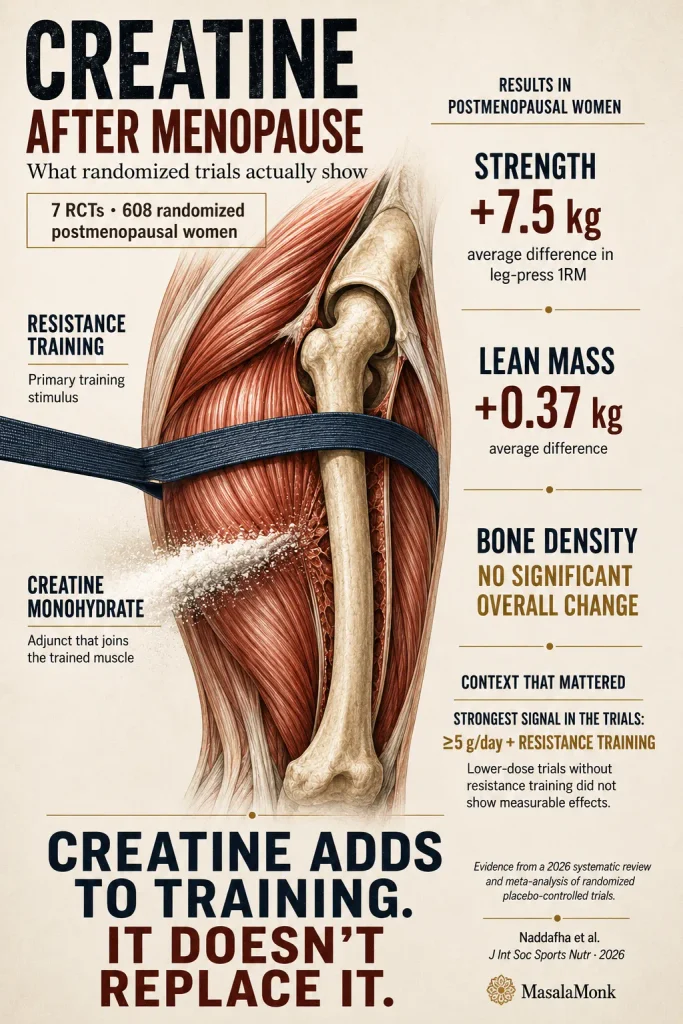
A 2026 systematic review and meta-analysis included seven randomized trials and 608 postmenopausal women overall. Five lean-mass comparisons involving 338 participants favoured creatine by about 0.37 kg, while three studies involving 111 participants contributed to the leg-press analysis, which favoured creatine by roughly 7.5 kg.

The clearest benefits appeared when at least 5 g/day was paired with resistance training. Overall bone density did not significantly improve. Most studies carried at least some risk-of-bias concerns, so the findings are encouraging rather than permission to attach every menopause claim imaginable to creatine.

That is a much stronger reason for interest than vague promises of “hormonal support.”

Postmenopause creatine graphic with a female muscle-and-bone model under resistance-training tension, summarizing seven randomized trials: average leg-press strength improved by 7.5 kg, lean mass by 0.37 kg, while bone density showed no significant overall change.
If the main reason for considering creatine after menopause is bone density, the current trials do not offer the same support they do for strength and lean mass. In practice, the evidence points toward creatine as a potential addition to resistance training—not as a stand-alone treatment for the many changes grouped under “menopause.”

Creatine as you get older

The resistance-training partnership also matters in older adults.

A 2025 systematic review and meta-analysis found that creatine added to resistance training improved lower-body strength and lean tissue mass compared with resistance training plus placebo in older adults.

That makes creatine an interesting adjunct when preserving strength and function matters increasingly with age.

No scoop, however, reproduces what progressive strength training asks your muscles, bones and nervous system to do.

Vegetarians and vegans may start from a different baseline

Dietary creatine comes mainly from animal foods.

People eating little or no meat may therefore begin with lower creatine stores, leaving more room for those stores to rise after supplementation. A systematic review of vegetarian and omnivorous athletes found that tissue creatine often increased more in vegetarian participants, while studies were mixed on whether their exercise-performance gains were greater than those of omnivores.

That does not guarantee that every vegetarian or vegan will gain more strength, muscle or cognitive benefit than every omnivore.

Lower baseline stores help explain why biological responses can differ. They do not guarantee a particular visible result.

↑ Back to guide

Is creatine safe?

For healthy adults taking commonly studied doses, creatine has an unusually large safety literature for a sports supplement.

A 2025 safety analysis covering 685 human creatine trials compared reported side effects across 12,839 creatine participants and 13,452 placebo participants. Overall participant-level side-effect reporting was 4.60% with creatine and 4.21% with placebo, a difference that was not statistically significant.

A separate 2026 study-level analysis across 684 randomized trials asked a different question: whether adverse effects showed a meaningful pattern as creatine dose or duration increased. Reported effects were generally infrequent and mild, and the analysis did not identify a consistent clinically meaningful dose- or duration-response pattern versus placebo.

That combination is reassuring: symptoms occur in both supplement and placebo groups, and the broad randomized-trial literature does not show the escalating safety pattern often implied online. It is still not evidence that every possible person in every medical situation should take creatine without thought.

An athletic woman sits in a gym holding a creatine drink beside loose creatine powder; callouts describe possible water-weight gain and GI upset, while a 685-trial comparison shows side-effect reporting of 4.60% with creatine and 4.21% with placebo, with no significant overall difference.
The placebo comparison matters because symptoms can appear during a trial even when creatine is not the cause. Therefore, a headache, stomach complaint or other symptom beginning after a new supplement deserves attention—but timing alone cannot establish causation. That distinction is useful well beyond creatine when evaluating supplement side-effect stories.

For a symptom-by-symptom discussion of gastrointestinal complaints, water retention and other reported effects, see our dedicated guide to creatine side effects.

Creatine, creatinine and your kidneys

Imagine you have been taking creatine for several months.

You get routine blood work.

Your creatinine comes back higher.

After years of hearing that creatine “damages kidneys,” connecting those dots would be easy.

The test itself makes the story more complicated.

Creatine and creatinine are related, but not interchangeable

Creatine is the compound being supplemented.

Creatinine is a breakdown product.

Serum creatinine is also commonly used to estimate kidney filtration.

If creatine supplementation changes creatinine production or metabolism, a kidney estimate that relies on creatinine can move even when actual filtration has not deteriorated in the same way.

Two 2026 analyses help show why the blood test can look worse even when kidney filtration has not necessarily become worse.

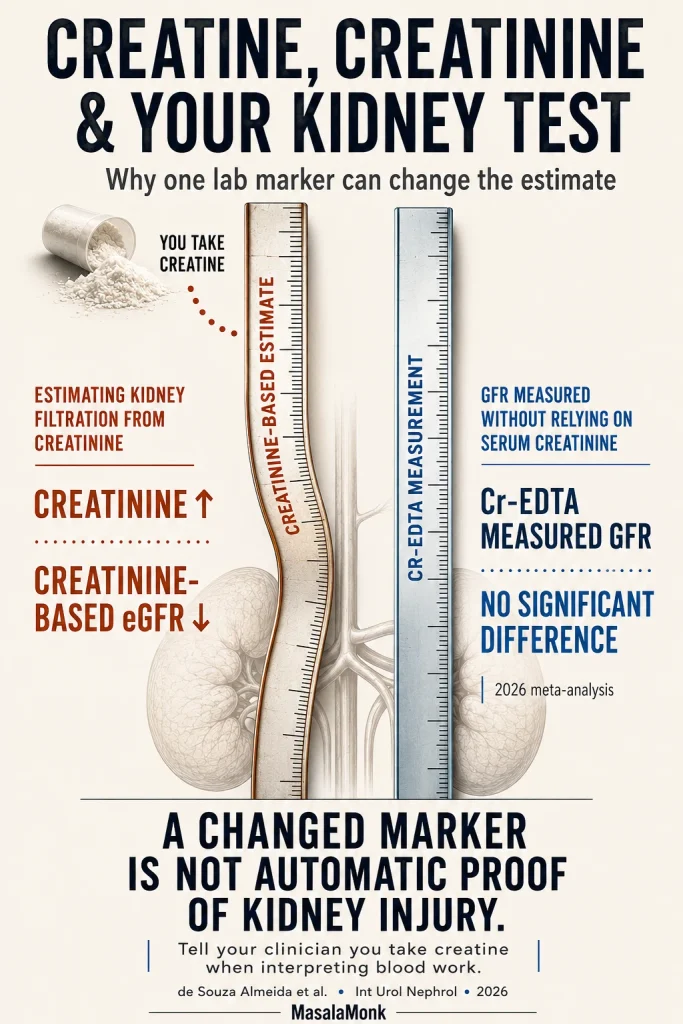
One meta-analysis of randomized trials found that supplementation increased serum creatinine by an average of about 0.13 mg/dL but did not find significant differences in urea or estimated GFR overall.

A second 2026 kidney-health meta-analysis went a step further. Across 26 studies, serum creatinine increased and creatinine-based GFR estimates decreased. But when filtration was assessed using Cr-EDTA, there was no statistically significant difference between creatine and control groups. Other kidney markers including albuminuria and proteinuria were also not significantly different.

The practical lesson: a creatinine-based estimate can be affected by something that changes creatinine metabolism. A higher result deserves clinical interpretation, but it is not automatic proof that creatine injured the kidneys.

Editorial kidney-test graphic separating creatine use, serum creatinine and kidney filtration, explaining that creatine can affect creatinine-based kidney estimates even when directly measured filtration does not show the same impairment.
There is an important measurement lesson here: when a supplement can change the marker used in an equation, the estimated result can move partly because the marker moved. That is why the directly measured filtration findings matter—they help separate a change in creatinine from evidence that kidney filtration itself deteriorated in the same way.

So should you ignore a high creatinine result?

No.

A changed laboratory result deserves appropriate interpretation. Tell the clinician reviewing your blood work that you take creatine. They can consider supplementation alongside your medical history, other laboratory markers and—when clinically appropriate—measures that are less dependent on creatinine.

The point is not to self-diagnose yourself as healthy. It is also not to diagnose yourself with creatine-induced kidney damage from a single number.

What if you already have kidney disease?

That is a different situation from a healthy adult taking a sports supplement.

Research in people with kidney disease is much more limited, and Mayo Clinic recommends that people with kidney disease discuss creatine with their healthcare team.

Does creatine cause hair loss?

This rumour survived because there was just enough science underneath it to sound convincing.

Where the worry came from

A small 2009 study in rugby players reported changes in dihydrotestosterone (DHT) during creatine supplementation.

DHT is relevant to androgenetic hair loss in genetically susceptible people.

A plausible concern therefore emerged:

creatine → higher DHT → hair loss.

One important detail disappeared as the story travelled around gyms and the internet.

The study did not measure hair loss.

Then researchers measured the hair

In 2025, researchers conducted a randomized controlled trial specifically examining creatine and hair-follicle health.

Forty-five resistance-trained men aged 18–40 were assigned to 5 g/day of creatine monohydrate or placebo for 12 weeks.

Researchers measured total testosterone, free testosterone, DHT, hair density, follicular-unit count and cumulative hair thickness.

They found no significant differences in DHT or measured hair outcomes between creatine and placebo. Read the randomized trial.

That is much more direct evidence than the creatine-hair debate had previously.

It is also one 12-week trial in young resistance-trained men. It cannot answer every possible lifetime question about every population.

But we can no longer accurately say that nobody has directly tested creatine and hair loss. They have. In that first direct randomized trial, the results did not support the claim.

Creatine hair-loss evidence timeline comparing the 2009 study that reported a DHT increase with a 2025 randomized trial that directly measured hair density, follicular units and hair thickness and found no significant difference between creatine and placebo.
This creatine–hair-loss story illustrates a broader evidence rule: changing a hormone associated with an outcome is not the same as measuring the outcome itself. A 2009 DHT finding raised a reasonable question; years later, researchers finally tested hair density and follicular measures directly. Surrogate signals and real-world outcomes should not be treated as interchangeable.

“But I started creatine and saw more hair in the shower”

That can be genuinely unnerving.

The difficult question is not whether you saw more hair. The difficult question is whether creatine caused it.

Hair shedding can change with genetics, age, illness, stress, calorie restriction, nutritional problems, medications and ordinary variation. When a new supplement and a new symptom appear close together, connecting them is natural.

Anecdotes are useful for spotting questions worth studying. Controlled trials are what help us test causation.

Does creatine dehydrate you?

Creatine increases water associated with muscle.

That fact somehow became a rule that creatine users must spend all day chasing a giant water target.

You do not need a special four- or five-litre creatine quota.

Hydration needs vary with body size, climate, sweat rate, exercise volume, diet, health and individual physiology.

If you are training outside in hot, humid weather, your fluid and electrolyte needs may be substantial because you are losing more fluid through sweat.

Creatine itself does not create an arbitrary universal number everyone must drink. Controlled evidence has not supported the old claim that recommended creatine use inherently causes dehydration or muscle cramping; a 2025 safety review found no significant adverse effect on hydration or thermoregulation in the controlled literature it assessed.

Hydrate according to your actual circumstances rather than a creatine-specific internet ritual.

A muscle specimen suspended in a clear fluid chamber under controlled heat illustrates that early water retention is not the same as dehydration; text notes that hydration and thermoregulation were not worsened, cramps were not shown to increase, and no universal creatine-specific water intake exists.
The same daily creatine dose can accompany completely different hydration needs. An air-conditioned rest day and a long outdoor session in hot, humid weather may require very different amounts of fluid and electrolytes—not because the creatine changed, but because sweat loss, exercise and environment did.

If creatine bothers your stomach

Gastrointestinal discomfort is one of the more plausible practical complaints, particularly when somebody suddenly tries to consume a large loading dose.

Before spending more money on an exotic creatine form, simplify.

  • skip loading;
  • keep each dose smaller;
  • split loading doses through the day;
  • take creatine with food if that feels better;
  • check whether your supplement contains sweeteners, stimulants or other ingredients that may be responsible.

The traditional loading protocol itself divides approximately 20 g across four doses rather than taking it all at once. NIH dosing guidance.

For many people, the stomach-friendly solution is simply 3–5 g/day without loading.

↑ Back to guide

How to take creatine without overthinking it

This can be a remarkably simple supplement.

SituationPractical approach
You want the simplest routine3–5 g creatine monohydrate daily
You want faster saturation~20 g/day split into 4 doses for 5–7 days, then 3–5 g/day
Loading upsets your stomachSkip it
It’s a rest dayTake your normal daily amount
You forgot yesterdayResume your normal dose today
You stop using creatineNo taper is required
A practical creatine dosing cheat sheet for everyday use.

Both loading and gradual daily dosing are well-established research approaches. NIH Office of Dietary Supplements

A continuous creatine-powder trail explains a simple daily routine: 3–5 g creatine monohydrate every day, the same approach on workout and rest days, optional loading, no proven perfect timing window, and no established need to cycle.
The easiest way to make creatine effective may be to make it boring. Attach the daily dose to a routine you already remember rather than building an elaborate supplement schedule around the clock. Consistency is easier to maintain when creatine becomes ordinary, not another task that requires perfect workout timing.

Is 3 grams enough?

For many people, yes.

The NIH describes non-loading research protocols around 3–6 g/day, including weight-adjusted approaches of roughly 0.03–0.1 g/kg/day, used over several weeks. See the dosing overview.

That does not mean the average recreational user needs a calculator. A consistent 3–5 g/day is much easier to follow than turning a simple supplement into body-weight mathematics.

Five grams is convenient. It is not a magical biological threshold.

Do you need to load?

No.

Loading mostly answers: How quickly do I want my muscle creatine stores to rise?

It does not answer: Will creatine eventually work if I don’t load it?

If you have a competition or a specific short timeline, reaching saturation quickly may matter. For a long-term gym routine, a slower daily approach is perfectly reasonable.

A skeletal-muscle visual compares creatine loading with no loading: 20 g/day split into four 5 g doses reaches elevated muscle creatine stores in about 5–7 days, while 3–5 g/day reaches a similar rise more gradually over about 3–4 weeks.
The real trade-off with a creatine loading phase is convenience. Faster saturation requires several larger doses across the day and can be harder on some stomachs; meanwhile, gradual daily dosing asks for more patience but less complexity. If reaching high stores quickly solves no real problem for you, speed itself may offer little practical value.

Before or after your workout?

For most users, the available timing literature does not support chasing a precise pre- versus post-workout window. Methodological limitations still prevent a firm recommendation for one ideal strategy. Review of creatine timing around exercise.

A 2026 randomized crossover pilot in 11 physically active men reported better acute lifting performance when creatine was consumed before exercise rather than during or after it. Interesting? Certainly. Enough to establish a new universal dosing rule? No—the authors themselves describe the findings as exploratory and in need of confirmation in larger studies.

Regular intake remains the more useful priority.

Morning works. Lunch works. After training works.

Choose a routine you will remember.

What about rest days?

Take your normal dose.

Creatine works through elevated tissue stores. Your muscles do not reset because today happens to be a rest day.

You forgot yesterday

Resume your normal amount.

There is no need to double today’s scoop or restart loading. One missed day does not erase weeks of accumulated muscle creatine.

Do you need to cycle creatine?

Routine creatine cycling has no established evidence-based requirement.

Gym culture borrowed “cycling” language from substances where cycling has entirely different biological reasons. Creatine is not an anabolic steroid.

What happens when you stop?

Muscle creatine stores gradually move toward baseline.

Some water-associated body weight may fall.

You do not need to taper, and there is no recognised creatine withdrawal syndrome.

Muscle that you genuinely built through months of training does not suddenly vanish because the supplement left your shaker.

Can you take creatine with coffee?

For ordinary coffee drinkers taking normal creatine doses, the evidence does not justify a blanket rule that caffeine and creatine must always be separated.

The reason the internet argument sounds contradictory is that the small research base has tested different ways of combining them. Two systematic reviews each identified only about ten relevant studies. One review found that acute caffeine taken after a creatine-loading phase generally did not erase caffeine’s ergogenic effect, whereas chronic caffeine consumed throughout loading produced mixed results: some studies suggested interference, several found no interaction and one reported synergy.

A second systematic review similarly found that acute caffeine after loading produced an additional ergogenic effect over creatine alone in three of five studies, while daily caffeine during loading produced an additive benefit in only one of five studies.

That is not enough evidence to invent a mandatory two-, four- or six-hour separation rule. Your morning coffee does not automatically cancel your creatine, but chronic high-caffeine use during a loading phase is less settled. If combining large doses makes your stomach miserable, separating or simplifying them is sensible.

The same athletic woman appears repeatedly mixing daily creatine and once drinking coffee before training, contrasting creatine as a daily strategy with caffeine as an acute stimulant; the graphic labels acute post-loading caffeine as generally compatible, chronic use during loading as mixed, and states that no universal separation rule exists.
When you see the claim that “caffeine blocks creatine,” ask how caffeine was actually used. Acute caffeine after a creatine-loading period and chronic high-caffeine intake during loading are different research situations, and they have not produced identical results. That distinction is more useful than inventing a universal coffee-versus-creatine rule.

Which type of creatine should you buy?

This is the easiest part.

Creatine monohydrate.

It has the deepest evidence base, a long history of use and usually the lowest price.

A systematic review examining alternative creatine forms found very few direct comparisons with monohydrate and no consistent evidence that newer forms outperform it.

FormWhat to know
Creatine monohydrateBest-studied default
Micronized creatine monohydrateSame form, smaller particles; may mix more easily
Creatine HClMarketed with advantages that have not convincingly beaten monohydrate in evidence
Buffered creatineNo established practical superiority over monohydrate
How common creatine forms compare with the monohydrate evidence base.

The NIH likewise notes that more expensive alternatives have not been proven superior for increasing muscle creatine, digestibility, stability or safety.

Laboratory-style comparison of creatine monohydrate, micronized monohydrate, creatine HCl and buffered creatine, showing micronized as finer-particle monohydrate, HCl as more soluble without proven better outcomes, and monohydrate as the most established reference form.
Once you have chosen creatine monohydrate, product quality matters more than increasingly exotic formulation language. For athletes subject to drug testing, independent sport certification may be especially valuable because contamination with prohibited substances is a different problem from whether creatine itself is effective.

“Micronized” is not a different type of creatine

Despite the label, micronized creatine is still creatine monohydrate.

The term simply means the powder has been processed into smaller particles, which may help it disperse more easily in liquid without changing the underlying form of creatine.

Product quality matters more than impressive wording

Choose a reputable manufacturer.

If you compete in tested sport, independent sport certification may be particularly valuable because contamination with prohibited substances is a separate issue from whether creatine itself works.

You do not need a proprietary “ultra-anabolic matrix.” You need the product to contain what the label says it contains.

Who should be more cautious?

Healthy-adult evidence cannot automatically be transplanted into every population.

Known kidney disease

Discuss creatine with the healthcare team managing your kidney health rather than extrapolating from healthy-adult trials. Mayo Clinic creatine guidance.

Pregnancy and breastfeeding

Creatine is being investigated in maternal and fetal physiology, but routine supplementation during pregnancy and breastfeeding does not have the depth of human safety evidence available for adult sports supplementation. A recent safety review notes that evidence remains lacking in pregnancy, while the NIH LactMed creatine monograph reports that human milk levels after supplementation have not been studied and advises avoiding supplementation unless prescribed until more data are available.

Individual clinical advice is more appropriate here than extrapolating from gym studies.

Adolescents

It is no longer accurate to say that creatine has never been studied in teenagers.

A 2026 systematic review found five eligible studies and reported no consistent short-term kidney, liver or cardiometabolic safety signals during the study periods. It also emphasized how limited the evidence remains and the need for larger studies with longer follow-up.

So the evidence is not zero. It is also nowhere near as deep as the adult literature.

Medical conditions and medications

If you are managing a medical condition or take medication that affects kidney function, fluid balance or another relevant system, disclose supplement use to your healthcare professional.

“Available without a prescription” does not mean “irrelevant to medical care.”

↑ Back to guide

Frequently asked creatine questions

Everyday use and common questions

Can I mix creatine with whey protein?

Yes. Protein and creatine do different jobs, and there is no reason they have to live in separate drinks. If putting both in the same shake helps you remember your creatine, that is a perfectly good routine. For broader nutrition context, our guide to what protein does explains the role of dietary protein in more detail.

Can I take creatine on an empty stomach?

Yes, if you tolerate it. When your stomach dislikes it, take creatine with food. There is no benefit to making a simple supplement uncomfortable.

Is creatine a steroid?

No. Creatine is not an anabolic steroid. It is a compound your body naturally makes and uses in the creatine–phosphocreatine energy system; supplementation increases creatine availability rather than working through the hormonal mechanisms that define anabolic steroids.

Training, sport and long-term use

What if I take creatine but don’t work out?

Your tissue creatine stores can still increase. But many of the outcomes people want—more strength, more muscle and better training performance—depend on actually creating a training stimulus. The scoop cannot perform the repetitions for you. See the strength evidence for the training context.

Can runners take creatine?

Yes. The better question is whether it suits the runner’s goals. Someone who strength trains, sprints or performs repeated high-intensity intervals may have more reason to use creatine than someone concerned only with long-duration endurance. The dedicated endurance meta-analysis found no significant overall performance benefit in trained populations; see the full creatine-for-runners and endurance discussion.

How long can you take creatine?

There is no evidence-based rule telling healthy adults that creatine must be stopped after an arbitrary number of weeks. Mayo Clinic currently describes recommended oral doses as likely safe for many people for up to five years. That reflects the duration supported by available longer-term evidence; it does not mean creatine suddenly becomes unsafe on the first day of year six.

The 2026 analysis of 684 randomized trials also found no consistent pattern of clinically meaningful adverse effects increasing with dose or duration at the study level. Science cannot give us lifetime data on every possible user, but the available evidence does not support the familiar rule that healthy adults must routinely cycle off because continuous creatine inevitably becomes dangerous. For the broader context, see the creatine safety section.

So, is creatine worth taking?

Creatine has travelled through two opposite reputations.

First it was the suspicious bodybuilding powder supposedly responsible for cramps, kidney damage and baldness.

Now it is in danger of becoming a universal wellness supplement for muscle, menopause, memory, mood, longevity and brain optimisation.

Neither version fits the evidence particularly well.

Creatine is excellent at a fairly specific job. It supports the body’s rapid-energy system, and that translates into strong evidence for repeated high-intensity performance, greater strength gains and modestly greater lean-mass gains alongside resistance training.

The newer possibilities—in cognition, aging and postmenopausal women—deserve curiosity without being promoted to certainty before the evidence gets there.

And ordinary creatine use is much less complicated than supplement culture has made it.

For a healthy adult who decides it fits their goals:

Use creatine monohydrate.

Take around 3–5 grams each day.

Be consistent.

Then put considerably more thought into your training, food and sleep than into the timing of the scoop.

Key research used for this September 2026 update

How this guide was researched: priority was given to systematic reviews, meta-analyses, randomized controlled trials and major evidence-based clinical or sports-nutrition resources. Community questions were useful for identifying what readers are confused or worried about, but anecdotes were not treated as proof of benefit or harm. Where individual studies carried important limitations, we also considered sample size, study duration, risk of bias and relevant author disclosures when deciding how strongly to describe a finding.

Core performance, kidney and safety evidence

  1. NIH Office of Dietary Supplements. Dietary Supplements for Exercise and Athletic Performance: Health Professional Fact Sheet. Dosing, loading, forms, safety context and high-intensity exercise guidance.
  2. Desai I, et al. (2024). The Effect of Creatine Supplementation on Resistance Training-Based Changes to Body Composition: A Systematic Review and Meta-analysis. Journal of Strength and Conditioning Research.
  3. Kazeminasab F, et al. (2025). The Effects of Creatine Supplementation on Upper- and Lower-Body Strength and Power: A Systematic Review and Meta-Analysis. Nutrients.
  4. Tsiaras A, et al. (2026). The effect of creatine supplementation on kidney function: a systematic review and meta-analysis of randomized controlled trials. Journal of Renal Nutrition.
  5. de Souza Almeida A, et al. (2026). Impact of creatine supplementation on kidney health: a systematic review and meta-analysis. International Urology and Nephrology.
  6. Lak M, et al. (2025). Does creatine cause hair loss? A 12-week randomized controlled trial. Journal of the International Society of Sports Nutrition.
  7. Kreider RB, et al. (2025). Safety of creatine supplementation: analysis of the prevalence of reported side effects in clinical trials and adverse event reports. Journal of the International Society of Sports Nutrition.
  8. Gonzalez DE, et al. (2026). Creatine Supplementation Dose and Duration Are Not Associated with Increased Side Effects: A Structured Review and Study-Level Dose-Response Analysis of Randomized Controlled Trials. Sports.

Cognition, special populations and performance contexts

  1. Naddafha S, et al. (2026). Creatine monohydrate for lean mass, strength, and bone density in postmenopausal women: a systematic review and meta-analysis. Journal of the International Society of Sports Nutrition.
  2. Xu C, et al. (2024). The effects of creatine supplementation on cognitive function in adults: a systematic review and meta-analysis. Frontiers in Nutrition.
  3. McMorris T, et al. (2024). Creatine supplementation research fails to support the theoretical basis for an effect on cognition: Evidence from a systematic review. Behavioural Brain Research.
  4. Liu S, et al. (2025). The impact of creatine supplementation associated with resistance training on muscular strength and lean tissue mass in the aged: a systematic review and meta-analysis. European Review of Aging and Physical Activity.
  5. Fernández-Landa J, et al. (2023). Effects of Creatine Monohydrate on Endurance Performance in a Trained Population: A Systematic Review and Meta-analysis. Sports Medicine.
  6. Wesołowski I, et al. (2026). Creatine Supplementation in Endurance and Mixed-Sport Contexts: A Scoping Review of Performance, Recovery, and Body Composition. Nutrients.
  7. Northeast B, Clifford T. (2021). The Effect of Creatine Supplementation on Markers of Exercise-Induced Muscle Damage: A Systematic Review and Meta-Analysis of Human Intervention Trials. International Journal of Sport Nutrition and Exercise Metabolism.
  8. Ribeiro F, et al. (2021). Timing of Creatine Supplementation around Exercise: A Real Concern? Nutrients.
  9. Ben Maaoui K, et al. (2026). Acute Creatine Ingestion Before Resistance Training Enhances Strength Performance More than Ingestion During or After Training: A Randomized Crossover Pilot Trial. Nutrients.
  10. Kaviani M, Shaw K, Chilibeck PD. (2020). Benefits of Creatine Supplementation for Vegetarians Compared to Omnivorous Athletes: A Systematic Review. International Journal of Environmental Research and Public Health.

Forms, caffeine and clinical guidance

  1. Longobardi I, et al. (2025). A short review of the most common safety concerns regarding creatine ingestion. Frontiers in Nutrition.
  2. Fazio C, et al. (2022). Efficacy of Alternative Forms of Creatine Supplementation on Improving Performance and Body Composition in Healthy Subjects: A Systematic Review. Journal of Strength and Conditioning Research.
  3. Elosegui S, et al. (2022). Interaction Between Caffeine and Creatine When Used as Concurrent Ergogenic Supplements: A Systematic Review. International Journal of Sport Nutrition and Exercise Metabolism.
  4. Marinho AH, et al. (2023). Effects of creatine and caffeine ingestion in combination on exercise performance: A systematic review. Critical Reviews in Food Science and Nutrition.
  5. Rubinchuk A, et al. (2026). Evaluating the Safety of Creatine Monohydrate in Adolescents: A Systematic Review of Renal, Hepatic, and Cardiometabolic Outcomes. Cureus.
  6. Drugs and Lactation Database (LactMed): Creatine. National Library of Medicine; revised July 15, 2025.
  7. Mayo Clinic — Creatine. Clinical overview of uses, safety, kidney caution and longer-term use.

↑ Back to top

Posted on — 2 Comments

Hydration and Health: Role of Water in Wellness

Hydration plays a pivotal role in maintaining health, yet its importance is often overlooked. This comprehensive guide delves into why hydration is vital and how it impacts various aspects of our health.

Understanding Hydration

Water makes up about 60% of our body weight and is essential for several bodily functions, including:

  • Regulating Body Temperature
  • Transporting Nutrients and Oxygen
  • Removing Waste and Toxins
  • Lubricating Joints
  • Enhancing Digestive Health

Dehydration and Its Effects

Dehydration occurs when you lose more fluid than you take in. It can lead to:

  • Reduced Cognitive Function
  • Fatigue and Weakness
  • Digestive Issues
  • Kidney Stones and Urinary Tract Infections
  • Impaired Physical Performance

How Much Water Do You Need?

The “8×8 rule” (eight 8-ounce glasses per day) is a good starting point, but individual needs vary based on factors like age, climate, activity level, and health status.

Tips for Staying Hydrated

  1. Carry a Water Bottle: Having water on hand encourages regular sipping.
  2. Eat Water-Rich Foods: Fruits and vegetables can boost your hydration.
  3. Monitor Urine Color: Pale yellow urine is a sign of good hydration.
  4. Limit Diuretics: Beverages like coffee and alcohol can increase fluid loss.
  5. Hydrate Before, During, and After Exercise: Adjust your intake based on sweat loss.

Hydration for Weight Management

Staying hydrated can aid in weight management by:

  • Reducing Appetite: Sometimes thirst is mistaken for hunger.
  • Enhancing Metabolism: Adequate water intake supports metabolic processes.

Hydration and Skin Health

Adequate hydration can improve skin health, contributing to a more youthful and vibrant complexion.

Special Considerations

Certain conditions, like pregnancy or heart disease, may require modified fluid intake. It’s important to consult healthcare providers for personalized advice.

For a more comprehensive understanding of nutrition and wellness, and to join a health-focused community, visit the BackOnTrack WeightLoss Challenge. This challenge offers extensive material and encourages participation in a holistic health journey.

Hydration is a simple yet essential part of your daily health routine. By understanding its importance and incorporating good hydration practices, you can significantly enhance your overall well-being.

10 FAQs for “Hydration and Health: The Essential Role of Water in Your Wellness Journey”

  1. Why is water so important for our body? Water is crucial for regulating body temperature, transporting nutrients, removing waste, lubricating joints, and supporting digestive health.
  2. How can I tell if I’m dehydrated? Common signs include dry mouth, fatigue, dark urine, and decreased urine output. Severe dehydration may cause dizziness and confusion.
  3. Does the amount of water I need change with exercise or weather? Yes, increased physical activity or hot weather can increase your hydration needs due to higher water loss through sweat.
  4. Can hydration affect my mood and cognitive function? Adequate hydration is essential for optimal brain function, impacting mood, concentration, and alertness.
  5. Are there benefits to drinking water for weight loss? Drinking water can aid weight loss by reducing appetite and enhancing metabolism.
  6. What are some good sources of hydration besides water? Fruits and vegetables with high water content, herbal teas, and broths are excellent hydration sources.
  7. How does hydration impact skin health? Proper hydration helps maintain skin moisture and elasticity, contributing to a healthier, more youthful complexion.
  8. Can drinking too much water be harmful? Excessive water intake can lead to water intoxication or hyponatremia, though this is rare.
  9. Are sports drinks better than water for hydration? For most people, water is sufficient. Sports drinks can be beneficial during prolonged, intense exercise due to electrolytes and carbohydrates.
  10. How can I remember to drink enough water throughout the day? Setting reminders, carrying a water bottle, and incorporating water-rich foods into your diet can help maintain regular hydration.

Blog Tags for the Post

hydration, water intake, health benefits, dehydration, drinking water, body hydration, skin health, weight loss, healthy lifestyle, wellness tips

Posted on — 1 Comment

Alcohol and Eczema: What is the Connection?

Introduction

Navigating through life with eczema can be a challenging journey, filled with a continuous search for triggers and effective management strategies. Eczema, or atopic dermatitis, is a prevalent skin condition marked by inflamed, itchy, and often painful skin lesions. Various environmental factors, including allergens, irritants, and lifestyle choices such as alcohol consumption, play a significant role in the manifestation and exacerbation of eczema symptoms. This article delves deeply into understanding the intricate relationship between alcohol and eczema, aiming to provide comprehensive insights to help individuals make informed decisions regarding alcohol consumption in the context of managing eczema.

Alcohol as a Potential Eczema Trigger

Alcohol is omnipresent in social gatherings and relaxation rituals, but it might not be the best companion for individuals with eczema. Alcohol can act as an eczema trigger, ushering in a cascade of reactions that might exacerbate the skin’s condition. Here’s a closer look at how alcohol might influence eczema:

Dehydration and Skin Barrier Disruption

Alcohol possesses diuretic properties, promoting fluid loss and leading to dehydration. Adequate hydration is paramount for skin health, and the lack thereof can result in dry, flaky, and irritated skin, which is a precursor to eczema flare-ups. Furthermore, alcohol consumption can compromise the skin’s barrier function, making it more susceptible to irritants and allergens.

Inflammation and Immune System Response

Alcohol can instigate inflammatory responses in the body. Inflammation is a cornerstone of eczema, and the introduction of alcohol can amplify this, leading to heightened skin redness, itching, and discomfort. Additionally, alcohol might modulate the immune system’s responses, potentially influencing the severity and frequency of eczema flare-ups.

  • Dehydration: Alcohol is a diuretic, which means it can lead to increased water loss, contributing to dry and irritated skin.
  • Inflammation: Alcohol can promote inflammation in the body, which might worsen eczema symptoms.
  • Immune System: Alcohol can impact the immune system’s functionality, potentially affecting the skin’s ability to heal and regenerate.

Dissecting the Impact of Different Alcoholic Beverages

Not all alcoholic beverages impact eczema equally. Various components, such as preservatives, additives, and natural ingredients in these beverages, can influence their effect on eczema.

  • Beer: Often rich in gluten and other potential allergens, beer might not be the most eczema-friendly option. The yeast and other ingredients in beer might also contribute to its potential to trigger eczema symptoms.
  • Wine: Wine, particularly red wine, is laden with histamines and sulfites, notorious for their potential to instigate allergic and sensitivity reactions, possibly leading to eczema flare-ups.
  • Spirits like Vodka: Spirits undergo extensive distillation and purification processes, potentially making them slightly more tolerable. However, they are still potent, and their high alcohol content can be harsh on the skin.

Considerations and Adaptations for Managing Eczema

For those grappling with eczema, mindful consideration of alcohol consumption is essential. Moderation is key, and understanding one’s own triggers is crucial. Hydration should be prioritized to combat the dehydrating effects of alcohol. Choosing alcoholic beverages that are purer and contain fewer additives and irritants might also be beneficial.

  • Moderation: If you choose to consume alcohol, doing so in moderation is advisable.
  • Hydration: Ensure you are well-hydrated before and after consuming alcohol to counteract its dehydrating effects.
  • Choice of Alcohol: Opt for alcoholic beverages that are less likely to trigger your eczema. You might find that some drinks are more tolerable than others.

Food and Eczema: Nourishing the Skin from Within

Eczema, or atopic dermatitis, is not just a surface-level condition. It’s a reflection of internal imbalances, often closely tied to what we consume. The foods we eat can either aggravate or alleviate eczema symptoms, making dietary choices a crucial part of managing this skin condition. In this section, we will explore the intricate relationship between food and eczema, featuring insights from various resources that delve deeply into this topic.

Foods to Avoid for Eczema: Insights from Gut Health Expert Dr. Chanu Dasari, MD

In this insightful resource, Dr. Chanu Dasari shares his expertise on the foods that tend to exacerbate eczema symptoms. Understanding and avoiding these triggers is a fundamental step in managing eczema more effectively.

Healing Eczema Naturally

Explore natural ways to heal eczema, focusing on holistic approaches and dietary adjustments that can help manage symptoms. This resource provides a broader perspective on how natural remedies, including specific foods, can play a role in eczema management.

The Impact of Dairy on Eczema

Dairy is a common dietary trigger for eczema. This article delves into the relationship between dairy consumption and eczema flare-ups, providing valuable insights for those considering dietary adjustments to manage their symptoms.

The Role of Sugar in Eczema

Sugar can be an inflammatory ingredient for many, especially those dealing with eczema. Discover how sugar impacts eczema and learn about alternative sweetening options that are more skin-friendly.

Exploring the Eczema and Gluten Connection

Gluten can be a hidden culprit behind eczema flare-ups. This resource explores the potential link between gluten and eczema, guiding those considering a gluten-free approach to managing their symptoms.

Alcohol and Eczema: Understanding the Connection

Alcohol consumption can influence eczema symptoms. Learn more about how alcohol interacts with eczema and what considerations to keep in mind regarding alcohol intake.

Conclusion

The intersection of alcohol and eczema is complex, influenced by various factors including the type of alcohol consumed and individual sensitivities. By cultivating a deeper understanding of this relationship, individuals with eczema can navigate their choices with greater awareness and mindfulness, fostering better management of their skin condition.

FAQs

  1. What is the relationship between alcohol consumption and eczema flare-ups? Alcohol can potentially exacerbate eczema symptoms due to its dehydrating effects and its ability to trigger inflammatory responses in the body. The type of alcoholic beverage and individual sensitivities also play a role in how alcohol might affect eczema.
  2. Are certain types of alcoholic beverages more likely to cause eczema flare-ups? Yes, beverages like beer and wine, which contain more histamines, sulfites, and other potential allergens, are often more likely to trigger eczema symptoms compared to purer spirits like vodka.
  3. How does alcohol affect the skin’s hydration in relation to eczema? Alcohol acts as a diuretic, promoting fluid loss and leading to dehydration. For individuals with eczema, this can result in drier skin, making the skin more susceptible to irritants and allergens.
  4. Can moderate alcohol consumption still affect eczema? Even moderate alcohol consumption can influence eczema by affecting the skin’s barrier function and hydration levels. Individual tolerance varies, and some might find that even small amounts of alcohol can trigger their symptoms.
  5. Is there a way to consume alcohol without triggering eczema symptoms? While there’s no one-size-fits-all answer, choosing alcoholic beverages with fewer additives, ensuring adequate hydration, and consuming alcohol in moderation may help in managing the potential triggering of eczema symptoms.
  6. Does the type of alcohol in beverages make a difference in eczema reactions? The type of alcohol, along with the other ingredients present in the beverage, can influence its impact on eczema. Spirits, due to their distillation process, might be slightly more tolerable.
  7. How does alcohol-induced inflammation affect eczema? Alcohol can promote inflammatory responses in the body, which can exacerbate the inflammation already present in eczema, potentially worsening the symptoms.
  8. Is it advisable to avoid alcohol completely if one has eczema? Avoidance depends on individual triggers and tolerance. For some, avoiding alcohol might help in better managing eczema, while others might not notice a significant impact.
  9. Can alcohol affect the effectiveness of eczema treatments? Alcohol might interact with certain medications and can also affect the skin’s ability to heal and respond to treatments, potentially influencing the effectiveness of eczema management strategies.
  10. What are some strategies to minimize the impact of alcohol on eczema? Strategies include choosing beverages with fewer irritants, maintaining hydration, limiting consumption, and being mindful of individual triggers and sensitivities.

Blog Tags

eczema, alcohol, skin inflammation, eczema triggers, dehydration, eczema management, alcoholic beverages, skincare